Related Experiment Video
Updated: Jul 11, 2025

Drug-Induced Sleep Endoscopy DISE with Target Controlled Infusion TCI and Bispectral Analysis in Obstructive Sleep Apnea
Published on: December 6, 2016
The interaction between neuromuscular forces, aerodynamic forces, and anatomical motion in the upper airway predicts
Qiwei Xiao1,2, Daniel Ignatiuk1, Keith McConnell1
1Division of Pulmonary Medicine, Cincinnati Children's Hospital Medical Center, Cincinnati, Ohio, United States.

Insights
Pediatric obstructive sleep apnea (OSA) severity is linked to upper airway muscle responses during breathing. This study found that airway wall motion, influenced by neuromuscular control and airflow pressure, predicts OSA severity in children.
Area of Science:
- Respiratory Physiology
- Pediatric Sleep Medicine
- Biomedical Engineering
Background:
- Upper airway neuromuscular response to pressure is crucial for obstructive sleep apnea (OSA) assessment in children.
- Understanding the interplay between muscle activity, airflow, and airway collapse is key to determining OSA severity.
Purpose of the Study:
- To quantify upper airway neuromuscular responses (strength, timing, duration) at the soft palate, tongue, and epiglottis.
- To assess the relationship between neuromuscular control, airway mechanics, and OSA severity in pediatric subjects, including those with trisomy 21.
- To investigate the interaction between neuromuscular and aerodynamic forces using novel noninvasive methods.
Main Methods:
- Combined cine magnetic resonance imaging (MRI) for airway wall motion and computational fluid dynamics (CFD) for air pressure.
- Calculated power transfer between airway wall and airflow, assessing synchronous (passive) and asynchronous (active) responses.
- Studied 20 pediatric subjects (with/without trisomy 21) under sedation, correlating findings with obstructive apnea-hypopnea index (oAHI).
Main Results:
- Asynchronous airway dilation at the soft palate, tongue, and epiglottis significantly correlated with oAHI (Spearman's ρ = 0.54–0.64).
- Synchronous collapse at the epiglottis also significantly correlated with oAHI (ρ = 0.52).
- The temporal pattern of epiglottis motion predicted OSA severity (moderate vs. severe) with high sensitivity (100%) and moderate specificity (70%).
Conclusions:
- Severe OSA and/or trisomy 21 in pediatric patients is associated with insufficient neuromuscular activation during inhalation, leading to airway collapse.
- Airflow-driven airway wall motion, particularly during late inhalation, appears to be a primary determinant of OSA severity.
- Power transfer analysis provides a novel, noninvasive method to predict OSA severity in pediatric patients.
Abstract:
Upper airway neuromuscular response to air pressure during inhalation is an important factor in assessing pediatric subjects with obstructive sleep apnea (OSA). The neuromuscular response's strength, timing, and duration all contribute to the potential for airway collapses and the severity of OSA. This study quantifies these factors at the soft palate, tongue, and epiglottis to assess the relationship between neuromuscular control and OSA severity in 20 pediatric subjects with and without trisomy 21, under dexmedetomidine-induced sedation. The interaction between neuromuscular force and airflow pressure force was assessed based on power transferred between the airway wall and airflow calculated from airway wall motion (from cine magnetic resonance images) and air pressure acting on the airway wall (from computational fluid dynamics simulations). Airway wall motion could be asynchronous with pressure forces due to neuromuscular activation, or synchronous with pressure forces, indicating a passive response to airflow. The obstructive apnea-hypopnea index (oAHI) quantified OSA severity. During inhalation, the normalized work done through asynchronous dilation of the airway at the soft palate, tongue, and epiglottis correlated significantly with oAHI (Spearman's ρ = 0.54, 0.50, 0.64; P = 0.03, 0.03, 0.003). Synchronous collapse at the epiglottis correlated significantly with oAHI (ρ = 0.52; P = 0.02). Temporal order of synchronous and asynchronous epiglottis motion during inhalation predicted the severity of OSA (moderate vs. severe) with 100% sensitivity and 70% specificity. Subjects with severe OSA and/or trisomy 21 have insufficient neuromuscular activation during inhalation, leading to collapse and increased neuromuscular activation. Airflow-driven airway wall motion during late inhalation likely is the main determinant of OSA severity.NEW & NOTEWORTHY This is the first study that combines cine MRI and computational fluid dynamics with in vivo synchronous respiratory flow measurement to quantify the interaction between airway neuromuscular forces, aerodynamic forces, and airway anatomy noninvasively in pediatric patients with obstructive sleep apnea (OSA). The results indicate power transfer predicts OSA severity.
Related Concept Videos
 01:21
Sleep Apnea
The condition is more prevalent among...
 01:30
Assessment of Airway, Skin Color, and Use of Accessory Muscles
Introduction
The initial evaluation of a patient's respiratory system...
 01:19
Factors Affecting Pulmonary Ventilation
Alveolar Surface Tension
The alveolar fluid lines the luminal surface of the alveoli and exerts a force called surface tension. This force is caused by the polar water molecules in the liquid being more strongly attracted to each...
 01:21
Mechanism of Breathing III: The Accessory Muscles
The respiratory system is a complex network that relies on primary respiratory muscles like the diaphragm, but also involves accessory muscles to enhance lung expansion and airflow during both inhalation and exhalation.
Enhancing Inhalation with Accessory Muscles:
Accessory muscles such as the sternocleidomastoid, scalene, intercostal, and abdominal muscles are crucial when additional respiratory effort is required, such as during deep...
 01:22
Physiology of Respiration II: Neurogenic Control of Respiration
Central Control
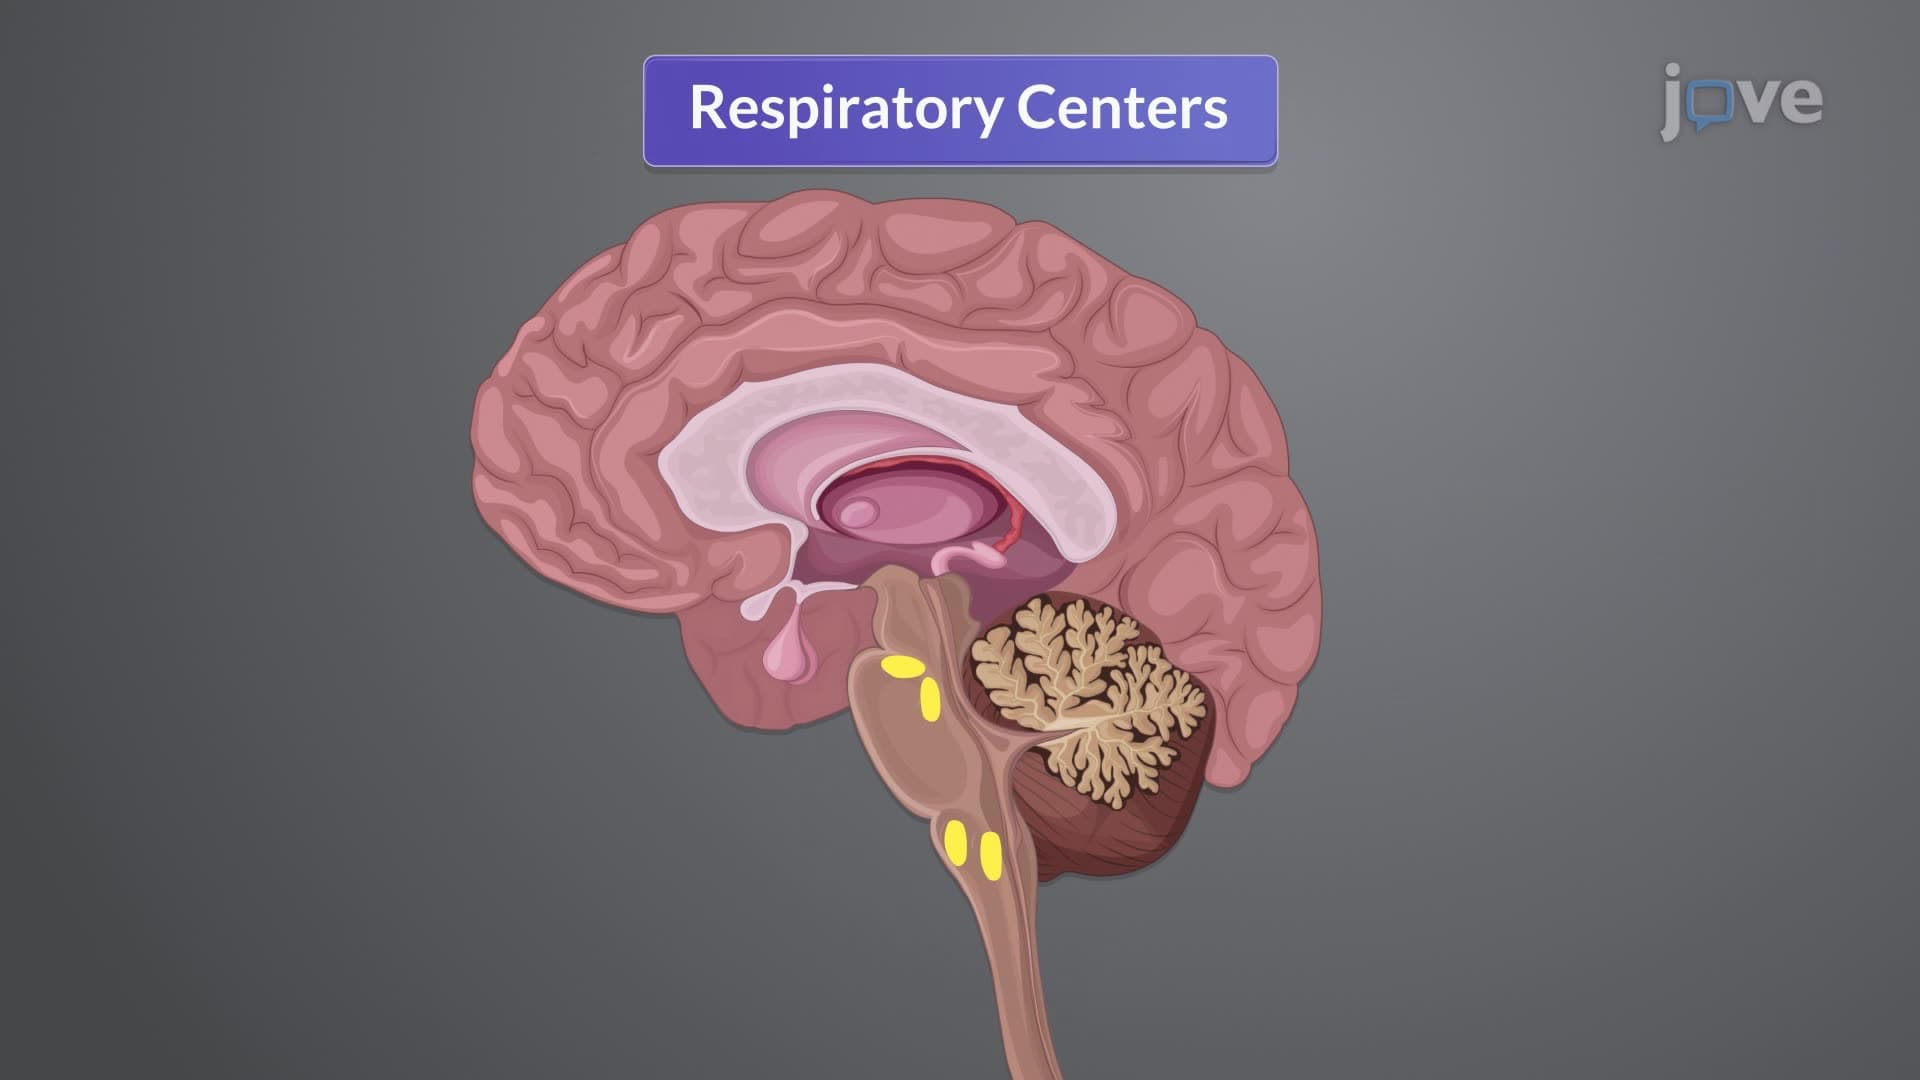
The brainstem is the primary site of central control, hosting respiratory centers:
 01:22
Cardiopulmonary Resuscitation II: ACLS Airway Management