Related Experiment Video
Updated: Jul 11, 2025
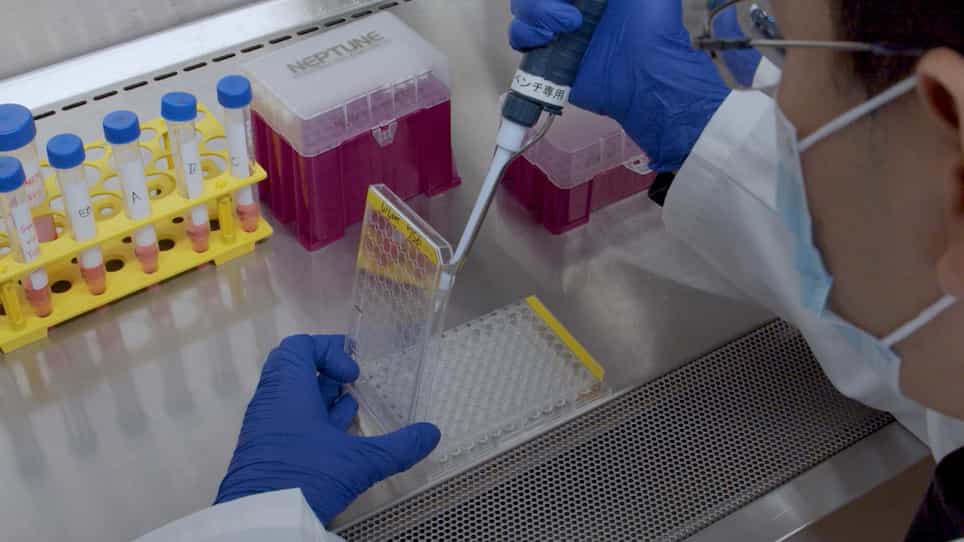

Model of Ischemic Heart Disease and Video-Based Comparison of Cardiomyocyte Contraction Using hiPSC-Derived Cardiomyocytes
Published on: May 5, 2020
Mechanical Resistance to Micro-Heart Tissue Contractility unveils early Structural and Functional Pathology in iPSC

Insights
Mechanical stress combined with hypertrophic cardiomyopathy (HCM) mutations triggers disease phenotypes. This study used engineered heart tissues to reveal HCM hallmarks, offering insights into inherited heart conditions.
Area of Science:
- Cardiovascular Biology
- Biomedical Engineering
- Stem Cell Biology
Background:
- Hypertrophic cardiomyopathy (HCM) is a leading cause of sudden cardiac death in young individuals.
- Variable disease penetrance suggests nongenetic factors contribute to HCM.
- Hypertension exacerbates HCM, indicating a synergistic role between mechanical stress and sarcomeric mutations.
Approach:
- Developed an in vitro physiological model using micro-heart muscle arrays (μHM) from iPSC-derived cardiomyocytes with MYBPC3 loss-of-function mutations.
- Challenged μHMs to contract against varying mechanical loads (substrate stiffnesses from 0.4 kPa to 114 kPa).
- Compared disease manifestation in μHMs with afterload versus standard 2D cell cultures.
Key Points:
- μHMs with afterload exhibited HCM hallmarks like cellular hypertrophy, impaired energetics, and abnormal calcium handling, unlike 2D cultures.
- Observed unique changes in troponin C and T localization in MYBPC3+/- μHMs under mechanical stress.
- Pharmacologic studies implicated excessive calcium influx via membrane channels in electrophysiological abnormalities.
Conclusions:
- Physiologically relevant engineered tissue models are powerful tools for studying inherited cardiac diseases.
- Mechanical stress acts synergistically with MYBPC3 mutations to induce HCM phenotypes.
- Understanding calcium handling defects is crucial for developing targeted HCM therapies.
Abstract:
Hypertrophic cardiomyopathy is the most common cause of sudden death in the young. Because the disease exhibits variable penetrance, there are likely nongenetic factors that contribute to the manifestation of the disease phenotype. Clinically, hypertension is a major cause of morbidity and mortality in patients with HCM, suggesting a potential synergistic role for the sarcomeric mutations associated with HCM and mechanical stress on the heart. We developed an in vitro physiological model to investigate how the afterload that the heart muscle works against during contraction acts together with HCM-linked MYBPC3 mutations to trigger a disease phenotype. Micro-heart muscle arrays (μHM) were engineered from iPSC-derived cardiomyocytes bearing MYBPC3 loss-of-function mutations and challenged to contract against mechanical resistance with substrates stiffnesses ranging from the of embryonic hearts (0.4 kPa) up to the stiffness of fibrotic adult hearts (114 kPa). Whereas MYBPC3 +/- iPSC-cardiomyocytes showed little signs of disease pathology in standard 2D culture, μHMs that included components of afterload revealed several hallmarks of HCM, including cellular hypertrophy, impaired contractile energetics, and maladaptive calcium handling. Remarkably, we discovered changes in troponin C and T localization in the MYBPC3 +/- μHM that were entirely absent in 2D culture. Pharmacologic studies suggested that excessive Ca 2+ intake through membrane-embedded channels, rather than sarcoplasmic reticulum Ca 2+ ATPase (SERCA) dysfunction or Ca 2+ buffering at myofilaments underlie the observed electrophysiological abnormalities. These results illustrate the power of physiologically relevant engineered tissue models to study inherited disease mechanisms with iPSC technology.


