Related Experiment Video
Updated: Jul 10, 2025


Isolation of Leukocytes from Human Breast Milk for Use in an Antibody-dependent Cellular Phagocytosis Assay of HIV Targets
Published on: September 6, 2019
Combined Hormonal Contraception during Breastfeeding-A Survey of Physician's Recommendations
Lior Segev1,2, Gideon Weitzman2, Goldie Katz-Samson3
1Azrieli Faculty of Medicine, Bar Ilan University, Safed 1311502, Israel.

Until breastfeeding is established, progesterone-only pill (POP) use is preferable over combined hormonal contraception (CHC), as the latter potentially reduces milk production. Yet, POPs are often associated with breakthrough bleeding (BTB), and irregular spotting is often a reason for their cessation. Conversely, CHC is less associated with BTB but is not usually prescribed, even if breastfeeding has been established, despite its verified safety profile. Here, we surveyed physicians' perception of CHC safety during breastfeeding through an online questionnaire (N = 112). Physicians were asked if they would prescribe CHC to a woman three months postpartum, breastfeeding fully, and suffering from BTB while using POPs. Half of the physicians responded they would, 28% would not until six months postpartum, while 14% would not during breastfeeding. Of the physicians that would prescribe CHC, 58% would without any reservation, 24% would only after discussing milk reduction with the patient, 9% would use a pill with a lower hormonal dose, and 9% would only prescribe CHC 3 months postpartum. The main risk associated with CHC during breastfeeding, as perceived by physicians, is a potential decrease in breast milk production (88%). While some physicians consider CHC unsafe during breastfeeding, most health organizations consider CHC compatible with breastfeeding 5-6 weeks after birth. Thus, there is a gap in the attitude and knowledge of physicians about the safety profile of CHC, and only half acknowledge that the risk of BTB justifies the use of CHC instead of POPs while breastfeeding three months postpartum. We highlight the importance of physician's education, advocate CHC breastfeeding compatibility if breastfeeding has been established (i.e., 30 days postpartum), and underline the importance of discussing the option of CHC with patients in case POPs have unwanted side effects.
Until breastfeeding is established, progesterone-only pill (POP) use is preferable over combined hormonal contraception (CHC), as the latter potentially reduces milk production. Yet, POPs are often associated with breakthrough bleeding (BTB), and irregular spotting is often a reason for their cessation. Conversely, CHC is less associated with BTB but is not usually prescribed, even if breastfeeding has been established, despite its verified safety profile. Here, we surveyed physicians' perception of CHC safety during breastfeeding through an online questionnaire (N = 112). Physicians were asked if they would prescribe CHC to a woman three months postpartum, breastfeeding fully, and suffering from BTB while using POPs. Half of the physicians responded they would, 28% would not until six months postpartum, while 14% would not during breastfeeding. Of the physicians that would prescribe CHC, 58% would without any reservation, 24% would only after discussing milk reduction with the patient, 9% would use a pill with a lower hormonal dose, and 9% would only prescribe CHC 3 months postpartum. The main risk associated with CHC during breastfeeding, as perceived by physicians, is a potential decrease in breast milk production (88%). While some physicians consider CHC unsafe during breastfeeding, most health organizations consider CHC compatible with breastfeeding 5-6 weeks after birth. Thus, there is a gap in the attitude and knowledge of physicians about the safety profile of CHC, and only half acknowledge that the risk of BTB justifies the use of CHC instead of POPs while breastfeeding three months postpartum. We highlight the importance of physician's education, advocate CHC breastfeeding compatibility if breastfeeding has been established (i.e., 30 days postpartum), and underline the importance of discussing the option of CHC with patients in case POPs have unwanted side effects.


Related Concept Videos
 01:22
Birth Control Methods
 01:22
Hormonal Regulation of the Menstrual Cycle
At puberty, GnRH begins a pulsatile release pattern, which triggers the anterior pituitary gland to secrete follicle-stimulating hormone (FSH) and luteinizing hormone (LH). The frequency and amplitude of GnRH pulses vary across the menstrual cycle, with faster pulses favoring LH release and slower pulses favoring FSH...
 01:22
Target Cell Response to Hormones
Notably, the cellular response can be regulated by altering the number of receptors expressed in the cell. For example, prolonged exposure to elevated hormone levels results in a gradual decline or down-regulation in the number of receptors for that specific hormone on the cell surface. Conversely, in response to low hormone levels, cells may use up-regulation, producing an...
 01:24
Gonadal and Placental Hormones
In males, testosterone is the primary gonadal androgen. It plays a central role in the maturation of male reproductive organs — the penis and testes. Additionally, testosterone is instrumental in the development of secondary sexual characteristics — a deep voice as well as facial and pubic hair...
 01:15
Drug Dosage Regimen: Overview
Typically, the starting dose and dosing interval are guided by the manufacturer's recommendations based on clinical trials conducted during and after drug...
 01:01
Dosage Regimen: Fixed Dose
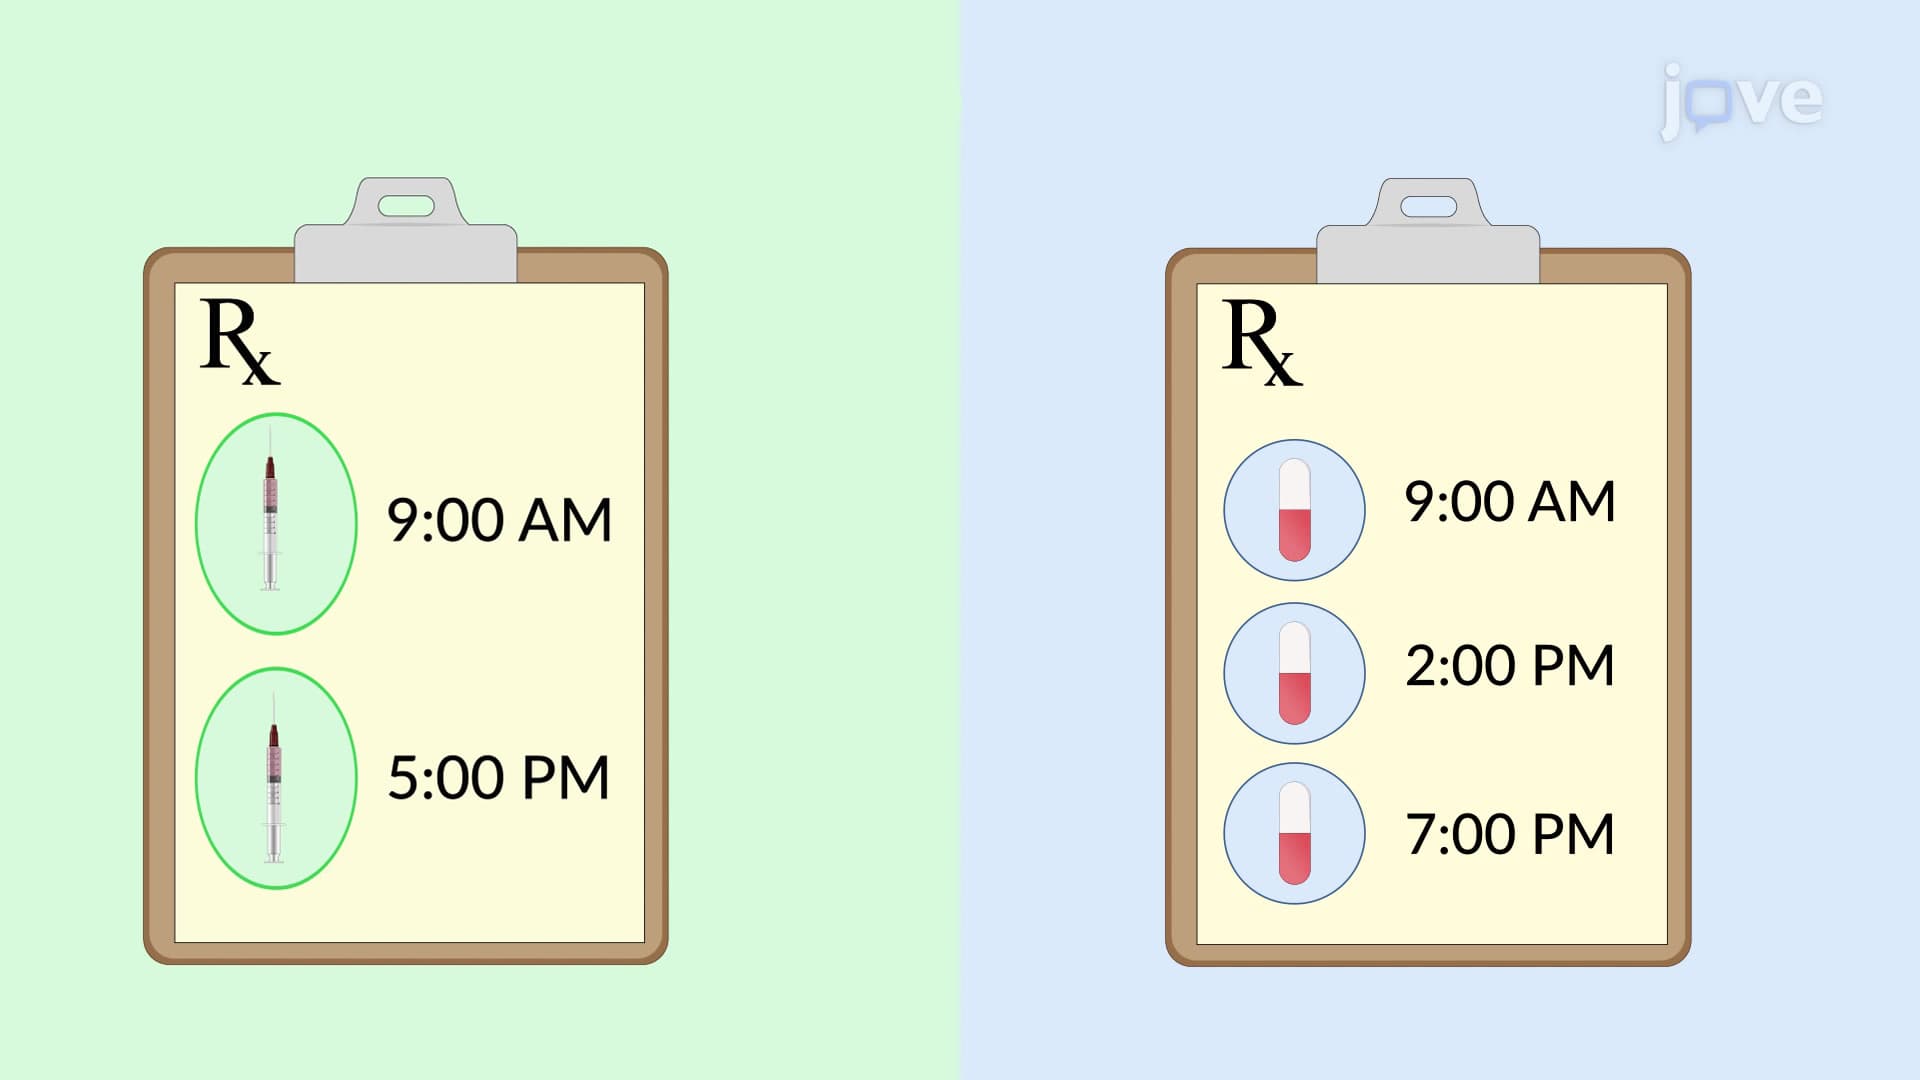
Fixed-dose regimens can be used for various routes of administration, including intravenous (IV) injections and oral medications. For IV administration, a predetermined amount of the drug is...