Related Experiment Video
Updated: Jul 10, 2025
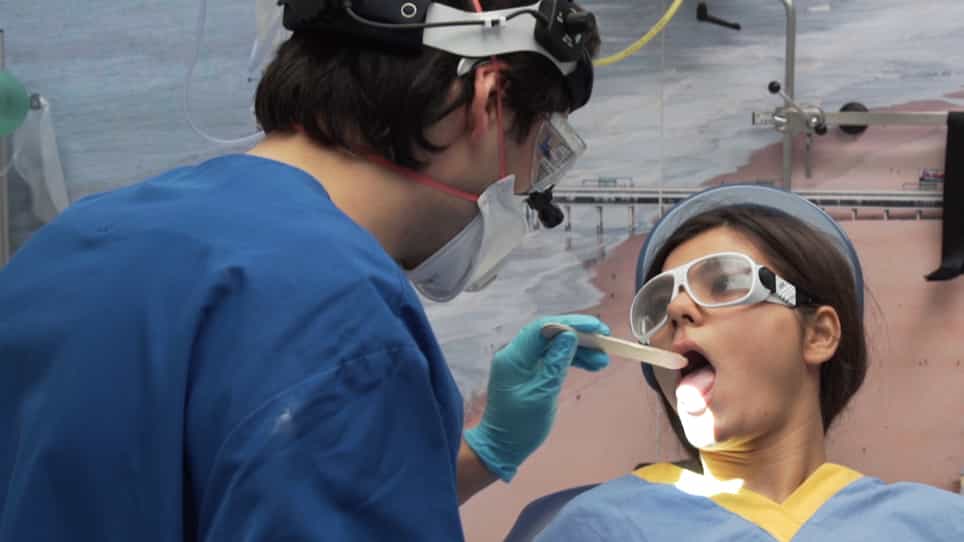

CO2-Lasertonsillotomy Under Local Anesthesia in Adults
Published on: November 6, 2019
Airway management of lingual tonsillar hypertrophy: A narrative review
Patrick Wong1, Jamie W Sleigh2
1Department of Anaesthesia and Pain Medicine, Te Whatu Ora Health New Zealand Waikato, Hamilton, New Zealand.

Abstract:
Lingual tonsillar hypertrophy is rarely identified on routine airway assessment but may cause difficulties in airway management. We conducted a narrative review of case reports of lingual tonsillar hypertrophy to examine associated patient factors, success rates of airway management techniques and complications. We searched the literature for anaesthetic management of cases with lingual tonsillar hypertrophy. We found 89 patients in various case reports, from which we derived 92 cases to analyse. 64% of cases were assessed as having a normal airway. Difficult and impossible face mask ventilation occurred in 29.6% and 1.4% of cases, respectively. Difficult intubation and failed intubation occurred in 89.1% and 21.7% of cases, respectively. Multiple attempts (up to six) at intubation were performed, with no successful intubation after the third attempt with direct laryngoscopy. Some 16.5% of patients were woken up and 4.3% required emergency front of neck access. Complications included oesophageal intubation (10.9%), bleeding (9.8%) and severe hypoxia (3.2%). Our findings show that severe cases of lingual hypertrophy may cause an unanticipated difficult airway and serious complications, including hypoxic brain damage and death. A robust airway strategy is required which includes limiting the number of attempts at laryngoscopy, and early priming and performance of emergency front of neck access if required. In patients with known severe lingual tonsillar hypertrophy, awake intubation should be considered.


Related Concept Videos
 01:23
Chronic Pharyngitis
Etiology
It often arises from persistent viral or bacterial infections affecting sinuses and tonsils.
Additional contributing factors include inadequate dental hygiene, mouth breathing, recurring tonsillitis, allergic rhinitis, laryngopharyngeal reflux, and exposure to smoke, chemicals, and other environmental pollutants. Allergic reactions to pollen, mold, and pet dander, chronic cough, excessive voice usage,...
 01:26
Tonsillitis II: Management
 01:30
Tonsillitis I: Introduction
Etiology
Three primary contributing factors have been identified.
 01:22
Trachea
Anatomical Features:
Location: About half of the trachea is situated in the neck, anterior to the esophagus, and extends from the larynx (at the level of...
 01:17
Endotracheal Intubation II: Nursing Management
1. Nursing Care of Patients Before Intubation
Before the endotracheal intubation procedure, nurses play an essential role in ensuring the process goes smoothly. The nurses must be familiar with intubation...
 01:15
Endotracheal Intubation I: Procedure
The ET tube comprises various components, including a standard adaptor to attach a bag-valve-mask (BVM) or ventilator, a cuff, a pilot balloon, and radiopaque markings along its length to measure the insertion distance. The tube sizes...