Related Experiment Video
Updated: Jul 10, 2025
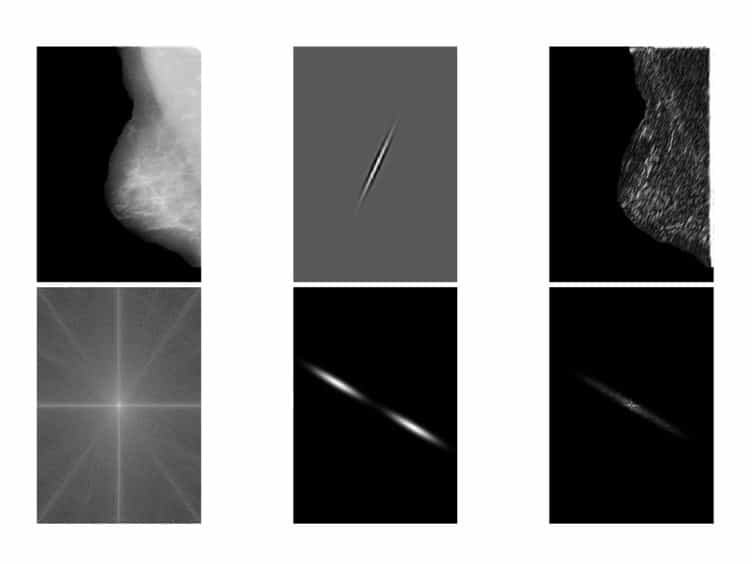

Detection of Architectural Distortion in Prior Mammograms via Analysis of Oriented Patterns
Published on: August 30, 2013
Benefits and Harms of Mammography Screening in 75 + Women to Inform Shared Decision-making: a Simulation Modeling
Jinani Jayasekera1, Sarah Stein2, Oliver W A Wilson3
1Health Equity and Decision Sciences Research Laboratory, National Institute on Minority Health and Health Disparities (NIMHD) Intramural Research Program (IRP), National Institutes of Health, Bethesda, MD, 20892, USA. jinani.jayasekera@nih.gov.

Background:
Guidelines recommend shared decision-making (SDM) around mammography screening for women ≥ 75 years old.
Objective:
To use microsimulation modeling to estimate the lifetime benefits and harms of screening women aged 75, 80, and 85 years based on their individual risk factors (family history, breast density, prior biopsy) and comorbidity level to support SDM in clinical practice.
Design, Setting, And Participants:
We adapted two established Cancer Intervention and Surveillance Modeling Network (CISNET) models to evaluate the remaining lifetime benefits and harms of screening U.S. women born in 1940, at decision ages 75, 80, and 85 years considering their individual risk factors and comorbidity levels. Results were summarized for average- and higher-risk women (defined as having breast cancer family history, heterogeneously dense breasts, and no prior biopsy, 5% of the population).
Main Outcomes And Measures:
Remaining lifetime breast cancers detected, deaths (breast cancer/other causes), false positives, and overdiagnoses for average- and higher-risk women by age and comorbidity level for screening (one or five screens) vs. no screening per 1000 women.
Results:
Compared to stopping, one additional screen at 75 years old resulted in six and eight more breast cancers detected (10% overdiagnoses), one and two fewer breast cancer deaths, and 52 and 59 false positives per 1000 average- and higher-risk women without comorbidities, respectively. Five additional screens over 10 years led to 23 and 31 additional breast cancer cases (29-31% overdiagnoses), four and 15 breast cancer deaths avoided, and 238 and 268 false positives per 1000 average- and higher-risk screened women without comorbidities, respectively. Screening women at older ages (80 and 85 years old) and high comorbidity levels led to fewer breast cancer deaths and a higher percentage of overdiagnoses.
Conclusions:
Simulation models show that continuing screening in women ≥ 75 years old results in fewer breast cancer deaths but more false positive tests and overdiagnoses. Together, clinicians and 75 + women may use model output to weigh the benefits and harms of continued screening.

Related Concept Videos
 01:14
Imaging Studies I: CT and MRI
Description of the Procedures
Computed Tomography (CT) scan:
Computed Tomography (CT) scans use X-ray technology to generate detailed images of bones, organs, and tissues. During the scan, the patient lies on a moving table...
 01:27
Nursing Ethical Principles II
Consider the following scenario, which illustrates how these principles are applied in the care of Mr. John, a fifty-year-old teacher diagnosed with metastatic liver cancer.
Initially, Mr. John's...
 01:30
Preventive Healthcare Services
 01:28
Menopause
 01:20
Lifestyle Factors and Health
Benefits of Physical Activity
Physical activity, whether through structured exercise or casual activities like walking, biking, or dancing, is a cornerstone of a...
 01:30
Radiological Investigation I: X-ray and CT