Related Experiment Video
Updated: Jul 29, 2026

Surgical Retrieval, Isolation and In vitro Expansion of Human Anterior Cruciate Ligament-derived Cells for Tissue Engineering Applications
Published on: April 30, 2014
Weaker Quadriceps Muscle Strength With a Quadriceps Tendon Graft Compared With a Patellar or Hamstring Tendon Graft
David Holmgren1,2, Shiba Noory1, Eva Moström1,2
1Department of Molecular Medicine and Surgery, Stockholm Sports Trauma Research Center, Karolinska Institutet, Stockholm, Sweden.

Background:
Impaired quadriceps muscle strength after anterior cruciate ligament reconstruction (ACLR) is associated with worse clinical outcomes and a risk of reinjuries. Yet, we know little about quadriceps muscle strength in patients reconstructed with a quadriceps tendon (QT) graft, which is increasing in popularity worldwide.
Purpose:
To describe and compare isokinetic quadriceps strength in patients undergoing ACLR with a QT, hamstring tendon (HT), or bone-patellar tendon-bone (BPTB) autograft.
Study Design:
Cross-sectional study; Level of evidence, 3.
Methods:
We included patients with QT grafts (n = 104) and matched them to patients with HT (n = 104) and BPTB (n = 104) grafts based on age, sex, and associated meniscal surgery. Data were collected through clinical strength testing at a mean of 7 ± 1 months postoperatively. Isokinetic strength was measured at 90 deg/s, and quadriceps strength was expressed as the limb symmetry index (LSI) for peak torque, total work, torque at 30° of knee flexion, and time to peak torque.
Results:
Patients with QT grafts had the most impaired isokinetic quadriceps strength, with the LSI ranging between 67.5% and 75.1%, followed by those with BPTB grafts (74.4%-81.5%) and HT grafts (84.0%-89.0%). Patients with QT grafts had a significantly lower LSI for all variables compared with patients with HT grafts (mean difference: peak torque: -17.4% [95% CI, -21.7 to -13.2], P < .001; total work: -15.9% [95% CI, -20.6 to -11.1], P < .001; torque at 30° of knee flexion: -8.8% [95% CI, -14.7 to -2.9], P = .001; time to peak torque: -17.7% [95% CI, -25.8 to -9.6], P < .001). Compared with patients with BPTB grafts, patients with QT grafts had a significantly lower LSI for all variables (mean difference: peak torque: -6.9% [95% CI, -11.2 to -2.7], P < .001; total work: -7.7% [95% CI, -12.4 to -2.9], P < .001; torque at 30° of knee flexion: -6.3% [95% CI, -12.2 to -0.5], P = .03; time to peak torque: -8.8% [95% CI, -16.9 to -0.7], P = .03). None of the graft groups reached a mean LSI of >90% for peak torque (QT: 67.5% [95% CI, 64.8-70.1]; HT: 84.9% [95% CI, 82.4-87.4]; BPTB: 74.4% [95% CI, 72.0-76.9]).
Conclusion:
At 7 months after ACLR, patients with QT grafts had significantly worse isokinetic quadriceps strength than patients with HT and BPTB grafts. None of the 3 graft groups reached a mean LSI of >90% in quadriceps strength.
More Related Videos


Related Concept Videos
 01:16
Bones of the Lower Limb: Femur and Patella
 01:23
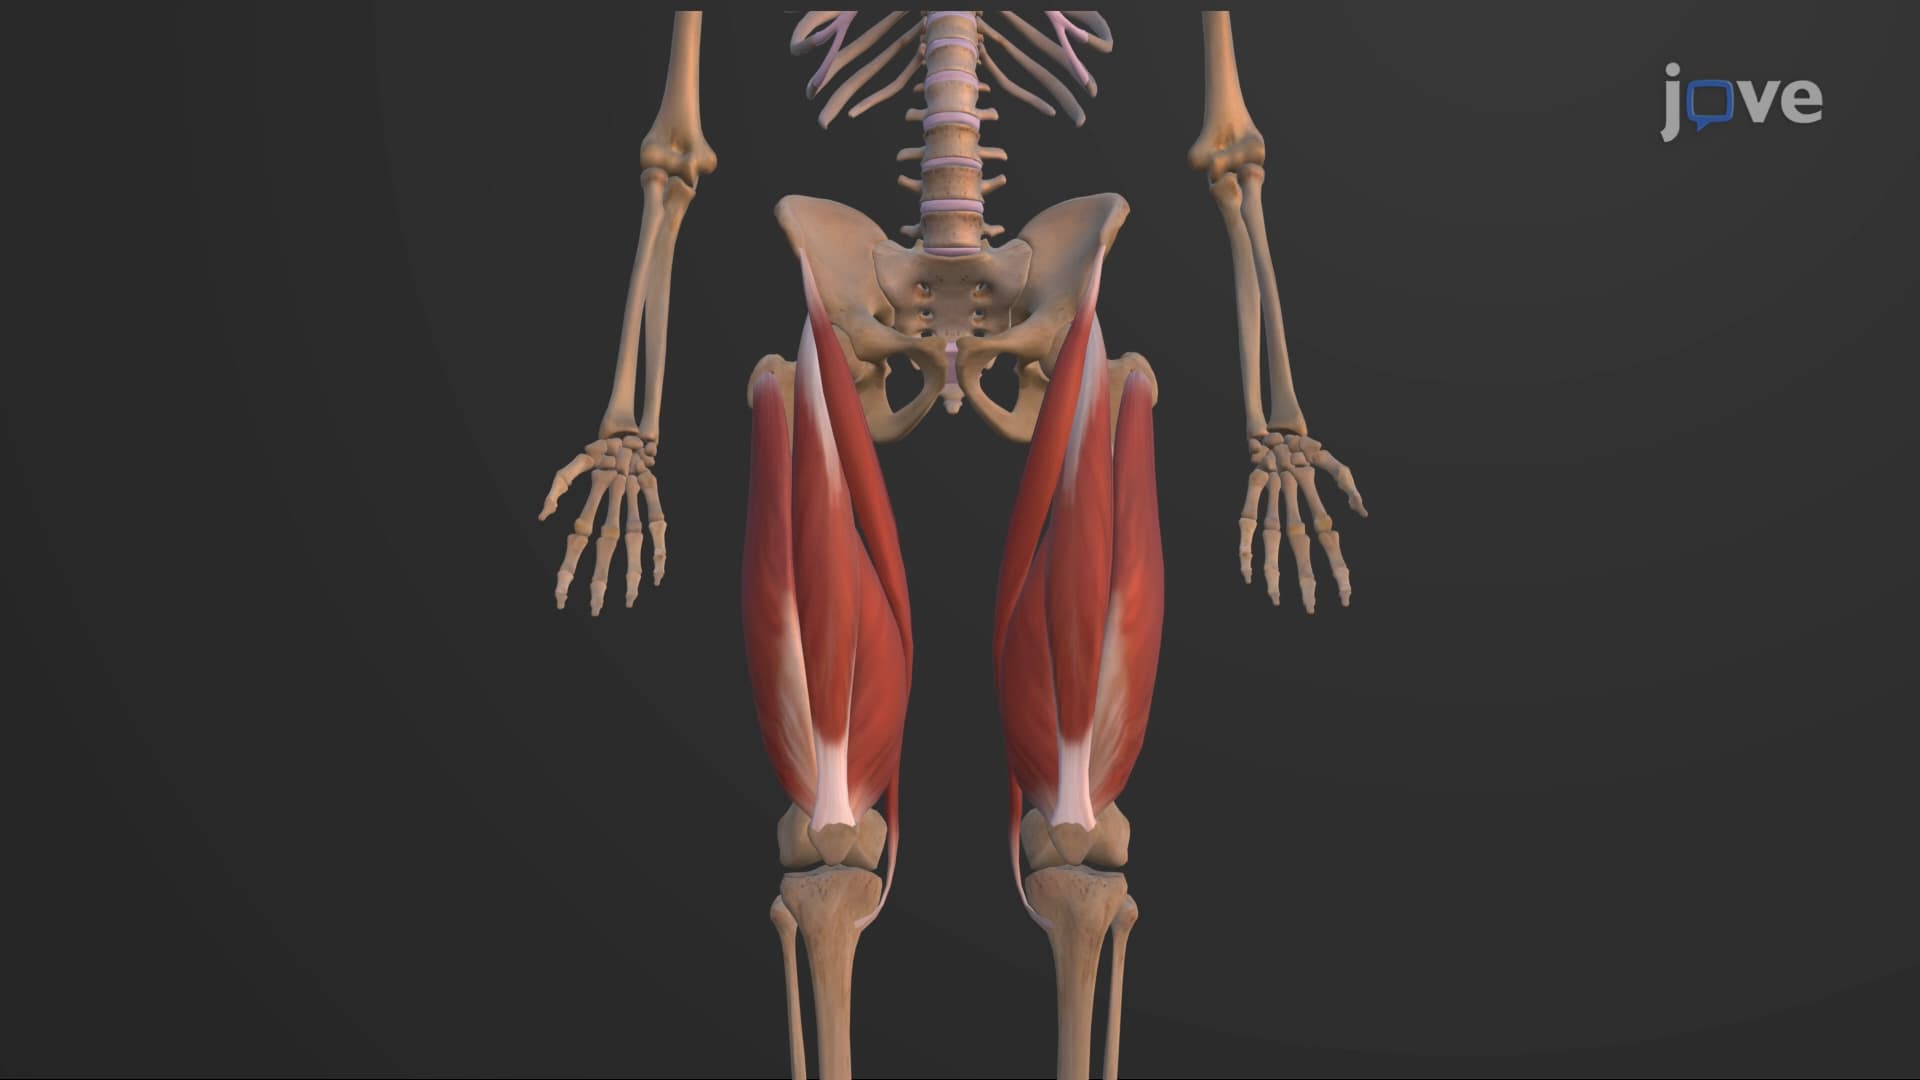
Muscles that Move the Leg
Anterior Compartment
The quadriceps femoris, the most visible muscle of the anterior compartment, is integral for leg extension and thigh flexion. It is formed by merging four distinct muscles — the vastus lateralis, vastus medialis, vastus intermedius, and rectus femoris. The quadriceps tendon, a shared tendon of the four quadriceps muscles, is affixed to...