Related Experiment Video
Updated: Jul 6, 2026

Granulocyte-dependent Autoantibody-induced Skin Blistering
Published on: October 12, 2012
Molecular basis for the deficiency of complement 1 inhibitor in type I hereditary angioneurotic edema

Hereditary angioneurotic edema (HANE) results from deficiency of complement 1 inhibitor (C1 INH). In type I HANE, C1 INH is present in serum at levels 5-30% of normals. Using cultured monocytes and biosynthetic labeling of proteins, C1 INH was detected in supernatants of cells from HANE patients at levels 20% of those detected in normals. The intracellular reduction of C1 INH in patients' monocytes approached 50%. The study of C1 INH messenger RNA (mRNA) by Northern blot analysis indicated that in HANE patients' monocytes a message of normal size is present at about half the concentration of that from normal cells. One of the patients analyzed showed the presence of a genetically inherited abnormal mRNA (1.9 kb) in addition to the normal mRNA (2.1 kb). Southern blot analysis of DNA from peripheral blood leukocytes did not show any difference in quantity or in sizes of endonuclease restriction fragments between patients and normals. The defect(s), therefore, in type I HANE is pretranslational, but is not due to a deletion or to a major chromosomal rearrangement.
Hereditary angioneurotic edema (HANE) results from deficiency of complement 1 inhibitor (C1 INH). In type I HANE, C1 INH is present in serum at levels 5-30% of normals. Using cultured monocytes and biosynthetic labeling of proteins, C1 INH was detected in supernatants of cells from HANE patients at levels 20% of those detected in normals. The intracellular reduction of C1 INH in patients' monocytes approached 50%. The study of C1 INH messenger RNA (mRNA) by Northern blot analysis indicated that in HANE patients' monocytes a message of normal size is present at about half the concentration of that from normal cells. One of the patients analyzed showed the presence of a genetically inherited abnormal mRNA (1.9 kb) in addition to the normal mRNA (2.1 kb). Southern blot analysis of DNA from peripheral blood leukocytes did not show any difference in quantity or in sizes of endonuclease restriction fragments between patients and normals. The defect(s), therefore, in type I HANE is pretranslational, but is not due to a deletion or to a major chromosomal rearrangement.
Related Concept Videos
 01:27
Complement System
 01:20
Chronic Obstructive Pulmonary Disease-II: Pathophysiology
Chronic Inflammation
 01:28
Asthma I: Introduction
 01:23
Chronic Obstructive Pulmonary Disease II: Emphysema
 01:18
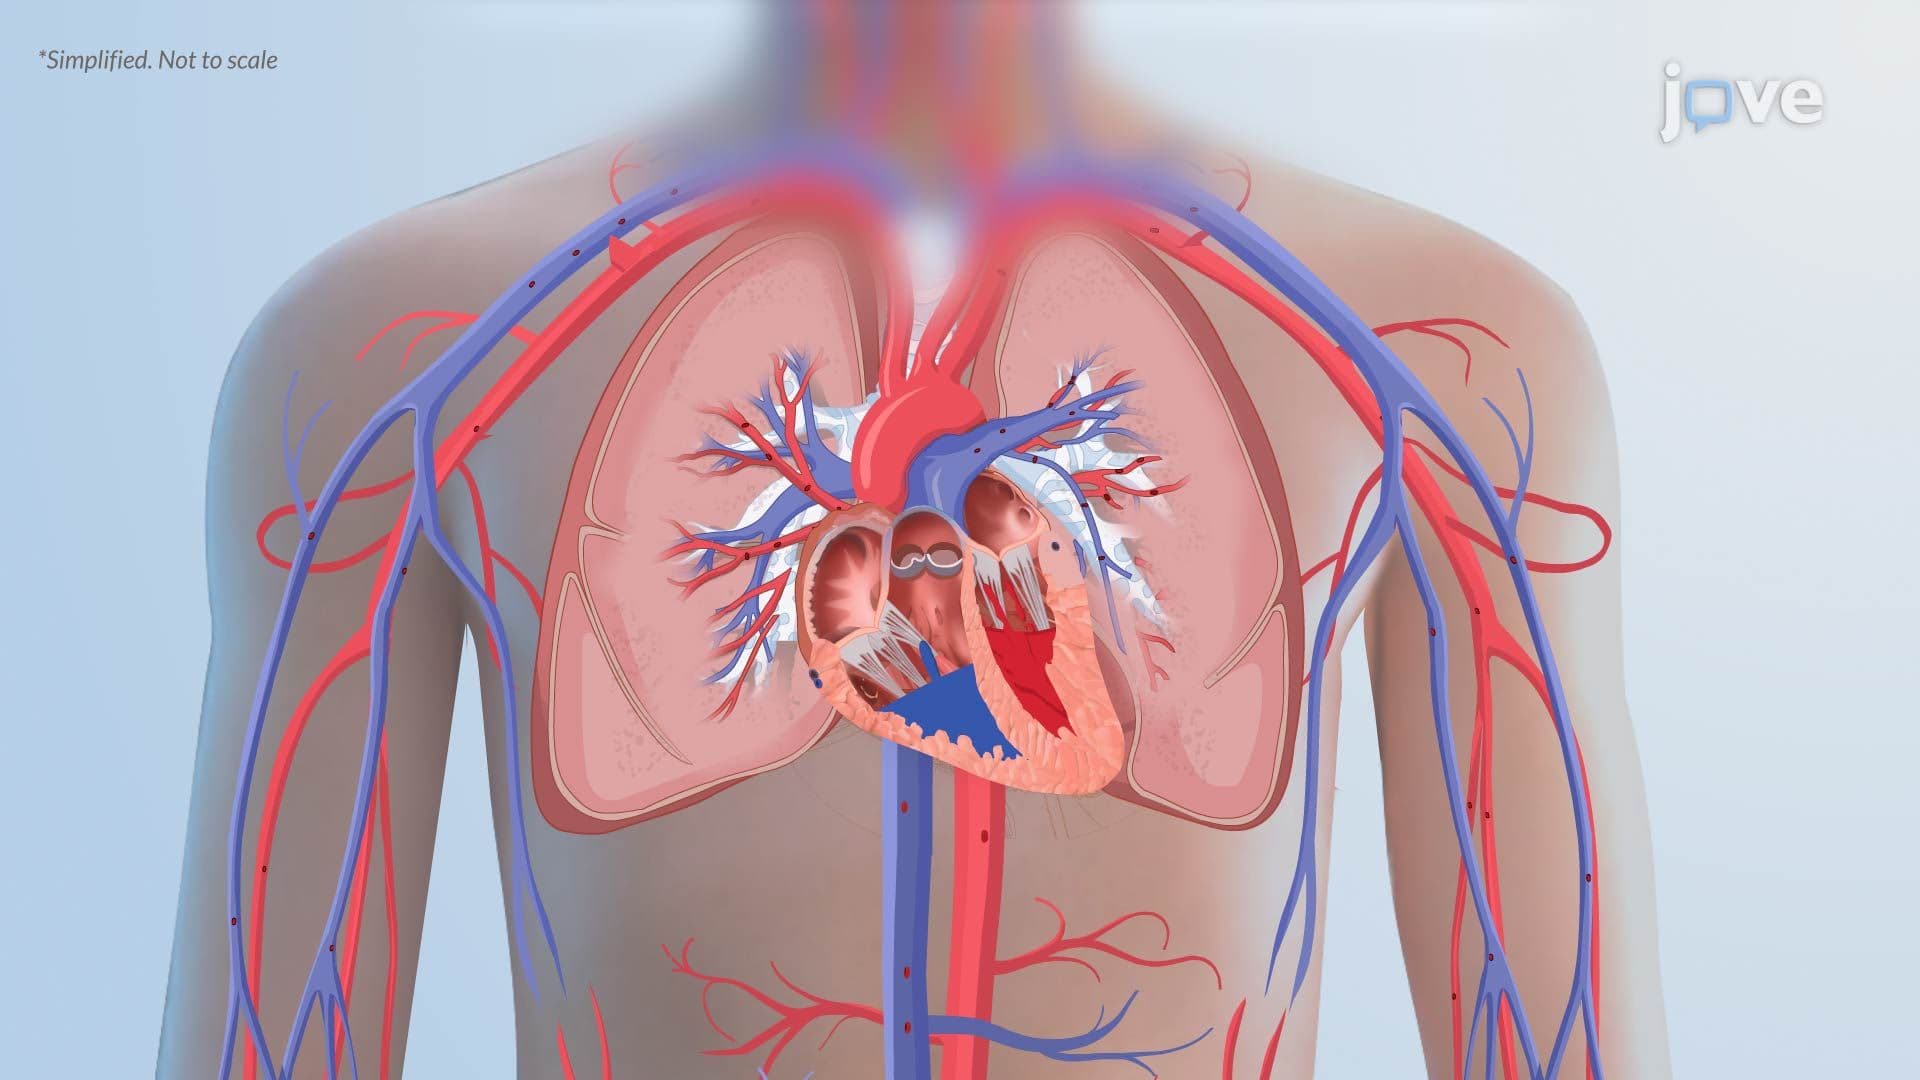
Pulmonary Edema II: Pathophysiology
 01:19
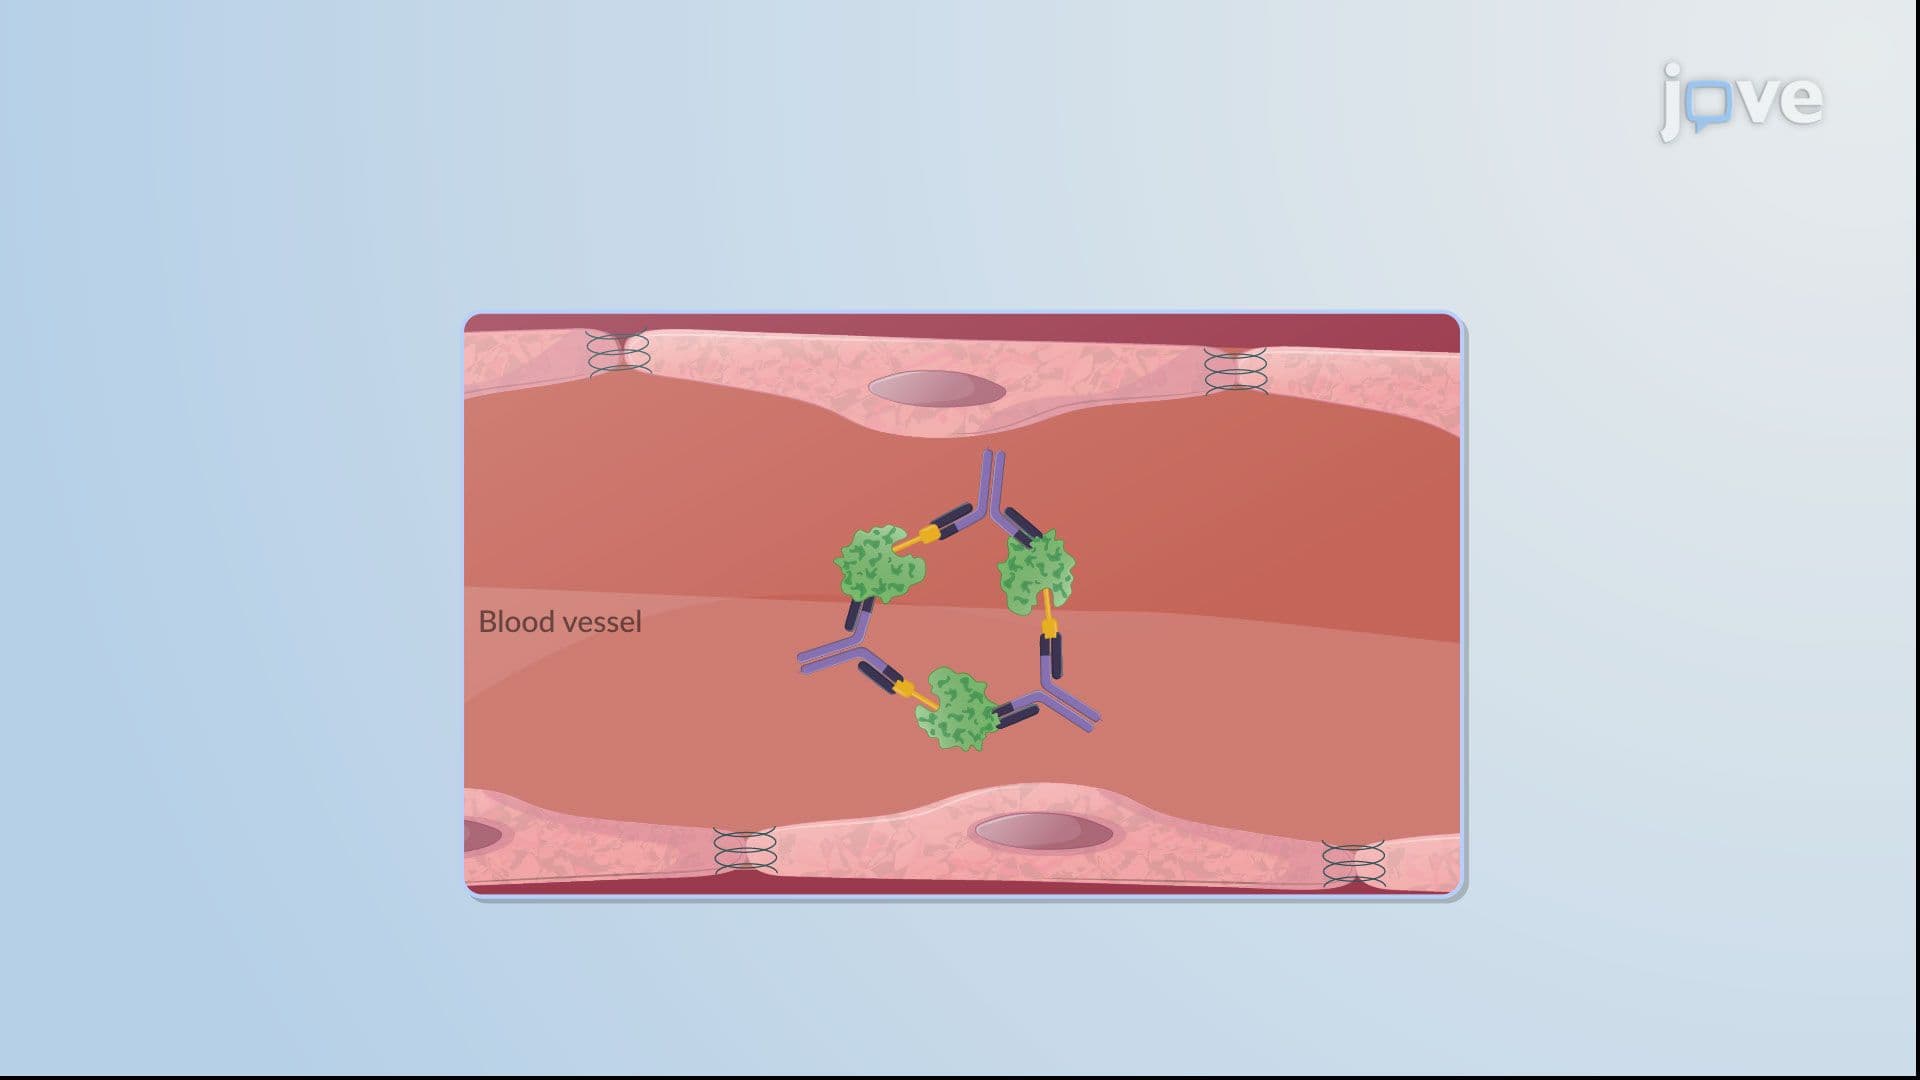
Hypersensitivity Reactions: Immune-Complex Reactions