Related Experiment Video
Updated: Jul 6, 2025
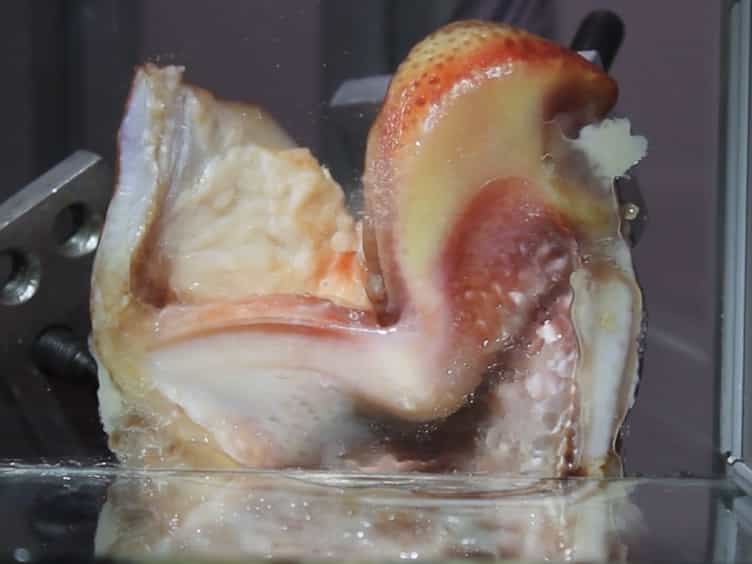

Hemi-laryngeal Setup for Studying Vocal Fold Vibration in Three Dimensions
Published on: November 25, 2017
Relationships Between Vocal Fold Adduction Patterns, Vocal Acoustic Quality, and Vocal Effort in Individuals With and
Caroline Crocker1, Laura E Toles2, Robert A Morrison3
1School of Behavioral and Brain Sciences, Callier Center for Communication Disorders, University of Texas at Dallas, Richardson, Texas.

Objectives/Hypothesis:
Increased vocal effort and aberrant vocal quality are often attributed to vocal fold hyperadduction in hyperfunctional voice disorders. However, there are currently no established methods to quantify vocal fold adduction beyond subjective descriptors in this clinical population. Furthermore, relationships between vocal fold adduction patterns, vocal effort severity, and vocal quality are not well characterized. Therefore, the objectives of this study were to (1) quantify vocal fold adduction, applying a previously validated method developed for patients with vocal fold paralysis, and (2) correlate these measures with acoustic vocal quality and self-perceived measures of vocal effort severity.
Methods:
A deep learning program, Automated Glottic Action Tracking using artificial Intelligence, was used to track glottic angle configurations and vocal fold adduction velocities on laryngoscopic videos across 60 laryngoscopies (20 primary muscle tension dysphonia [pMTD], 20 phonotraumatic lesions, and 20 healthy controls). Voice samples were also acquired, and cepstral peak prominence (CPP) and H1-H2 acoustic measures were used to quantify vocal quality. Participants were also asked to rate their vocal effort on a 100 mm visual analog scale.
Results:
There were no significant group differences in glottic angle configurations or vocal fold adduction velocities, although there were trends toward increased peak vocal fold adduction velocities in patients with hyperfunctional voice disorders compared to controls. Vocal effort was significantly higher in the two hyperfunctional groups compared to controls. CPP was significantly lower in the pMTD group, but there were no group differences in acoustic parameters between any of the other groups or for H1-H2 values.
Conclusion:
Despite significantly more vocal effort reported in patients with hyperfunctional voice disorders, there were no significant group differences in vocal fold adduction patterns. These findings suggest other physiologic mechanisms may also be responsible for the symptoms and genesis of pMTD and benign vocal fold lesions.


Related Concept Videos
 01:21
Larynx
Anatomy of the Larynx
The larynx consists of various components, including cartilage, muscles, and vocal cords. Its structure includes three large unpaired cartilages—the thyroid, cricoid, and epiglottis—and three smaller paired cartilages—the arytenoids,...
 01:30
Assessment of Airway, Skin Color, and Use of Accessory Muscles
Introduction
The initial evaluation of a patient's respiratory system...
 01:31
Respiratory System Abnormal Finding II: Palpation and Auscultation
Palpation Findings
During a respiratory assessment, palpation can reveal several vital abnormalities:
 01:28
Physical Assessment of the Respiratory Tract IV: Auscultation
Breath Sounds
Breath sounds are categorized into vesicular, bronchovesicular, and bronchial.
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement:
 01:19
Factors Affecting Pulmonary Ventilation
Alveolar Surface Tension
The alveolar fluid lines the luminal surface of the alveoli and exerts a force called surface tension. This force is caused by the polar water molecules in the liquid being more strongly attracted to each...