Related Experiment Video
Updated: Jul 5, 2025
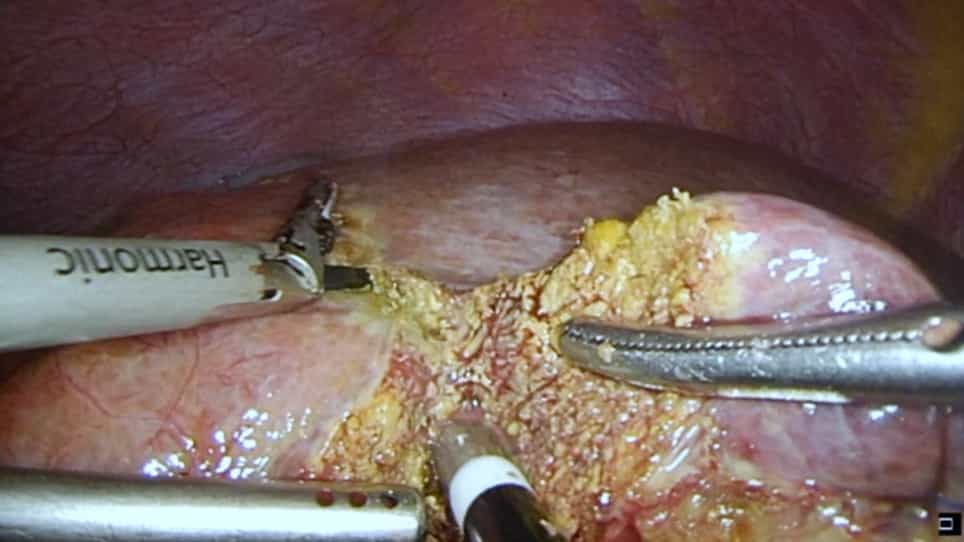

Application of Hemostatic Devices in Laparoscopic Hepatectomy
Published on: April 19, 2022
Establishing the clinical relevance of grade A post-hepatectomy liver failure
Dominic J Vitello1, Dhavan Shah1, Bona Ko1
1Department of Surgery, Northwestern University Feinberg School of Medicine, Chicago, Illinois, USA.

Introduction:
The International Study Group of Liver Surgery's criteria stratifies post-hepatectomy liver failure (PHLF) into grades A, B, and C. The clinical significance of these grades has not been fully established.
Methods:
The American College of Surgeons National Surgical Quality Improvement Program (ACS NSQIP) hepatectomy-targeted database was analyzed. Outcomes between patients without PHLF, with grade A PHLF, and grade B or C PHLF were compared. Univariate and multivariable logistic regression were performed.
Results:
Six thousand two hundred seventy-four adults undergoing elective major hepatectomy were included in the analysis. The incidence of grade A PHLF was 4.3% and grade B or C was 5.3%. Mortality was similar between patients without PHLF (1.2%) and with grade A PHLF (1.1%), but higher in those with grades B or C PHLF (25.4%). Overall morbidities rates were 19.3%, 41.7%, and 72.8% in patients without PHLF, with grade A PHLF, and with grade B or C PHLF, respectively (p < 0.001). Grade A PHLF was associated with increased morbidity (grade A: odds ratios [OR] 2.7 [95% CI: 2.0-3.5]), unplanned reoperation (grade A: OR 3.4 [95% CI: 2.2-5.1]), nonoperative intervention (grade A: OR 2.6 [95% CI: 1.9-3.6]), length of stay (grade A: OR 3.1 [95% CI: 2.3-4.1]), and readmission (grade A: OR 1.8 [95% CI: 1.3-2.5]) compared to patients without PHLF.
Conclusions:
Although mortality was similar between patients without PHLF and with grade A PHLF, other postoperative outcomes were notably inferior. Grade A PHLF is a clinically distinct entity with relevant associated postoperative morbidity.


