Related Experiment Video
Updated: Jul 2, 2025


Evaluation of Patients' Posture and Gait Profile After Lumbar Fusion Surgery by Video Rasterstereography and Treadmill Gait Analysis
Published on: March 23, 2019
A Geometrical Explanation for Change in Pelvic Tilt (or Lack of Change) Following Long Spinal Fusions
Gautham Prabhakar1, Michael P Kelly2, Ezekial Koslosky1
1Department of Orthopaedics, University of Texas Health Science Center at San Antonio, San Antonio, TX.

Study Design:
Retrospective cohort.
Objective:
Examine the relationship between compensatory pelvic retroversion, positive sagittal imbalance (measured by C2 tilt), and the C2 pelvic angle (C2PA) in patients before long spinal fusions; and to determine the association between changes in C2PA and pelvic tilt (PT) following long spinal fusions.
Background:
Adult spinal deformity surgical goals often include a PT target, yet patients frequently demonstrate persistent compensatory pelvic retroversion following surgery.
Methods:
Adults above 18 years old undergoing long spinal fusions (>4 levels) with standing preoperative and postoperative radiographs were included. To examine drivers of preoperative sagittal balance, regression models were fit to estimate the association between preoperative C2PA and pelvic incidence with preoperative PT and C2 tilt. To predict postoperative change in PT, multivariable regression was used to estimate change in PT, adjusting for change in C2PA and preoperative C2 tilt.
Results:
Among the 80 patients identified, the median age was 61 (IQR: 45-72) and 46 (58%) were female. The median number of levels fused was 10 (IQR: 8-13) and 55 (69%) were instrumented to the sacrum/pelvis. Preoperative C2PA had a significant nonlinear association with preoperative PT ( r2 =0.81, P <0.001) and preoperative C2 tilt ( r2 =0.41, P =0.002). Postoperative change in PT was strongly associated with change in C2PA (β=0.81; P <0.001) and preoperative C2 tilt (β=0.55; P <0.001).
Conclusions:
Following long spinal fusions, change in PT (or lack thereof) can be reliably predicted based on change in C2PA and preoperative C2 tilt. In patients with normal preoperative C2 tilt, the change in C2PA is nearly equivalent to the change in PT, but in patients with more positive C2 tilt (sagittal imbalance), a greater change in C2PA will be required to achieve an equivalent change in PT.
Level Of Evidence:
3.
More Related Videos
 07:41
Quantification of Levator Ani Hiatus Enlargement by Magnetic Resonance Imaging in Males and Females with Pelvic Organ Prolapse
Published on: April 17, 2019
 08:38
Three-dimensional Navigation-guided, Prone, Single-position, Lateral Lumbar Interbody Fusion Technique
Published on: July 15, 2021
Related Concept Videos
 01:16
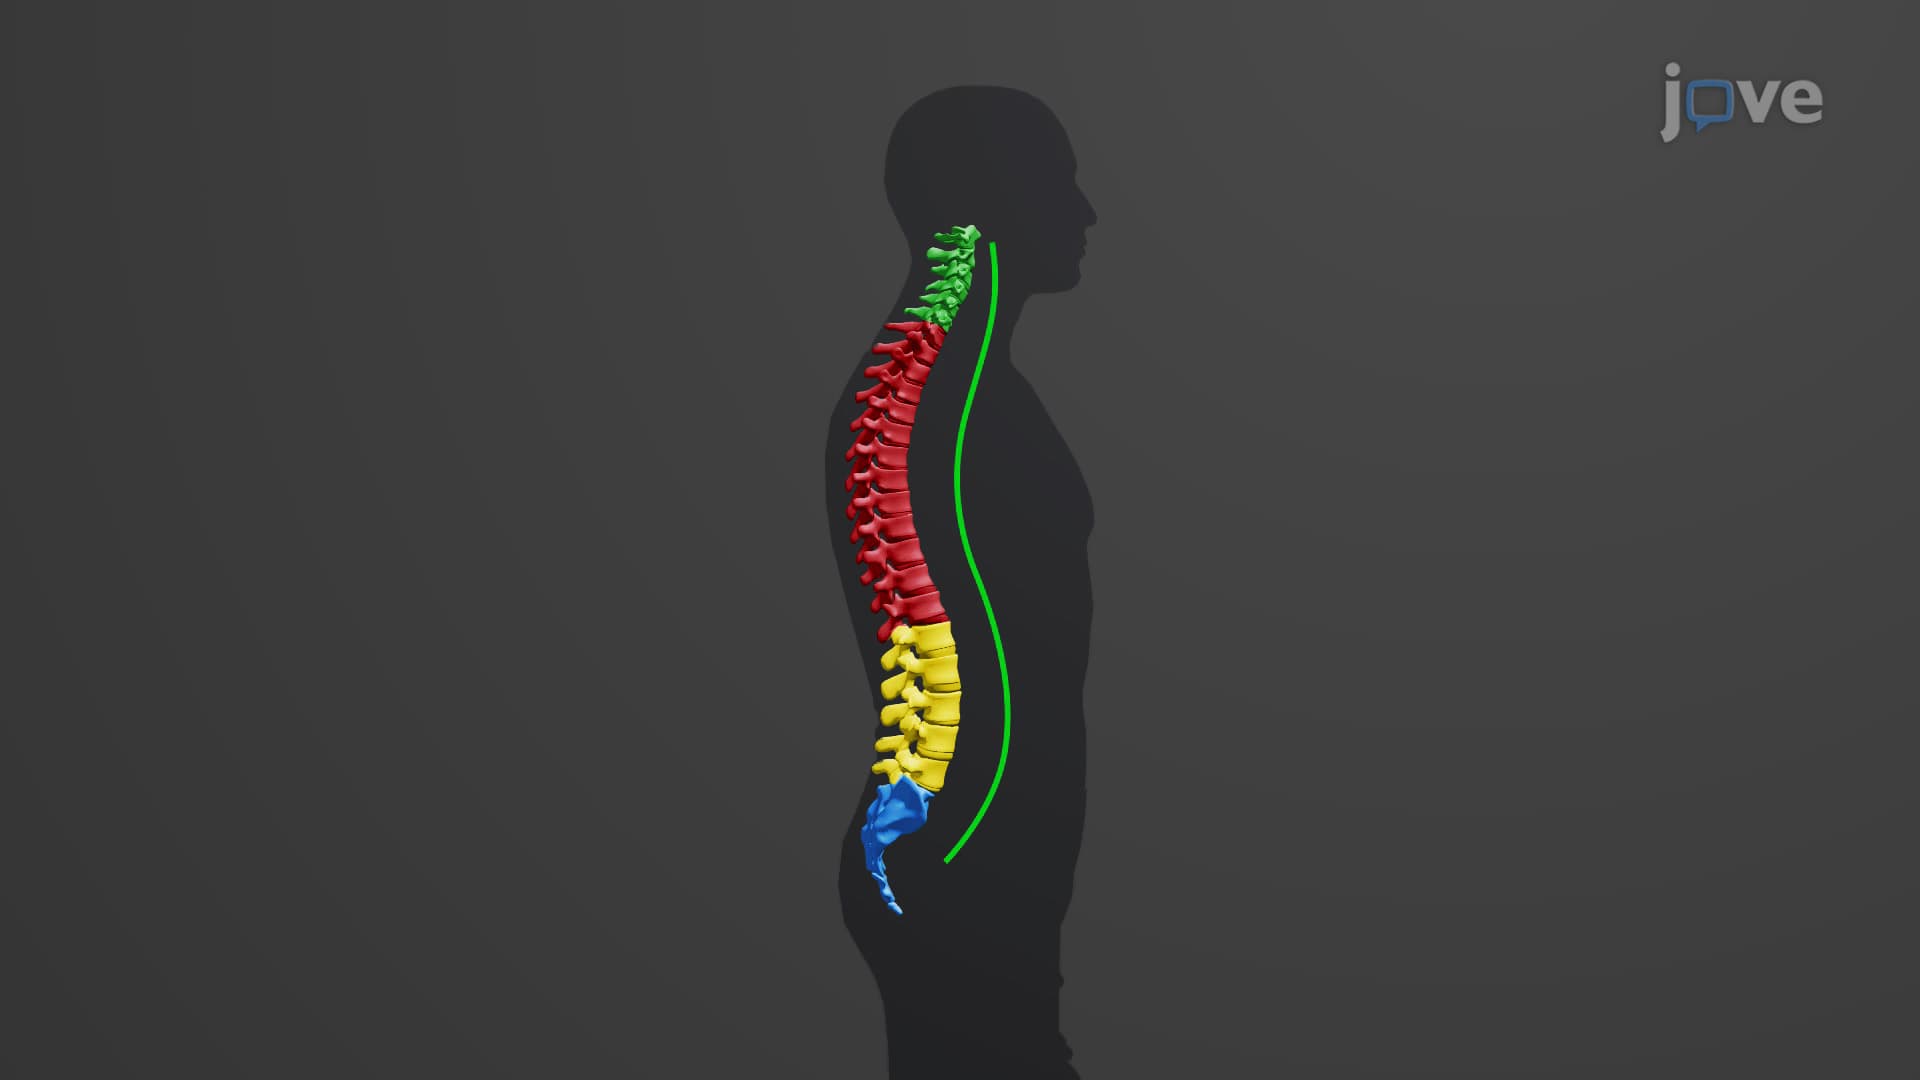
Vertebral Column: Regions and Curvature
Regions of the Vertebral Column
In an adult, the spine is subdivided into five regions: the cervical, the thoracic, the lumbar, the sacral, and the coccygeal region. The spine initially develops as a series of 33 vertebrae; after 20 years of age, the nine bones in the sacral region, five sacral, and four coccygeal bones fuse to form...
 01:26
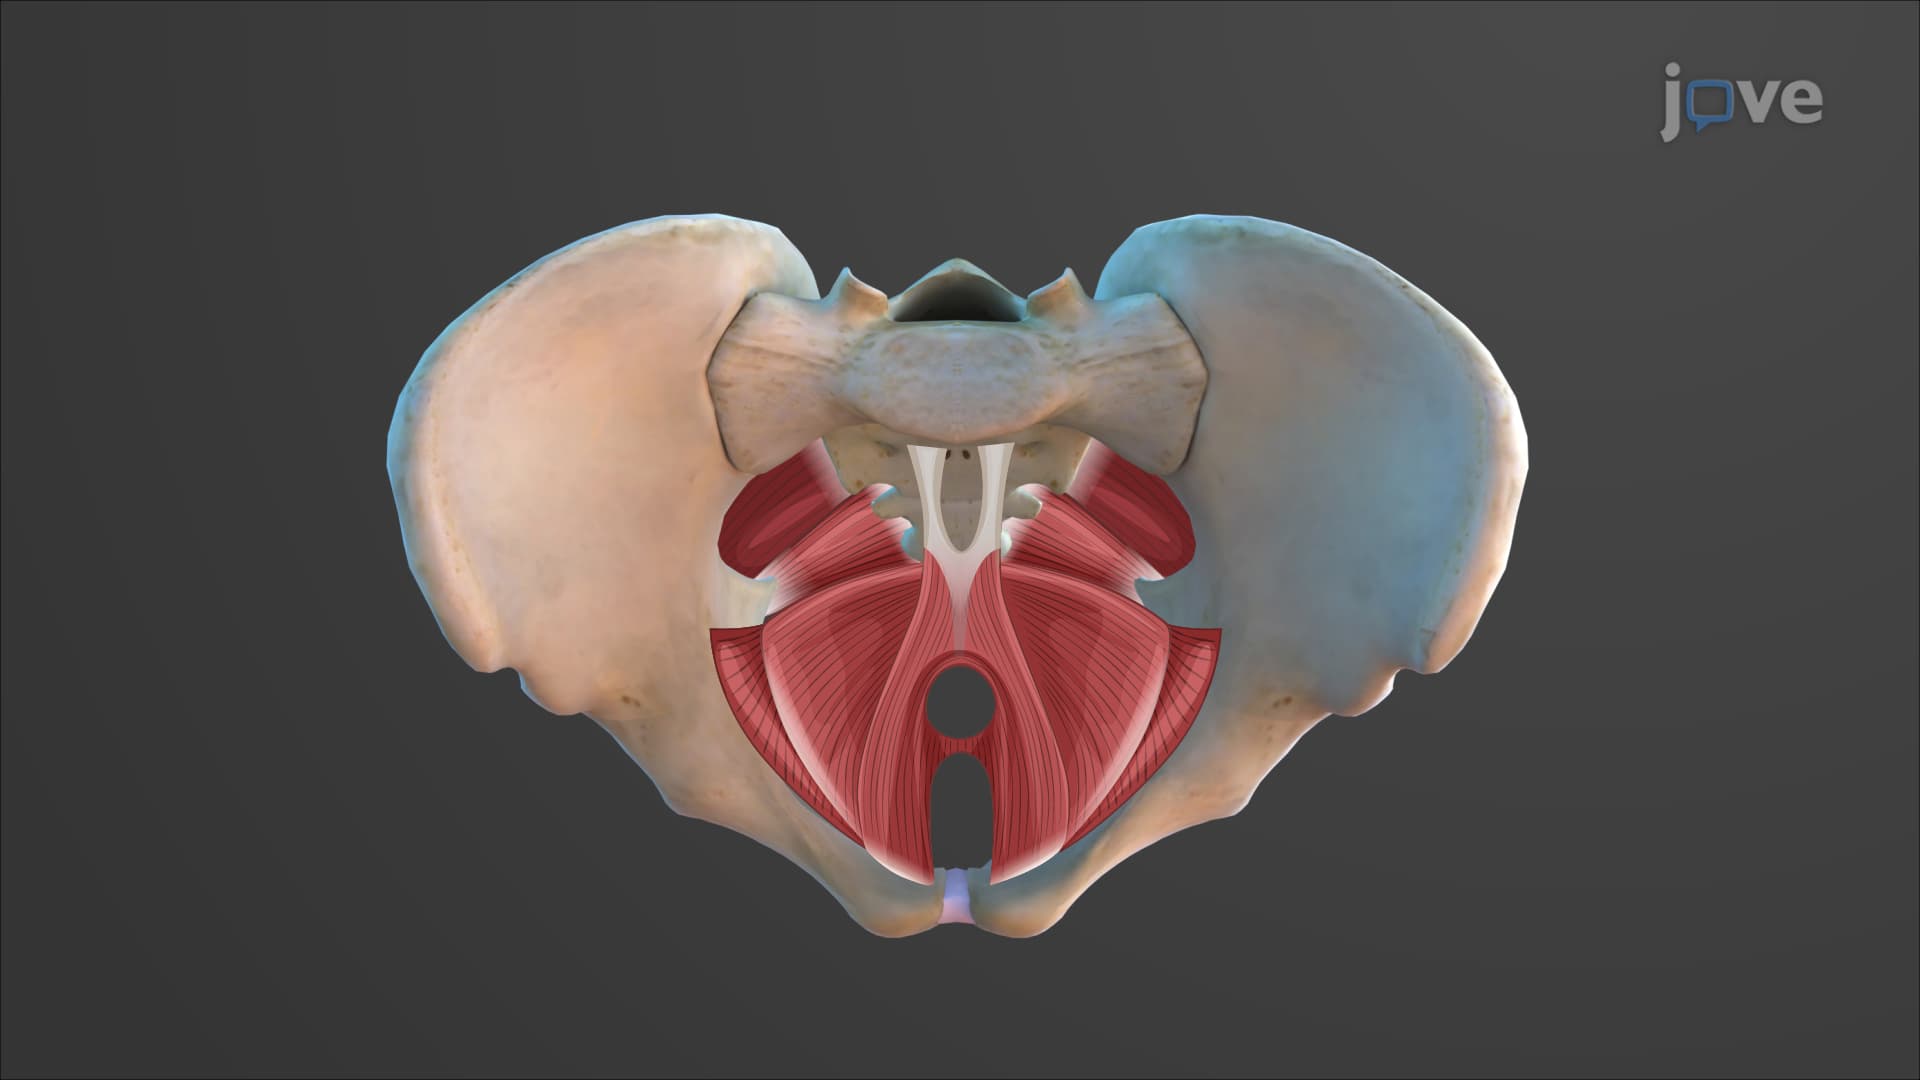
Muscles of the Pelvic Floor and Perineum
Perineal Layer
The perineum is a diamond-shaped area below the pelvic diaphragm, divided into an anterior urogenital triangle that contains the external genitals and a posterior anal triangle housing the anus. The urogenital...
 01:11
Anatomical Positions
The body is upright, facing forward, and standing erect.
The feet are parallel and flat on the floor.
The arms are hanging by the...
 01:30
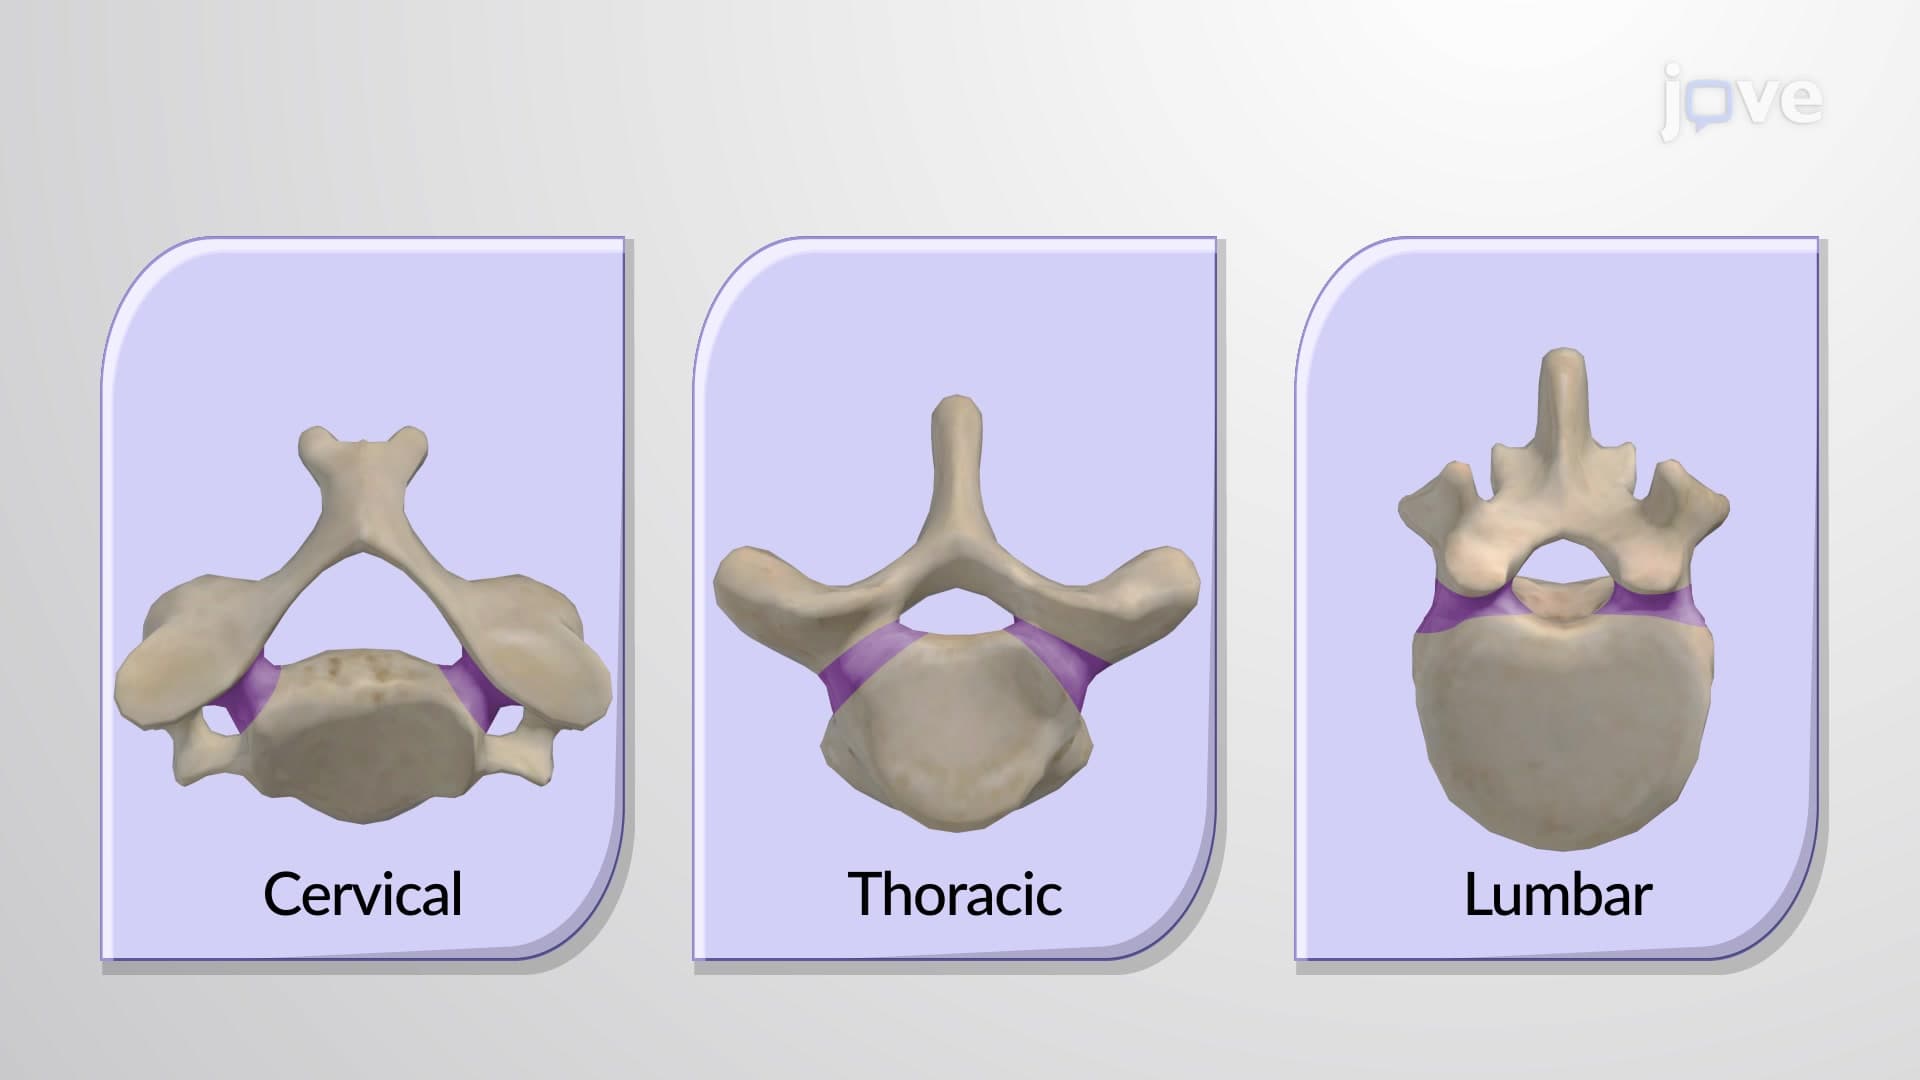
General Structure of a Vertebra