
Severe Left Main Coronary Artery Stenosis and Aortic Regurgitation in a Patient Presenting with Takayasu Arteritis
Akiko Tanihata1, Atsushi Shibata1, Kazutoshi Teragaki1
1Department of Cardiovascular Medicine, Osaka Metropolitan University Graduate School of Medicine, Japan.

Insights
Takayasu arteritis (TA) can cause severe coronary artery stenosis. Surgical intervention for left main coronary artery stenosis in TA patients should be considered only after successful anti-inflammatory treatment resolves inflammation.
Area of Science:
- Cardiology
- Immunology
- Vascular Surgery
Background:
- Takayasu arteritis (TA) is a large vessel vasculitis.
- TA can lead to stenosis in major arteries, including the coronary arteries.
- Coronary artery stenosis poses significant risks, including myocardial infarction.
Observation:
- A 46-year-old woman presented with TA, severe left main coronary artery (LMCA) stenosis, and severe aortic regurgitation.
- Initial medical therapy with prednisolone and tacrolimus improved aortic regurgitation but not LMCA stenosis.
- Following confirmed resolution of inflammation, coronary artery bypass grafting was performed without aortic valve intervention.
Findings:
- Anti-inflammatory therapy can improve TA-related aortic regurgitation.
- Surgical management of LMCA stenosis in TA requires prior successful anti-inflammatory treatment.
- Coronary artery bypass grafting alone can be effective after medical management of TA.
Implications:
- This case highlights the importance of managing inflammation in TA before surgical intervention for coronary stenosis.
- Optimal timing for surgical intervention in TA patients with LMCA stenosis is crucial.
- A multidisciplinary approach involving cardiology, rheumatology, and surgery is essential for managing complex TA cases.
Abstract:
We herein report the case of a 46-year-old woman with Takayasu arteritis (TA), severe stenosis in the left main coronary artery (LMCA), and severe aortic regurgitation. Prednisolone and tacrolimus were initiated as TA treatments. Two months after initiating medical therapy, the aortic regurgitation severity improved to a moderate grade, although there was no obvious improvement in LMCA stenosis. Thus, after confirming the resolution of inflammation, we performed coronary artery bypass grafting alone without any aortic valve intervention. In TA patients with severe LMCA stenosis, surgical management of the coronary artery should therefore be considered only after successfully administering anti-inflammatory therapy.

Related Concept Videos
 01:26
Imbalances in Cardiac Output
CHF can occur due to the failure of either side of the heart. Left-side failure leads to pulmonary congestion—the right side continues to send...
 01:25
Cardiovascular System Abnormal Findings II: Auscultation
Abnormal Heart Sounds
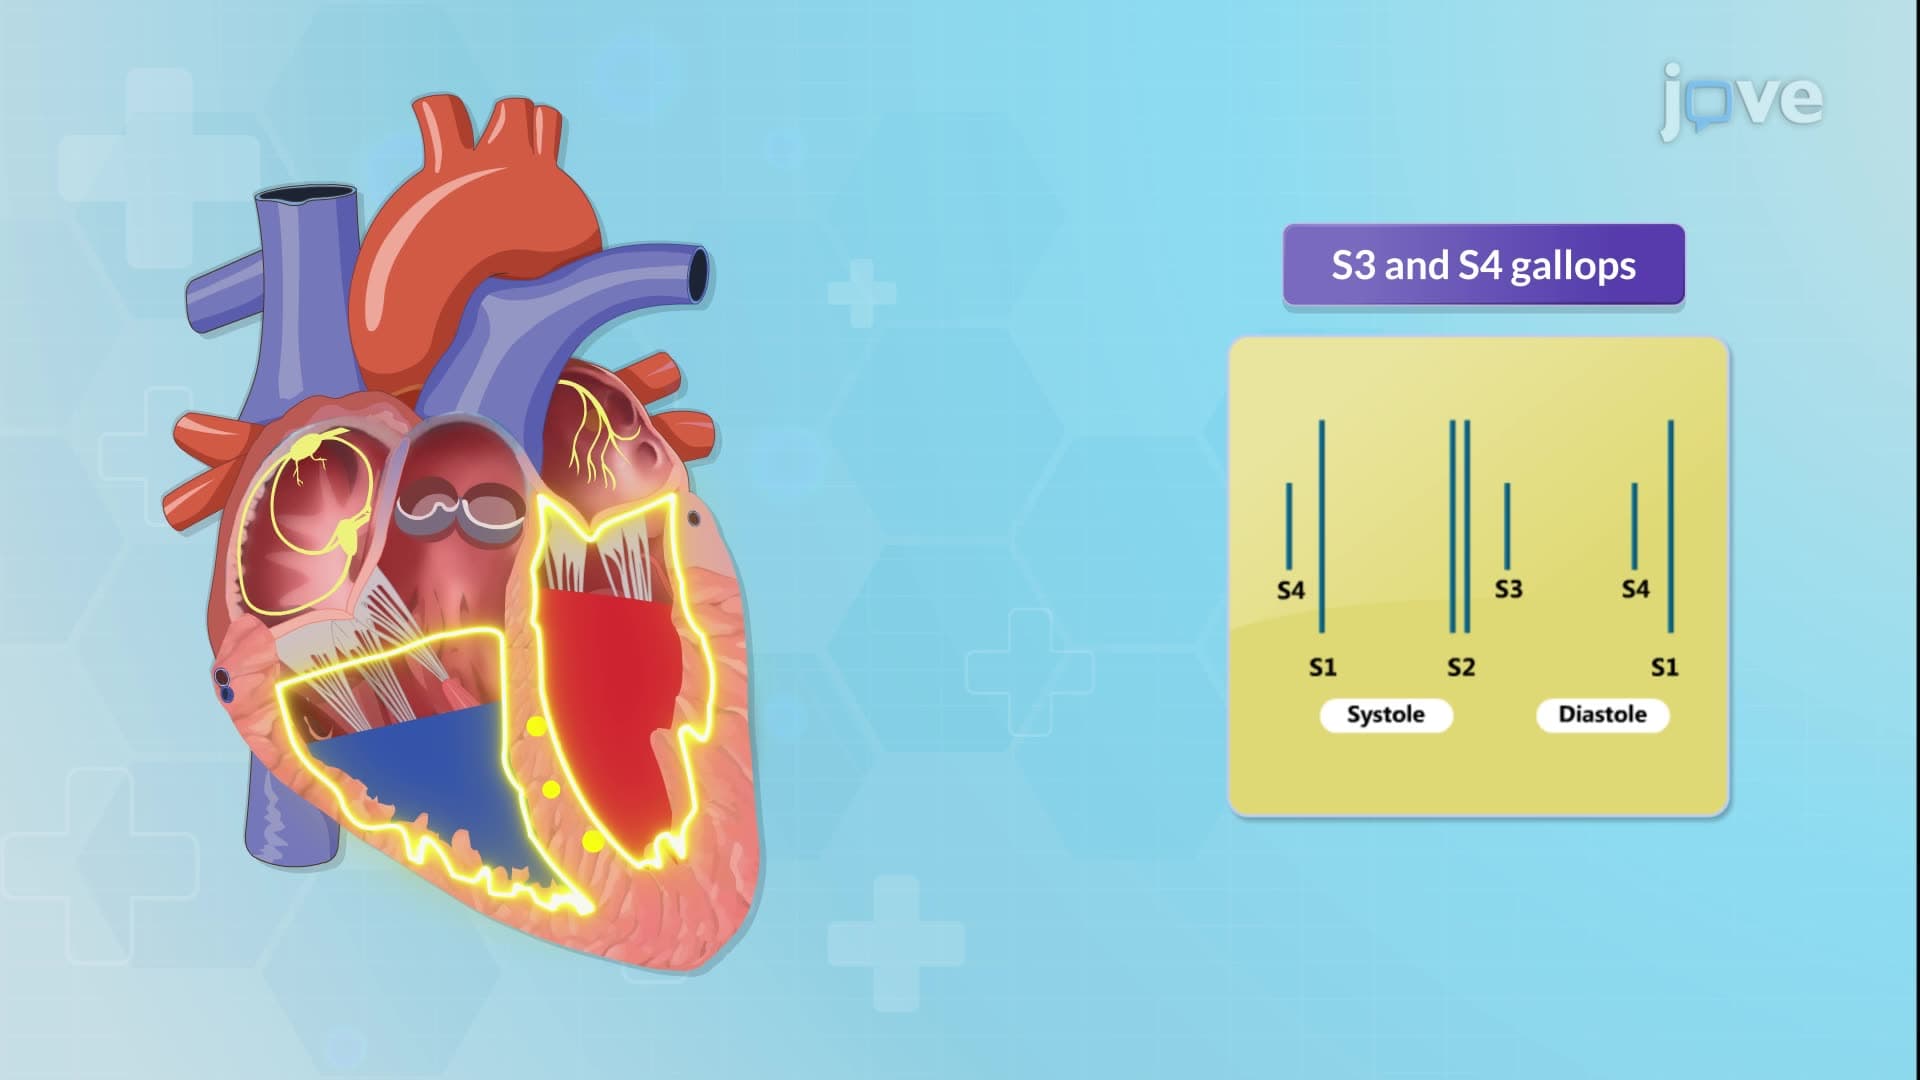
Gallops: