Related Experiment Video
Updated: Jul 1, 2025
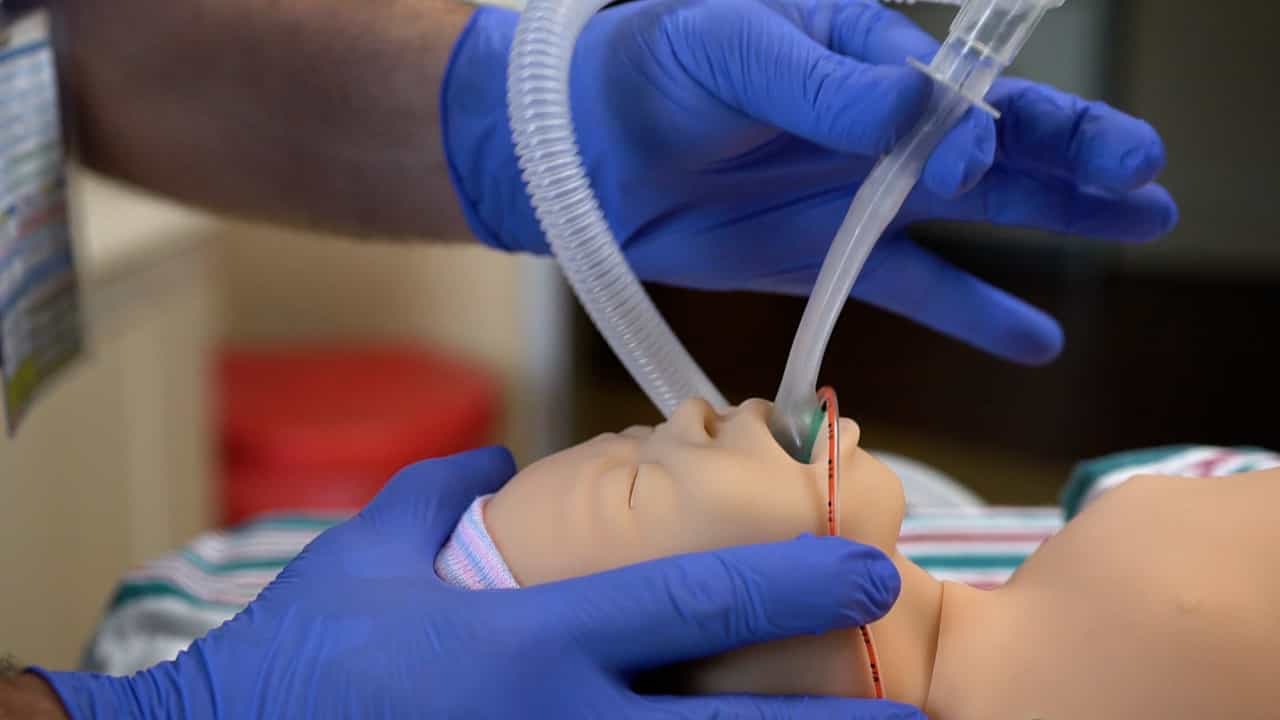

Laryngeal Mask Airway LMA Placement in a Neonatal Patient Simulator Using a Non-Inflatable Supraglottic Airway SGA
Published on: July 14, 2023
Airway Management During Diagnostic Laparoscopic Surgery: A Comparison of I-Gel and Proseal Laryngeal Mask Airway
Muhammad Sule1, Dalhat Salahu2, Mamuda Atiku2
1Department of Anaesthesia, Muhammad Abdullahi Wase Teaching Hospital, Kano, Nigeria.

Background:
Supraglottic airway devices (SADs) may be used during laparoscopic procedures in place of the often utilised endotracheal tube. The Proseal laryngeal mask airway (PLMA) is designed with an inflatable cuff, which provides an excellent oropharyngeal seal, and the I-gel is a newer SAD designed with a softer and noninflatable cuff and sharing similar features with PLMA.
Aim And Objectives:
This study compared the ease of insertion, haemodynamic and ventilatory parameters as well as morbidities associated with these SADs when used for airway management during diagnostic laparoscopic procedures.
Patients And Methods:
Eighty American Society of Anaesthesiologist I and II patients aged 18-60 years undergoing diagnostic laparoscopic surgery under controlled ventilation had either I-gel or PLMA used for airway management. Anaesthesia was induced with standard dose of propofol, patient received atracurium, fentanyl and the SAD inserted. Pulse oximetry, capnography, noninvasive blood pressure, oropharyngeal leak pressure (OLP), and evidence of pharyngolaryngeal morbidity were assessed. Data were analysed using the Statistical Package for Social Sciences version 21.0. The quantitative variables were analysed using the Student's t test and the qualitative using the Chi-square test. A P value of less than 0.05 was considered significant.
Results:
The success rates at first insertion for I-gel and PLMA were 95% and 80%, respectively (P = 0.04). The mean changes in mean arterial pressure following insertion were 9.6 mmHg (±4.7) and 10.6 mmHg (±8) for I-gel and PLMA, respectively (P = 0.02). The OLP during insufflation was higher in the PLMA (35.8 cmH2O) than in the I-gel group (27.9 cmH2O) (P = 0.57). In the I-gel group, 12.5% of the patients had oropharyngeal morbidities compared with 37.5% in the PLMA group (P = 0.009).
Conclusion:
Both I-gel and PLMA provide optimal ventilation during abdominal insufflation, with PLMA providing a better oropharyngeal seal, whereas I-gel has a better haemodynamic profile.
More Related Videos
 05:39
Author Spotlight: A Non-Intubated Video-Assisted Thoracoscopic Surgery with Multimodal Analgesia and Sevoflurane Inhalation Anesthesia
Published on: May 26, 2023
 03:58
Author Spotlight: Advancing Awake Nasotracheal Intubation with Flexible Video Rhino-Laryngoscopes
Published on: August 2, 2024
Related Concept Videos
 01:16
Tracheostomy Care I: Pre-procedural Steps
Required Equipment
The equipment necessary for tracheostomy care includes:
 01:26
Endoscopic Procedures IV: Sigmoidoscopy and Laproscopy
Sigmoidoscopy
Sigmoidoscopy is a diagnostic procedure that uses a flexible sigmoidoscope equipped with a light source and camera to examine the rectum and sigmoid colon. The procedure involves inserting the tube through the anus...
 01:25
Tracheostomy Care II: Procedure
Step 1: Perform hand hygiene, and put on personal protective equipment: gown, gloves, mask...
 01:26
Tracheostomy Suctioning I: Pre-Procedural Steps
Equipment Required
First, gather all necessary equipment: a sterile suction catheter, a sterile disposable container, sterile gloves, a towel or...
 01:15
Endotracheal Intubation I: Procedure
The ET tube comprises various components, including a standard adaptor to attach a bag-valve-mask (BVM) or ventilator, a cuff, a pilot balloon, and radiopaque markings along its length to measure the insertion distance. The tube sizes...