Related Experiment Video
Updated: Jul 1, 2025

Methods for In Vivo Biomechanical Testing on Brachial Plexus in Neonatal Piglets
Published on: December 19, 2019
Peripheral nerve decompression for pain relief in the setting of previous obstetrical brachial plexus injury: a
Jessica Gormley1, Pavlo Isak2, Deborah Gjertsen3
1Division of Plastic Surgery, Department of Surgery, McMaster University, 1280 Main Street West, Hamilton, ON, L8S 4L8, Canada. jessica.gormley@medportal.ca.

Insights
Peripheral nerve decompression and neurolysis significantly reduced upper extremity pain in children with obstetrical brachial plexus injury (OBPI). This treatment also modestly improved range of motion, suggesting nerve compression as a pain source.
Area of Science:
- Pediatric Orthopedics
- Neurology
- Surgical Innovation
Background:
- Upper extremity pain affects 45-66% of children with obstetrical brachial plexus injury (OBPI).
- Pain is often characterized as musculoskeletal or neuropathic.
- Effective treatments for OBPI-related pain remain an area of investigation.
Purpose of the Study:
- To evaluate the efficacy of peripheral nerve decompression and neurolysis for upper extremity pain in OBPI patients.
- To determine if surgical intervention can alleviate pain associated with previous OBPI.
- To explore neurolysis and decompression as a treatment for OBPI-related pain.
Main Methods:
- Retrospective chart review of patients who underwent peripheral nerve decompression and neurolysis following OBPI.
- Assessment of pain reduction and improvement in wrist and elbow range of motion.
- Preoperative and follow-up outcome measures were analyzed.
Main Results:
- Six pediatric patients with OBPI underwent nerve decompression (median, ulnar, or posterior interosseous nerves).
- All patients experienced substantial pain improvement, with resolution of subjective pain and Tinel's sign.
- A modest improvement in range of motion was observed postoperatively.
Conclusions:
- Peripheral nerve decompression and neurolysis show promise in improving pain and range of motion in a subset of OBPI patients.
- The findings suggest that peripheral nerve compression may be a significant source of pain in this population.
- Further research with larger cohorts is warranted to confirm these results and explore treatment options.
Purpose:
In children with previous obstetrical brachial plexus injury (OBPI), upper extremity pain is present in 45 to 66% of patients. Recent literature reports this as musculoskeletal or neuropathic in nature. The purpose of the study is to demonstrate that peripheral nerve decompression, and neurolysis may be an effective treatment for patients with upper extremity pain in the context of previous OBPI.
Methods:
A retrospective chart review was performed on patients undergoing peripheral nerve decompression and neurolysis after OBPI by senior author. The primary outcome assessed was pain, and secondary outcome measure was range of motion of the wrist and elbow. Outcome measures were assessed preoperatively as well as at their subsequent follow-up.
Results:
Six patients were included, with a mean age of 14 years old at time of decompression. Three patients underwent median nerve, two patients underwent ulnar nerve, and one patient underwent posterior interosseous nerve decompression. There was a substantial improvement in pain post-operatively, demonstrated by reduction or resolution of subjective pain in all patients and resolution of Tinel's sign. There was a modest improvement in range of motion.
Conclusion:
This study demonstrates an improvement in subjective pain and range of motion after decompression and neurolysis in small subset of OBPI patients. It generates the hypothesis that peripheral nerve compression is a source of pain that can be addressed in this population. Future research should focus on confirming this hypothesis and assessing treatment options on a larger scale.
More Related Videos
 09:14
Surface Electromyographic Biofeedback as a Rehabilitation Tool for Patients with Global Brachial Plexus Injury Receiving Bionic Reconstruction
Published on: September 28, 2019
 03:24
Author Spotlight: Development and Application of a Novel Suture Technique for Annular Fibrosus Repair in Percutaneous Transforaminal Endoscopic Discectomy
Published on: January 26, 2024
Related Concept Videos
 01:22
Spinal Nerves: Plexus I
The Cervical Plexus
The cervical plexus, formed by the anterior rami of the first four...
 01:21
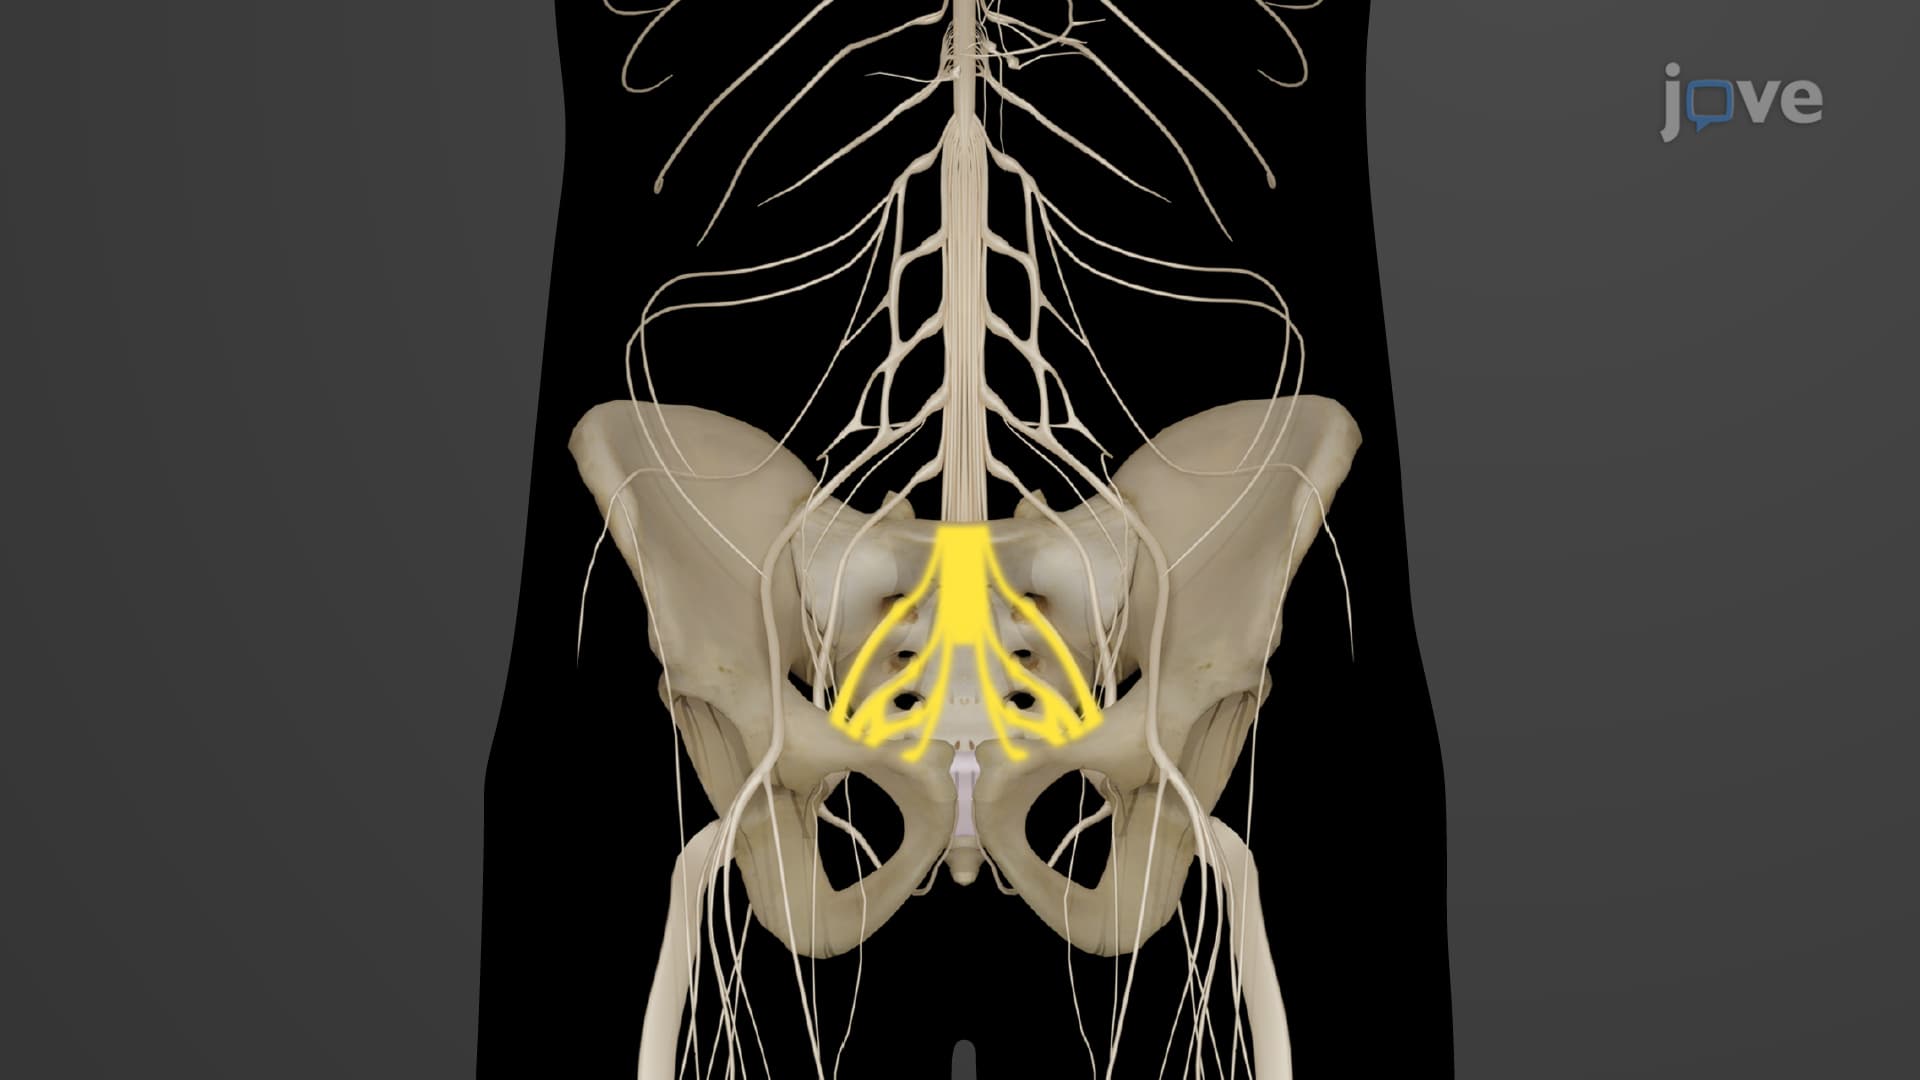
Spinal Nerves: Plexus II
The Lumbar Plexus
The lumbar plexus is situated within the lumbar region of the back and is primarily formed by the first four lumbar spinal nerves (L1 to L4). This plexus extends its branches into several nerves, including the...
 01:16
Local Anesthetics: Clinical Application as Intravenous Regional Anesthesia
One of the advantages of...