Related Experiment Video
Updated: Jul 1, 2025


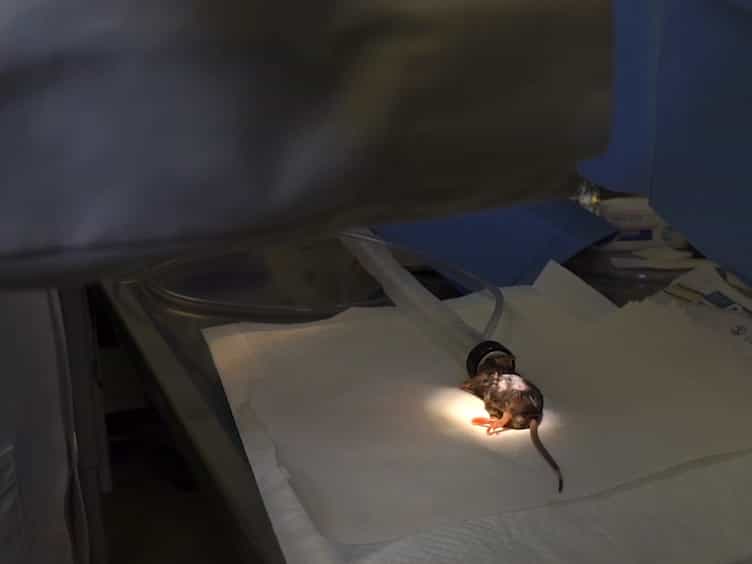
5/6th Nephrectomy in Combination with High Salt Diet and Nitric Oxide Synthase Inhibition to Induce Chronic Kidney Disease in the Lewis Rat
Published on: July 3, 2013
Guideline directed medical therapy induced nephrotoxicity in HFrEF patients; an insight to its mechanism
Anu Philip1, Prarambh S R Dwivedi2, C S Shastry1
1Department of Pharmacy Practice, NGSM Institute of Pharmaceutical Sciences (NGSMIPS), Nitte (Deemed to be University), Mangalore, India.

Insights
Guideline Directed Medical Therapy (GDMT) for heart failure may cause kidney damage. This study used systems biology to identify specific drug combinations and molecular targets, like HBA1 and CBR1, linked to potential nephrotoxicity.
Area of Science:
- Cardiology
- Pharmacology
- Nephrology
- Computational Biology
- Systems Biology
Background:
- Guideline Directed Medical Therapy (GDMT) is the standard pharmacotherapy for Heart Failure with reduced Ejection Fraction (HFrEF).
- European Society of Cardiology (ESC) guidelines recommend specific GDMT combinations.
- Nephrotoxicity is a potential adverse effect of GDMT in HFrEF patients.
Purpose of the Study:
- To predict the molecular mechanisms underlying GDMT-induced nephrotoxicity.
- To identify specific GDMT drug combinations and molecular targets associated with nephrotoxicity.
Main Methods:
- Utilized systems biology tools including ADVER-Pred, gene enrichment analysis, molecular docking, and molecular dynamic simulations.
- Categorized GDMT into three groups based on ACC/AHA/ESC guidelines.
- Analyzed protein-protein interaction networks to identify hub genes and binding affinities.
Main Results:
- Gene enrichment analysis indicated that Category 2 drugs (β-blockers, SGLT2 inhibitors, ARNI) showed the highest association with nephrotoxicity (79.41%).
- Top hub genes identified include HBA1, CBR1, ATG5, and SLC6A3.
- Molecular docking revealed high binding affinity between candesartan and SLC6A3 (-10.2 kcal/mol), and molecular dynamics simulations showed stability for empagliflozin-CBR1 and candesartan-ATG5 interactions.
Conclusions:
- A combination of β-blockers, Angiotensin Receptor Blockers (ARBs), and Sodium-Glucose Cotransporter-2 Inhibitors (SGLT2I) may lead to nephrotoxicity.
- The identified molecular targets (HBA1, CBR1, ATG5, GPX1) are implicated in the nephrotoxic effects.
- Candesartan and empagliflozin are predicted to be the most likely culprits for nephrotoxicity via modulation of these specific genes.
Abstract:
Guideline Directed Medical Therapy (GDMT) has been the standard pharmacotherapy for the treatment of Heart Failure patients with reduced Ejection Fraction (HFrEF) recommended by the European Society of Cardiology (ESC). However, patients on GDMT are likely to possess nephrotoxicity as an adverse effect. We utilized multiple system biology tools like ADVER-Pred, gene enrichment analysis, molecular docking, molecular dynamic simulations, and MMPBSA analysis to predict a possible molecular mechanism of how selected combinations of GDMT may cause nephrotoxicity. As per the ACC/AHA/ESC guidelines, we categorized the drugs as category 1 including β-blockers (BB), angiotensin receptor blockers (ARB), and sodium-glucose cotransporter-2 inhibitors (SGLT2I), category 2 includes BB's, SGLT2I, and angiotensin receptor-neprilysin inhibitors (ARNI), and category 3 includes BB's, SGLT2I, and angiotensin-converting enzyme (ACE) inhibitors. Enrichment analysis predicted category 2 drugs to possess the highest number of proteins to be involved in the development of nephrotoxicity i.e. 79.41%. The targets HBA1, CBR1, ATG5, and SLC6A3 were the top hub genes with an edge count of 7 followed by GPX1 with an edge count of 6. Molecular docking studies revealed candesartan-SLC6A3 to possess the highest binding affinity of -10.2 kcal/mol. In addition, simulation studies displayed empagliflozin-CBR1 to possess the highest stability followed by candesartan-ATG5. A combination of β-blockers, ARBs, and SGLT2I are predicted to likely possess nephrotoxicity which may be due to the modulation of HBA1, CBR1, ATG5, and GPX1. In conclusion, candesartan and empagliflozin are most likely to cause nephrotoxicity via the modulation of HBA1, CBR1, ATG5, and GPX1.

Related Concept Videos
 01:26
Heart Failure Drugs: Inhibitors of Renin-Angiotensin System
 01:22
Heart Failure Drugs: Diuretics
 01:11
Renal Failure: Dose Adjustments
Reduced renal clearance and elimination rate are common outcomes of renal impairment. These alterations lead to a prolonged elimination half-life and an altered apparent volume of distribution for drugs. As a result, dosage adjustments are typically necessary to maintain optimal drug levels in the body.
However, dosage adjustments...
 01:26
Heart Failure Drugs: Inotropic Agents
 01:17
Pathophysiology of Heart Failure
 01:25
Antihypertensive Drugs: Direct Renin Inhibitors