Related Experiment Video
Updated: Jun 30, 2025


Utilizing Percutaneous Ventricular Assist Devices in Acute Myocardial Infarction Complicated by Cardiogenic Shock
Published on: June 12, 2021
Sex-Related Differences in Patient Characteristics, Hemodynamics, and Outcomes of Cardiogenic Shock: INOVA-SHOCK
Kelly C Epps1, Behnam N Tehrani1, Carolyn Rosner1
1Inova Heart and Vascular Institute, Falls Church, Virginia.

Insights
In patients with cardiogenic shock (CS) treated via a standardized team-based approach (STBA), women presented with higher acuity but experienced similar mortality and adverse events compared to men. This suggests STBA may mitigate historical sex-based outcome disparities in CS.
Area of Science:
- Cardiology
- Clinical Medicine
- Sex Differences in Health
Background:
- Limited understanding of sex-related disparities in cardiogenic shock (CS) outcomes.
- Investigating outcomes within a standardized team-based approach (STBA) is crucial.
Purpose of the Study:
- To evaluate sex-based differences in outcomes for patients with CS.
- To assess the impact of STBA on mitigating potential sex disparities in CS patients.
Main Methods:
- Retrospective analysis of 520 consecutive CS patients (acute myocardial infarction [AMI] or heart failure [HF]) from January 2017 to December 2019.
- Examination of in-hospital mortality, major adverse cardiac events, 30-day mortality, bleeding, vascular complications, and stroke stratified by sex and CS phenotype.
- Statistical analysis to identify sex-related differences and independent predictors of outcomes.
Main Results:
- Women with AMI-CS and HF-CS presented with higher acuity and cardiac arrest rates, respectively.
- No significant sex differences in in-hospital mortality or 1-year survival were observed for either AMI-CS or HF-CS.
- Women with HF-CS had higher rates of major bleeding and vascular complications, but female sex was not an independent predictor.
Conclusions:
- STBA may mitigate historical sex-based outcome disparities in CS patients, as women experienced similar mortality despite higher acuity.
- Further research is warranted to confirm the effectiveness of STBA in addressing sex differences in CS.
- Sex-specific considerations within STBA may still be necessary for complications like bleeding and vascular events.
Background:
Little is known about sex-related differences in outcomes of patients with cardiogenic shock (CS) treated within a standardized team-based approach (STBA).
Methods:
We evaluated 520 consecutive patients (151 women and 369 men) with CS due to acute myocardial infarction (AMI) and heart failure (HF) in a single-center registry (January 2017-December 2019) and examined outcomes according to sex and CS phenotype. The primary outcome was in-hospital mortality. Secondary outcomes included major adverse cardiac events, 30-day mortality, major bleeding, vascular complications, and stroke.
Results:
Women with AMI-CS had higher baseline acuity (CardShock score: female [F]: 5.5 vs male [M]: 4.0; P = .04). Women with HF-CS more often presented with cardiac arrest (F: 12.4% vs M: 2.4%; P< .01) and had higher rates of vasopressor use (F: 70.8% vs M: 58.0%; P = .04) and mechanical circulatory support (F: 46.1% vs M: 32.5%; P = .04). There were no sex-related differences in in-hospital mortality for AMI-CS (F: 45.2% vs M: 36.9%; P = .28) and HF-CS (F: 28.1% vs M: 24.5%; P = .56). Women with HF-CS experienced higher rates of major bleeding (F: 25.8% vs M: 13.7%; P = .02) and vascular complications (F: 15.7% vs M: 6.1%; P = .01). However, female sex was not an independent predictor of these complications. No sex differences in survival were noted at 1 year.
Conclusions:
Within an STBA, although women with AMI-CS and HF-CS presented with higher acuity, they experienced similar in-hospital mortality, major adverse cardiac events, 30-day mortality, stroke, and 30-day readmissions as men. Further research is needed to better understand the extent to which historical differences in CS outcomes can be mitigated by an STBA.


Related Concept Videos
 01:24
Blood Pressure Imbalances and Circulatory Shock
Blood Pressure: Hypertension and Hypotension
Normal blood pressure is 120/80 mm Hg. Elevated blood pressure is 120-129/under 80 mm Hg. Hypertension, warranting treatment at 130/80 mm Hg, is often asymptomatic and can lead to severe cardiovascular events, aneurysms, peripheral arterial disease, chronic renal disease, or cardiac...
 01:26
Imbalances in Cardiac Output
CHF can occur due to the failure of either side of the heart. Left-side failure leads to pulmonary congestion—the right side continues to send...
 01:22
Cardiac Output II: Effect of Stroke Volume on Cardiac Output
Preload
Preload refers to the initial elongation of the cardiac myocytes before contraction and is related to the volume of blood filling the heart at the end of diastole, or end-diastolic volume. The...
 01:19
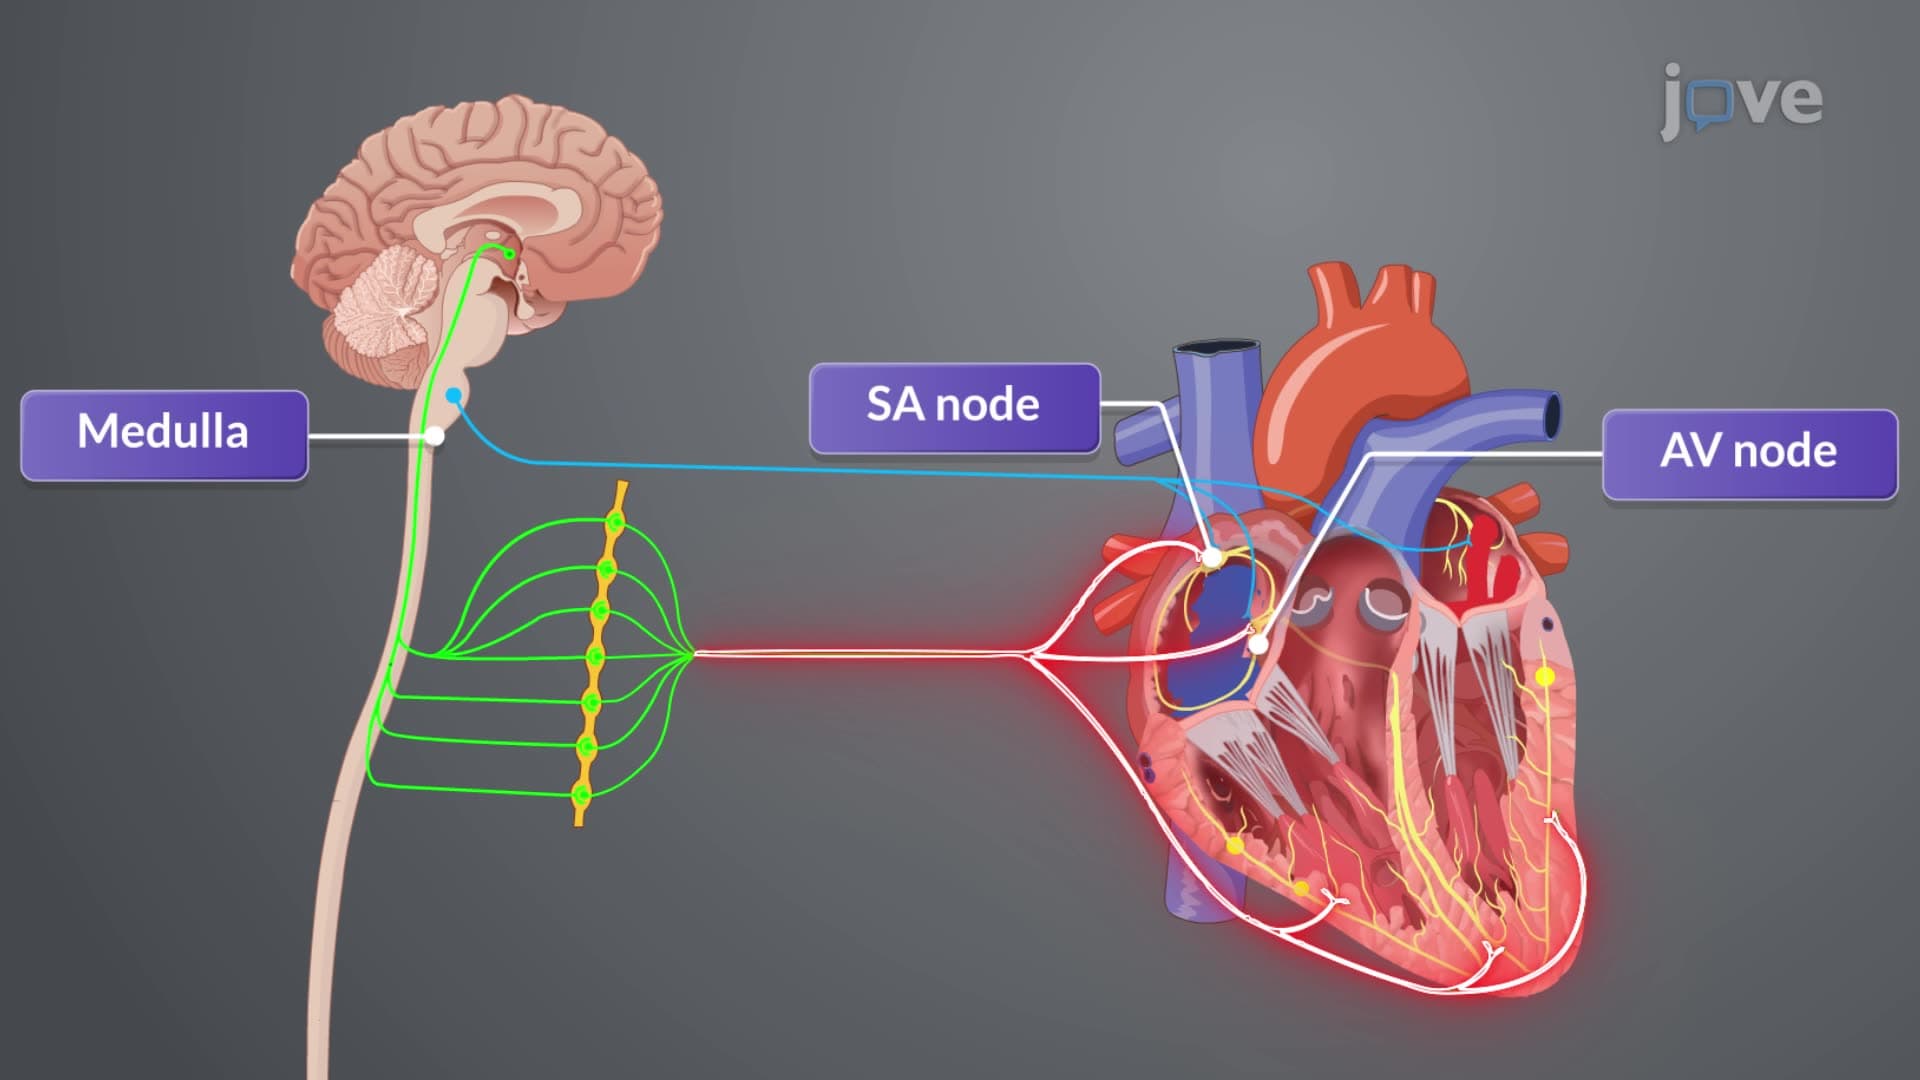
Cardiac Output I:Effect of Heart Rate on Cardiac Output
Cardiac output (CO) refers to the total amount of blood ejected by one of the ventricles in liters per minute (L/min). In a resting adult, CO ranges from 5 to 6 L/min, adjusting according to the body's metabolic requirements.
Effect of Heart Rate on Cardiac Output
Cardiac output adapts to metabolic demands during stress, physical activity, or illness. The autonomic nervous system regulates heart rate via the sinoatrial node. The parasympathetic nervous system decreases heart...
 01:17
Ischemic Heart Disease: Overview
Atherosclerosis, the primary malefactor, orchestrates this dangerous condition. It manifests as the accumulation of fatty deposits, akin to insidious plaques, within arterial walls. As time elapses, these plaques metamorphose, hardening and...
 01:20
Blood Studies for Cardiovascular System I: Cardiac Biomarkers
The essential diagnostic tools for detecting myocardial necrosis and monitoring individuals suspected of having acute coronary syndrome (ACS) include:
Troponins
Troponins, particularly cardiac troponins I and T, are the most precise and sensitive markers of myocardial injury. They are detectable within 4-6 hours of myocardial injury and remain...