Related Experiment Video
Updated: Jun 29, 2025
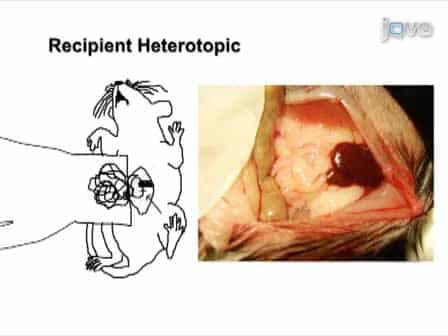
Heterotopic and Orthotopic Tracheal Transplantation in Mice used as Models to Study the Development of Obliterative Airway Disease
Published on: January 20, 2010
Successful Postnatal Tracheobronchoplasty for Unilateral Congenital High Airway Obstruction Syndrome due to Mainstem
Timothy M Crombleholme1,2, Jennifer D Smith3, Reenu Eapen2
1Fetal Care Center at Connecticut Children's and the Division of Pediatric General, Thoracic, and Fetal Surgery, Department of Surgery, University of Connecticut School of Medicine, Hartford, Connecticut, USA.

Introduction:
Unilateral congenital high airway obstruction syndrome (CHAOS) is caused by a complete obstruction of a mainstem bronchus with resulting hyperinflation and accelerated growth of one lung, severe mediastinal shift, and hydrops. Spontaneous perforation of the atresia has been observed in CHAOS which allows hydrops to resolve but hyperinflation, mediastinal shift and a critical airway obstruction persists as the perforation is usually pinhole-sized.
Case Presentation:
We present a case of unilateral CHAOS presenting at 26 2/7 weeks with observed-to-expected total lung volume (O/E TLV) of 203% with spontaneous perforation occurring at 28 weeks with resolution of hydrops but persistence of hyperinflation and mediastinal shift with an O/E TLV of 60.5% on 34 5/7 weeks' magnetic resonance imaging (MRI), successfully managed in a 35 5/7 weeks, 1,670 gm, growth restricted baby, by venoarterial extracorporeal membrane oxygenation (VA ECMO) and resection of the tracheobronchial atresia and tracheobronchoplasty on day of life 5. The baby was separated from ECMO on post-op day 12, required tracheostomy for positive end expiratory pressure for tracheomalacia at 4 months.
Conclusion:
At 2 years of age, she has met all developmental milestones, has been weaned to room air tracheostomy collar, and has been anticipating tracheal decannulation. There is persistent bronchiectasis in the hyperinflated right lung but no malacia. This is the first reported survivor of mainstem bronchial atresia suggesting the importance of preservation of the hyperplastic lung and airway reconstruction to normal long-term outcome.


Related Concept Videos
 01:22
Trachea
Anatomical Features:
Location: About half of the trachea is situated in the neck, anterior to the esophagus, and extends from the larynx (at the level of...
 01:28
Tracheostomy: Procedure and Tubes
Tracheostomy tubes can be made of semiflexible plastic (polyurethane or silicone), rigid plastic, or metal, and they come in...
 01:21
Tracheostomy Decannulation
Description of the Procedure
Decannulation refers to the permanent removal of the tracheostomy tube, signaling the resolution of the condition that initially necessitated the tracheostomy. The process requires a well-coordinated interplay between...
 01:23
Oxygen Delivering System III: Tracheostomy and T-piece
Tracheostomy
A tracheostomy is a surgically created opening (stoma) in the anterior part of the trachea. It is used to establish a patient airway, bypass an upper airway obstruction, simplify the removal of secretions, permit long-term...
 01:16
Tracheostomy Care I: Pre-procedural Steps
Required Equipment
The equipment necessary for tracheostomy care includes:
 01:16
Oxygen Delivering System II: Venturi Mask and Transtracheal Oxygen
Venturi Mask
The Venturi mask, named after the Venturi effect, is designed to deliver precise oxygen concentrations. It consists of a large tube with an oxygen inlet that narrows down, causing a pressure drop that pulls air in through adjustable side ports. The mask is a lightweight,...