Related Experiment Video
Updated: Jun 29, 2025


Author Spotlight: Advancing Early Detection and Treatment of Gastrointestinal Tumors
Published on: February 16, 2024
Long-term endoscopic change of gastric polyp associated with administration of vonoprazan
Yorinari Ochiai1, Shinji Ito2, Daisuke Kikuchi3
1Department of Gastroenterology, Toranomon Hospital, Tokyo, 105-8470, Japan. y.ochiai.1987@gmail.com.

Abstract:
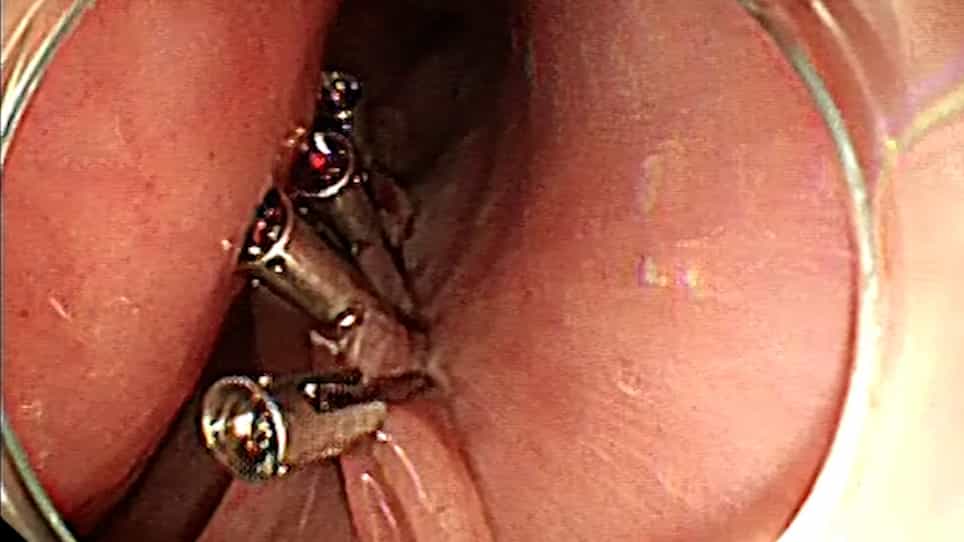
Vonoprazan (VPZ) has been available in Japan since 2015. Endoscopic features of proton-pump inhibitor (PPI)-related gastric mucosal changes, including fundic gland and hyperplastic polyps, have been observed. However, the relationship between gastric polyps and VPZ remains unclear. A 65-year-old man with reflux esophagitis-associated symptoms refractory to PPI was referred to our hospital. VPZ (20 mg) was administered for 3 weeks, which proved effective. Afterward, VPZ dose was reduced to 10 mg; the reflux symptoms worsened, and 20 mg VPZ was restarted. Afterward, esophagogastroduodenoscopy (EGD) revealed a gradually enlarging gastric polyp in the cardia. After 5 years of VPZ administration, the patient developed a reddish polyp (approximately 10 mm) with a whitish substance in the cardia. Based on the clinical course, the polyp was considered to have enlarged because of the long-term VPZ administration. After being informed of the endoscopic findings, the patient decided to discontinue VPZ. One year after VPZ discontinuation, EGD revealed a shrunken polyp (5 mm). Long-term acid suppression causes hypergastrinemia, which may lead to gastric mucosal changes, including gastric polyps. There are few case reports of a decrease in the number and size of gastric polyps after VPZ discontinuation. Hence, some VPZ-induced endoscopic changes may be reversible.
Related Concept Videos
 01:30
Peptic Ulcer Disease I: Introduction
An acute ulcer, marked by superficial erosion and minimal inflammation, swiftly resolves upon identifying and addressing the underlying cause. In contrast, a chronic ulcer persists, potentially eroding through the muscular wall and forming fibrous tissue.
Peptic ulcers can also be...
 01:21
Barrett Esophagus-II: Clinical Manifestations and Management
To diagnose Barrett's esophagus, healthcare providers often recommend an endoscopy for those showing symptoms of acid reflux. The procedure...
 01:26
Peptic Ulcer Disease IV: Management
The therapeutic approach involves ensuring adequate rest, implementing drug therapy, promoting smoking cessation, making dietary modifications, and emphasizing long-term follow-up care.
Pharmacological management
The prevailing therapy for peptic ulcers involves a combination of managing the patient's current...
 01:28
Peptic Ulcer Disease III: Clinical Manifestations and Diagnostic Studies
Few clinical manifestations differentiate gastric ulcers from duodenal ulcers. Distinctions in the location, timing, and pain relief are crucial for healthcare providers in differentiating between gastric and duodenal ulcers during clinical assessments.
 01:21
Barrett Esophagus-I: Introduction
This constant acid exposure transforms the esophagus's pink mucosal lining (stratified squamous epithelium) into a type of lining more...
 01:29
Endoscopic Procedures I: Esophagogastroduodenoscopy
During an EGD, the endoscope can be used to: