Related Experiment Video
Updated: Jun 29, 2025


Recognition of Epidermal Transglutaminase by IgA and Tissue Transglutaminase 2 Antibodies in a Rare Case of Rhesus Dermatitis
Published on: December 15, 2011
A case of IgA pemphigus with acantholysis in oral mucosal lesions
Ayumi Yamanishi1, Noriko Ono1, Asako Tsunoda1
1Department of Dermatology Keio University School of Medicine Tokyo Japan.

Abstract:
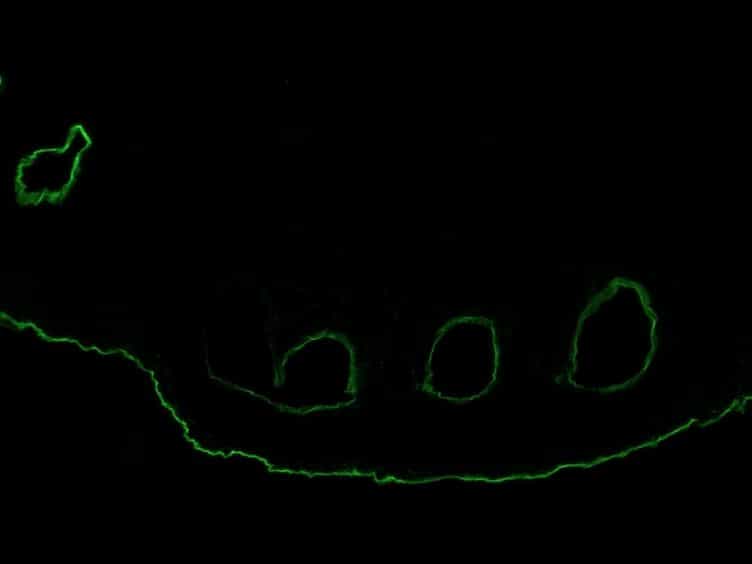
IgA pemphigus is an autoimmune bullous disease caused by anti-keratinocyte cell surface IgA autoantibodies. Mucous membrane involvement is rare in IgA pemphigus. We report a case of IgA pemphigus with oral mucosal lesions, in which acantholysis was pathologically confirmed. A 31-year-old woman presented with skin erythema with small pustules and oral mucosal erosions. Histopathological examination of the erosions on her oral mucosa and papules on her back revealed acantholysis and intraepidermal infiltration of neutrophils. Direct immunofluorescence tests showed intercellular deposition of IgA, but not IgG, mainly in the lower, but not entire, layer of the epidermis. C3 was linearly present in the basement membrane zone (BMZ), but not in the intercellular space. Enzyme-linked immunosorbent assay revealed that both anti-desmoglein (Dsg) 3 IgA and IgG were positive. Neither IgA nor IgG against desmocollin 1-3 were detected. This case was clinically and histologically compatible with IgA pemphigus, but immunologically anti-BMZ autoimmunity was additionally observed. IgA pemphigus is classified into two major types: subcorneal pustular dermatosis type and intraepidermal neutrophilic dermatosis type. This case was not typical in terms of rarely observed oral lesions and predominant deposition of IgA in the lower layer of the epidermis. Instead, this case could be considered a rare subtype of IgA pemphigus, IgA-pemphigus vulgaris. Oral lesions in IgA pemphigus may be clinical clue of having anti-Dsg3 IgA that cannot be routinely examined.

Related Concept Videos
 01:17
Gastritis-II: Pathophysiology
In acute gastritis, the gastric mucosa becomes swollen and red and undergoes superficial erosion. Superficial ulceration may lead to bleeding.
In chronic gastritis, persistent or repeated insults lead to chronic inflammatory changes and, eventually, thinning or atrophy of the gastric tissue.
Gastritis can stem from various causes, each...
 01:23
Gastritis III: Clinical Manifestations and Management
Clinical manifestations of acute gastritis
The patient with acute gastritis may have a rapid onset of symptoms, such as epigastric pain or discomfort, dyspepsia, anorexia, hiccups, or nausea and vomiting, which can last from a few hours to a few days. Erosive or hemorrhagic gastritis may cause bleeding, which may manifest as blood in vomit or as...
 01:28
Peptic Ulcer Disease III: Clinical Manifestations and Diagnostic Studies
Few clinical manifestations differentiate gastric ulcers from duodenal ulcers. Distinctions in the location, timing, and pain relief are crucial for healthcare providers in differentiating between gastric and duodenal ulcers during clinical assessments.
 01:30
Peptic Ulcer Disease I: Introduction
An acute ulcer, marked by superficial erosion and minimal inflammation, swiftly resolves upon identifying and addressing the underlying cause. In contrast, a chronic ulcer persists, potentially eroding through the muscular wall and forming fibrous tissue.
Peptic ulcers can also be...
 01:30
Inflammatory Bowel Disease II: Crohn's Disease
Inflammatory bowel disease, commonly known as IBD, refers to a collection of disorders that lead to persistent inflammation of the gastrointestinal tract. The two types of IBD are ulcerative colitis, which impacts the colon, and Crohn's disease, which can involve any part of the gastrointestinal segment.
Crohn's disease
Crohn's disease is a chronic, systemic inflammatory bowel disease (IBD) that predominantly affects the gastrointestinal tract. It is marked by...
 01:28
Peptic Ulcer Disease II: Pathophysiology
Damaging agents such as Helicobacter pylori, gastric acid, pepsin, and nonsteroidal anti-inflammatory drugs (NSAIDs) can weaken the mucosal defense, allowing hydrogen ions to infiltrate back and harm epithelial cells.