Why Kinematic Alignment Makes Little Sense in Valgus Osteoarthritis of the Knee: A Narrative Review
Related Experiment Video
Updated: Jun 29, 2025
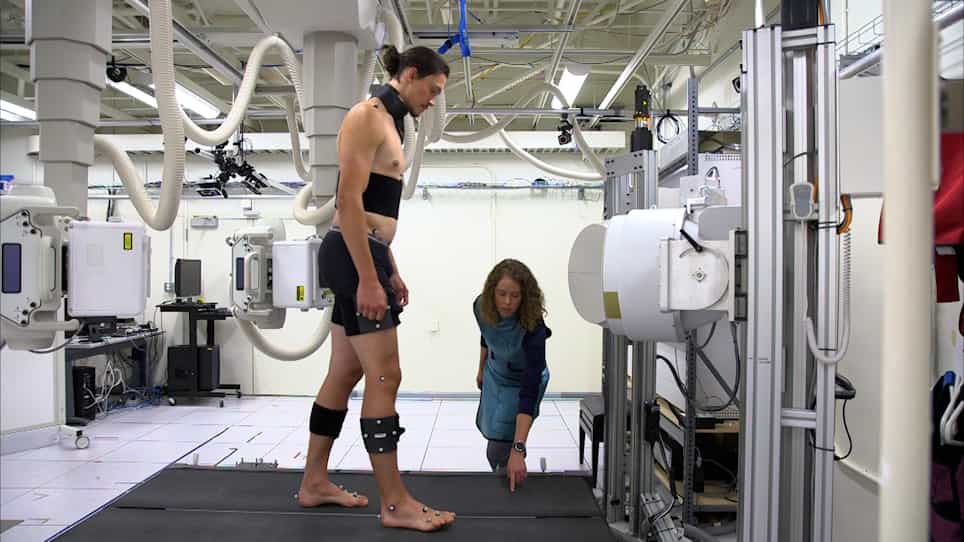
In Vivo Quantification of Hip Arthrokinematics during Dynamic Weight-bearing Activities using Dual Fluoroscopy
Published on: July 2, 2021
Christian Manuel Sterneder1, Martin Faschingbauer2, Lyubomir Haralambiev3
1Adult Reconstruction and Joint Replacement Department, Hospital for Special Surgery, 535 East 70th Street, New York, NY 10021, USA.

Abstract:
There is a debate about the best alignment strategies in total knee arthroplasty (TKA). Mechanical alignment (MA) targets in combination with necessary soft tissue releases are the gold standard for TKA in end-stage valgus osteoarthritis. Some authors propagate kinematic alignment (KA) with the aim of restoring the patient's native alignment and minimizing the need for soft tissue releases. Our previous studies showed that MA with standardized soft tissue release produces reproducible results, and that the preoperative phenotype does not influence the results of patients with valgus osteoarthritis. These data suggest that there is no functional advantage to preserving valgus alignment in patients with valgus osteoarthritis. Many patients with valgus osteoarthritis present with a compromised medial collateral ligament and leaving the knee in valgus could increase the risk of secondary instability. The current literature supports MA TKA with soft tissue release as the gold standard. While using more sophisticated enabling technologies like robotic surgery might allow for aiming for very slight (1-2°) valgus alignment on the femoral side, any valgus alignment outside this range should be avoided. This review paper summarizes our current knowledge on the surgical techniques of TKA in patients with valgus osteoarthritis.