Related Experiment Video
Updated: Jun 28, 2025
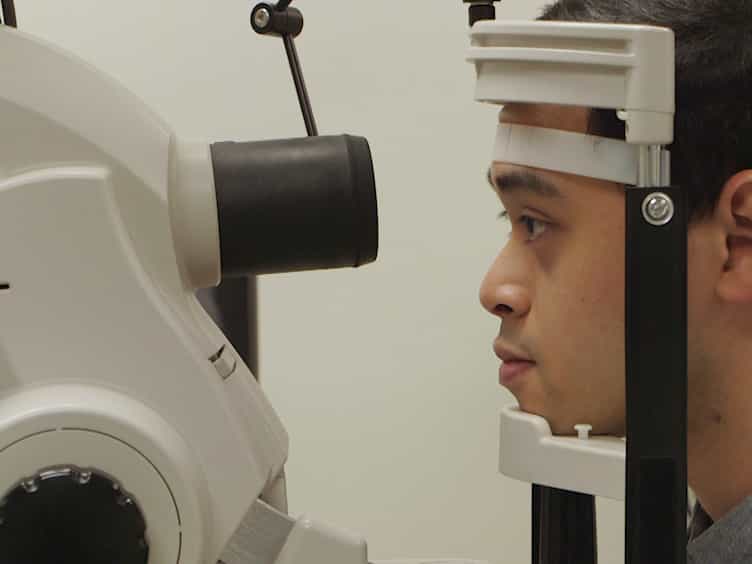

Using Retinal Imaging to Study Dementia
Published on: November 6, 2017
The AHA/ASA and DSM-V diagnostic criteria for vascular cognitive impairment identify cases with predominant vascular
Melmar C Folloso1,2,3, Steven G Villaraza1,2,3, Lo Yi-Wen4
1Memory, Ageing and Cognition Centre, National University Health System, Singapore.

Insights
The American Heart Association/American Stroke Association (AHA/ASA) and Diagnostic and Statistical Manual of Mental Disorders, Fifth Edition (DSM-V) criteria effectively identify vascular cognitive impairment (VCI) cases with minimal amyloid pathology, supporting their use in diagnosing predominantly vascular conditions.
Area of Science:
- Neurology
- Neuroimaging
- Cognitive Science
Background:
- Determining the etiology of vascular cognitive impairment (VCI) is challenging, particularly with mixed vascular and amyloid pathologies.
- Existing diagnostic criteria for VCI, including AHA/ASA and DSM-V, require validation using neuroimaging.
- Distinguishing between predominantly vascular and mixed pathologies is crucial for accurate VCI diagnosis and management.
Purpose of the Study:
- To evaluate the ability of AHA/ASA and DSM-V criteria to differentiate VCI cases with predominantly vascular pathology from those with mixed pathologies.
- To validate the diagnostic utility of these criteria using neuroimaging techniques, specifically [11C] PiB PET scans.
Main Methods:
- 186 subjects from a memory clinic underwent clinical, neuropsychological, MRI, and [11C] PiB PET assessments.
- VCI subtypes (VaMCI, VaD) were diagnosed using AHA/ASA and DSM-V criteria.
- Brain amyloid burden was quantified using [11C] PiB SUVR, with values ≥1.5 indicating amyloid positivity.
Main Results:
- Both AHA/ASA and DSM-V criteria showed excellent agreement for probable VaMCI and VaD, and good agreement for possible VaMCI.
- Amyloid positivity was significantly lower in probable VaMCI and VaD (predominantly vascular pathology) compared to other subtypes (p < 0.001).
- Both criteria effectively differentiated individuals with predominantly vascular pathology from those with significant amyloid burden.
Conclusions:
- The AHA/ASA and DSM-V criteria are valuable tools for identifying VCI cases with minimal or no amyloid co-pathology.
- These criteria support the diagnosis of patients with predominantly vascular contributions to cognitive impairment.
- Neuroimaging validation confirms the utility of these criteria in clinical practice for VCI subtyping.
Background:
There are major challenges in determining the etiology of vascular cognitive impairment (VCI) clinically, especially in the presence of mixed pathologies, such as vascular and amyloid. Most recently, two criteria (American Heart Association/American Stroke Association (AHA/ASA) and Diagnostic and Statistical Manual of Mental Disorders, Fifth Edition (DSM-V)) have been proposed for the clinical diagnosis of VCI but have not as yet been validated using neuroimaging.
Aims:
This study aims to determine whether the AHA/ASA and DSM-V criteria for VCI can distinguish between cases with predominantly vascular pathology and cases with mixed pathology.
Methods:
A total of 186 subjects were recruited from a cross-sectional memory clinic-based study at the National University Hospital, Singapore. All subjects underwent clinical and neuropsychological assessment, magnetic resonance imaging (MRI) and carbon 11-labeled Pittsburgh Compound B ([11C] PiB) positron emission tomography (PET) scans. Diagnosis of the etiological subtypes of VCI (probable vascular mild cognitive impairment (VaMCI), possible VaMCI, non-VaMCI, probable vascular dementia (VaD), possible VaD, non-VaD) were performed following AHA/ASA and DSM-V criteria. Brain amyloid burden was determined for each subject with standardized uptake value ratio (SUVR) values ⩾1.5 classified as amyloid positive.
Results:
Using κ statistics, both criteria had excellent agreement for probable VaMCI, probable VaD, and possible VaD (κ = 1.00), and good for possible VaMCI (κ = 0.71). Using the AHA/ASA criteria, the amyloid positivity of probable VaMCI (3.8%) and probable VaD (15%) was significantly lower compared to possible VaMCI (26.7%), non-VaMCI (33.3%), possible VaD (73.3%), and non-VaD (76.2%) (p < 0.001). Similarly, using the DSM-V criteria, the amyloid positivity of probable VaMCI (3.8%) and probable VaD (15%) was significantly lower compared to possible VaMCI (26.3%), non-VaMCI (32.1%), possible VaD (73.3%), and non-VaD (76.2%) (p < 0.001). In both criteria, there was good agreement in differentiating individuals with non-VaD and possible VaD, with significantly higher (p < 0.001) global [11C]-PiB SUVR, from individuals with probable VaMCI and probable VaD, who had predominant vascular pathology.
Conclusion:
The AHA/ASA and DSM-V criteria for VCI can identify VCI cases with little to no concomitant amyloid pathology, hence supporting the utility of AHA/ASA and DSM-V criteria in diagnosing patients with predominant vascular pathology.
Data Access Statement:
Data supporting this study are available from the Memory Aging and Cognition Center, National University of Singapore. Access to the data is subject to approval and a data sharing agreement due to University policy.
More Related Videos


Related Concept Videos
 01:30
Dementia
The progression of dementia is generally gradual....
 01:26
Alzheimer's Disease: Overview
The clinical diagnosis of AD hinges on the presence of memory and other cognitive impairments. Biomarkers, such as changes in Aβ...