Related Experiment Video
Updated: Jun 27, 2025
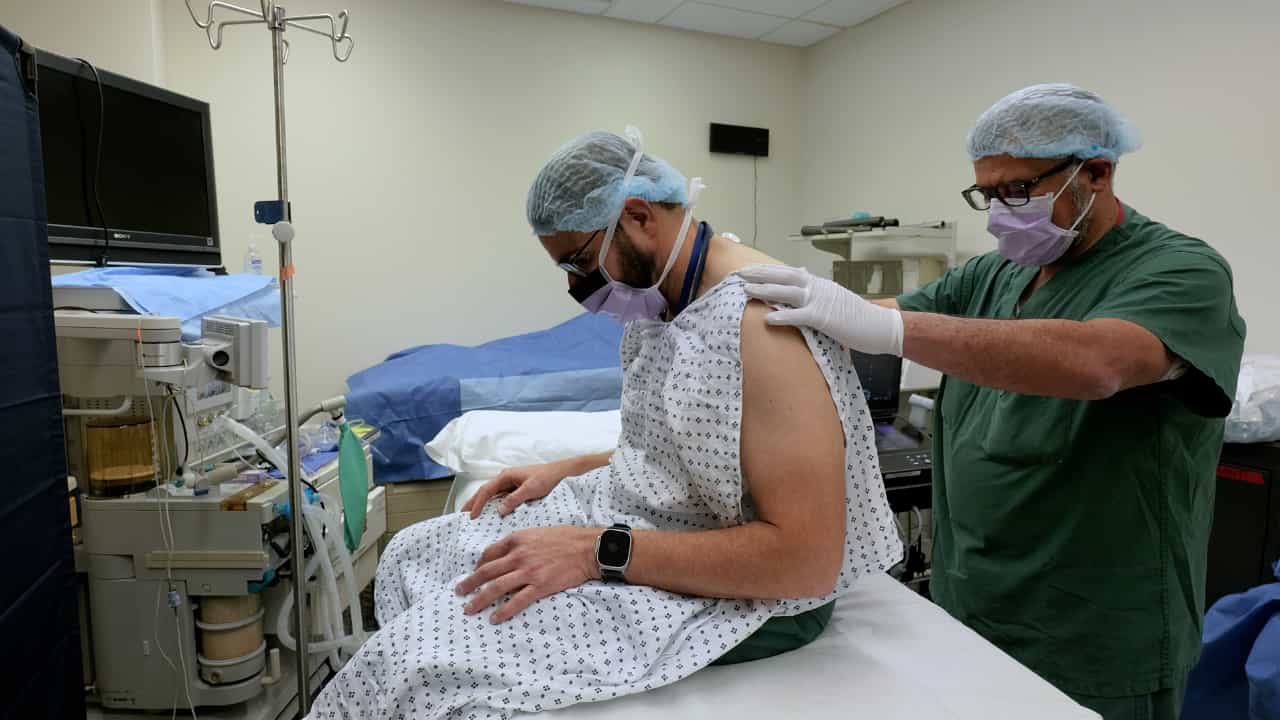

Author Spotlight: Enhancing Success of Ultrasound-Guided Neuraxial Anesthesia in Cases with Difficult Anatomy
Published on: January 31, 2025
Safety and Efficacy of Ultrasound-Guided Combined Segmental Thoracic Spinal Epidural Anesthesia in Abdominal
Alaa Ali M Elzohry1, Ahmed S Hegab2, Osama Yehia A Khalifa2
1Anasthesia, ICU and Pain Management, South Egypt Cancer Institute, Assiut University, El Fateh, Egypt.

Background:
Thoracic segmental spinal anesthesia (SA) may be a good alternative to general anesthesia (GA) for abdominal operations and laparoscopic procedures, especially in high-risk patients.
Objectives:
The aim of this study was to investigate the safety and efficacy of thoracic segmental SA vs GA during abdominal operations and laparoscopic procedures.
Methods:
This study was conducted at our university hospital and involved a total of 46 patients who underwent abdominal operations and laparoscopic procedures. The study period spanned from January 15, 2022, to October 15, 2022. Patients were divided into 2 groups: Group 1 (n = 23) received standard GA, and group 2 (n = 23) received thoracic segmental SA. A combination of 10 mg of hyperbaric bupivacaine 0.5% and 25 μg of fentanyl was injected through the spinal needle. The epidural catheter was then threaded through the Tuohy needle after withdrawal of the spinal needle to keep only 4 cm up in the epidural space. Demographic data, both intra and postoperative hemodynamic parameters, were monitored. Postoperatively, pain in both groups was treated with intravenous (IV) morphine by patient controlled analgesia (PCA), PCA settings were 1 mg morphine/mL, no background infusion, bolus dose 2 mL and lockout interval 15 min. Postoperative, both resting VAS and VAS during cough were measured for all patients at fixed intervals, and all patients were followed up for postoperative complications.
Results:
No significant variation was found in demographic data. Intra and postoperative mean arterial pressure (MAP) and heart rate (HR) measurements were higher in group 1 than in group 2 but without a statistically significant difference (P < 0.029). Early postoperative VAS values and discharge time from the postanesthesia care unit (PACU) were significantly reduced in group 2 than in group 1 (P < 0.001). The number of patients asked for analgesia and total opioid consumption were substantially reduced in group 2 than in group 1. Also, the time of the first analgesia request and patient satisfaction were substantially greater in group 2 than in group 1.
Conclusions:
Combined thoracic spinal/epidural block results in stable hemodynamics, longer postoperative analgesia with fewer side effects, and greater surgeon and patient satisfaction in patients undergoing abdominal operations and laparoscopic procedures.

Related Concept Videos
 01:29
Local Anesthetics: Clinical Application as Epidural Anesthesia
Since epidural anesthetics can be infused through an epidural catheter, all types of drugs, including short-acting ones, can be administered. Chloroprocaine and lidocaine are examples of short and long-duration anesthetics, respectively. Bupivacaine...
 01:11
Local Anesthetics: Clinical Application as Spinal Anesthesia