Related Experiment Video
Updated: Jun 26, 2025


Synthesis of a Borylated Ibuprofen Derivative Through Suzuki Cross-Coupling and Alkene Boracarboxylation Reactions
Published on: November 30, 2022
Salicylate Poisoning and Rebound Toxicity
Sindhu Harika Peketi1, Pratap Kumar Upadrista1, Bair Cadet2
1Internal Medicine, Nassau University Medical Center, East Meadow, USA.

Abstract:
Salicylate exposure and toxicity are associated with a myriad of symptoms and signs, and a comprehensive knowledge of diagnosing and treating salicylate poisoning is needed. Here, we present a case of a 29-year-old female with a past medical history of schizoaffective disorder and bipolar disorder with multiple suicide attempts brought to our hospital, Nassau University Medical Center, East Meadow, by the Emergency Medical Service (EMS) due to an intentional overdose of 300 pills of acetylsalicylic acid. She had mixed acid-base disturbance with respiratory alkalosis and metabolic acidosis. She was started on bicarbonate infusion in the emergency department to maintain a blood pH of 7.5 and to maintain a urine pH of more than 7.5. As her salicylate levels were 98.2 at admission with altered mental status, she was started on slow, low-efficiency hemodialysis. A few hours later, she developed a rebound increase in salicylate levels to 129, associated with a change in mental status and the patient was more confused. She was started on regular hemodialysis with improvement in mental status and elimination of salicylate steadily. Given the extensive nature of toxic effects, a patient with severe salicylate toxicity can deteriorate rapidly and can be challenging to manage. As there is no specific antidote for aspirin, the goals of therapy depend primarily on limiting the absorption of salicylate, enhancing elimination, and providing supportive care. Monitoring the acid-base status and serum salicylate levels closely and monitoring for rebound increase in salicylate levels is of paramount importance. Aggressive hydration to maintain euvolemia, alkalinization, aggressive replenishment of potassium and magnesium, activated charcoal to decrease absorption, and hemodialysis remain the cornerstones of treatment.
Related Concept Videos
 01:26
Toxic Reactions: Overview
Toxicity falls into two primary categories: local and systemic.
Local toxicity appears at the exposure site, such as protein denaturation caused by caustic substances.
In contrast, systemic toxicity requires the toxic agent's absorption and distribution,...
 01:14
Prevention of Further Absorption of Poison
 01:31
Acid Suppressive Drugs for Peptic Ulcer Disease: Antacids
However, this neutralization reaction between...
 01:26
Anticholinesterase Agents: Poisoning and Treatment
Irreversible agents form a strong bond with the cholinesterase enzyme, making it inactive. The breakdown of the phosphorylated enzyme is...
 01:17
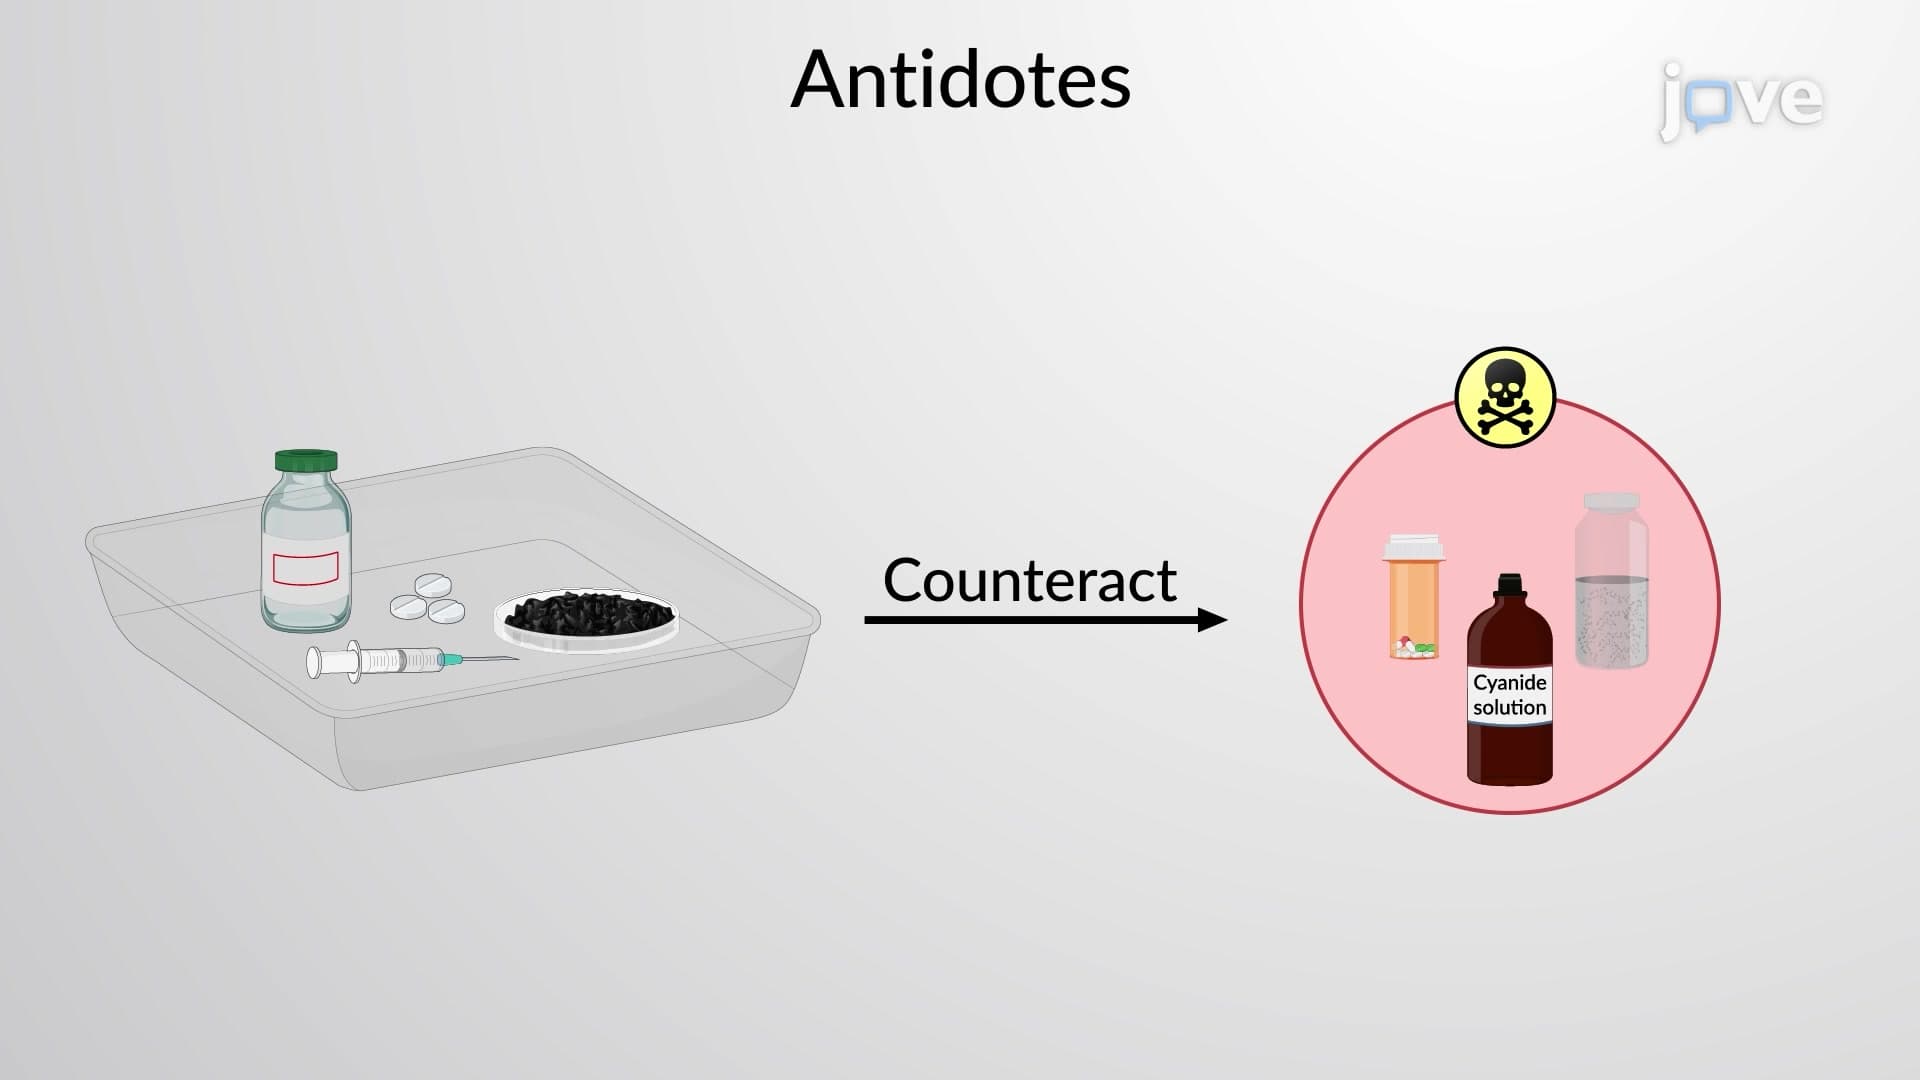
Antidotes
Specific antidotes operate by inhibiting the enzymes that control biochemical pathways, reducing the production of harmful metabolites.
An example of an antidote is atropine, which counteracts the detrimental effects of cholinesterase inhibitors. It achieves this by deactivating muscarinic receptors,...
 01:26
Enhanced Elimination of Poison
Antidotes serve a crucial role in counteracting the effects of poison by inhibiting enzymes responsible for producing harmful drug metabolites. In some cases, these toxic metabolites can be neutralized by endogenous cosubstrates, which are maintained at specific concentrations to prevent interaction with cellular macromolecules and subsequent cell death.
Renal excretion is the...