Related Experiment Video
Updated: Jun 25, 2025
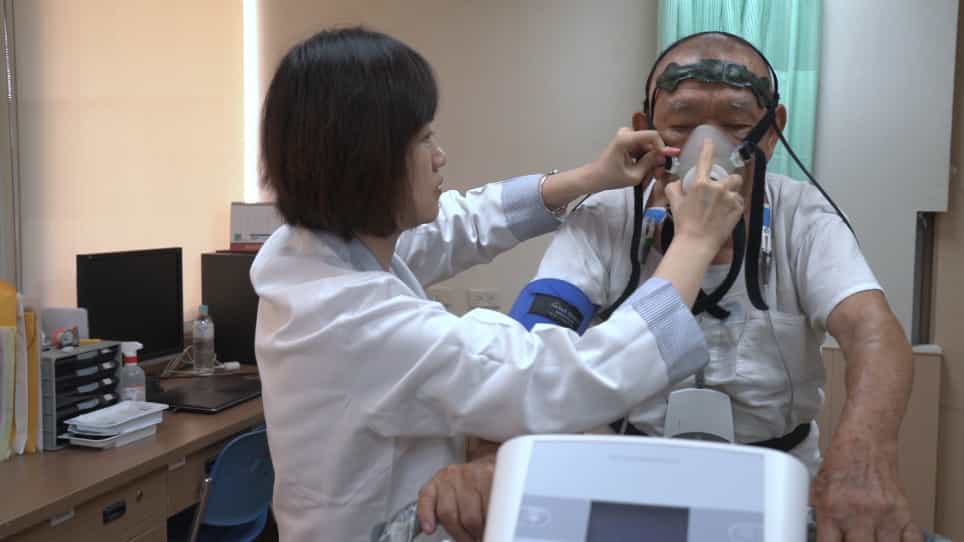

Integration of Brain Tissue Saturation Monitoring in Cardiopulmonary Exercise Testing in Patients with Heart Failure
Published on: October 1, 2019
Non-arterial line cardiac output calculation misclassifies exercise pulmonary hypertension and increases risk of data
Luiz Campedelli1, S Mehdi Nouraie1,2, Michael G Risbano3,2
1Division of Pulmonary, Allergy, and Critical Care Medicine, Department of Medicine, University of Pittsburgh School of Medicine and UPMC, Pittsburgh, PA, USA.

Insights
Using peripheral oxygen saturation (SpO2) instead of arterial oxygen saturation (SaO2) during invasive exercise testing can misclassify exercise pulmonary hypertension (ePH). This method also leads to significant data loss, especially in Black patients and those with scleroderma or Raynaud's.
Area of Science:
- Cardiopulmonary physiology
- Clinical exercise testing
- Medical diagnostics
Background:
- The direct Fick principle is standard for cardiac output (CO) calculation, crucial for detecting CO-dependent conditions like exercise pulmonary hypertension (ePH).
- Fick CO calculations can utilize arterial (Hba, SaO2) or non-arterial (Hbmv, SpO2) values, with the latter used when arterial lines are absent.
- Discrepancies in oxygen saturation and hemoglobin between arterial and non-arterial measurements may impact Fick CO calculations and ePH classification during exercise.
Purpose of the Study:
- To compare SpO2 and SaO2, Hba and Hbmv, and COarterial vs. COnon-arterial in invasive cardiopulmonary exercise testing (iCPET).
- To assess the risk of misclassifying pre- and post-capillary ePH using non-arterial measurements.
- To evaluate data loss associated with inaccurate SpO2 during iCPET.
Main Methods:
- Retrospective analysis of 296 iCPET studies.
- Comparison of SpO2 (pulse oximetry) and SaO2 (radial arterial).
- Assessment of Hba, Hbmv, COarterial, and COnon-arterial, and analysis of data loss and ePH misclassification.
Main Results:
- Low correlation was observed between SpO2 and SaO2, and between COarterial and COnon-arterial.
- Significantly higher data loss occurred with SpO2 (18%) compared to SaO2 (0.88%).
- ePH was misclassified in 17.1% of pre-capillary and 8.7% of post-capillary cases using COnon-arterial. SpO2 data loss was higher in Black patients (31.6%) and those with scleroderma/Raynaud's (33.3%).
Conclusions:
- Reliance on SpO2 during iCPET leads to misclassification of ePH.
- Unmeasurable SpO2 in certain patient groups (Black, scleroderma, Raynaud's) limits diagnostic accuracy.
- Invasive exercise testing without an arterial line may compromise diagnostic and prognostic value due to unreliable SpO2 measurements.
Background:
The direct Fick principle is the standard for calculating cardiac output (CO) to detect CO-dependent conditions like exercise pulmonary hypertension (ePH). Fick COarterial incorporates arterial haemoglobin (Hba) and oxygen saturation (S aO ) with oxygen consumption from exercise testing, while Fick COnon-arterial substitutes mixed venous haemoglobin (Hbmv) and peripheral oxygen saturation (S pO ) in the absence of an arterial line. The decision to employ an arterial catheter for exercise testing varies, and discrepancies in oxygen saturation and haemoglobin between arterial and non-arterial methods may lead to differences in Fick CO, potentially affecting ePH classification.
Methods:
We performed a retrospective analysis of 296 consecutive invasive cardiopulmonary exercise testing (iCPET) studies comparing oxygen saturation from pulse oximetry (S pO ) and radial arterial (S aO ), Hba and Hbmv, and CO calculated with arterial (COarterial) and non-arterial (COnon-arterial) values. We assessed the risk of misclassification of pre- and post-capillary ePH and data loss due to inaccurate S pO .
Results:
When considering all stages from rest to peak exercise, Hba and Hbmv demonstrated high correlation, while S pO and S aO as well as COarterial and COnon-arterial demonstrated low correlation. Data loss was significantly higher across all stages of exercise for S pO (n=346/1926 (18%)) compared to S aO (n=17/1923 (0.88%)). We found that pre- and post-capillary ePH were misclassified as COnon-arterial data (n=7/41 (17.1%) and n=2/23 (8.7%), respectively). Patients with scleroderma and/or Raynaud's (n=11/33 (33.3%)) and black patients (n=6/19 (31.6%)) had more S pO data loss.
Conclusion:
Reliance upon S pO during invasive exercise testing results in the misclassification of pre- and post-capillary ePH, and unmeasurable S pO for black, scleroderma and Raynaud's patients can preclude accurate exercise calculations, thus limiting the diagnostic and prognostic value of invasive exercise testing without an arterial line.
Related Concept Videos
 01:26
Imbalances in Cardiac Output
CHF can occur due to the failure of either side of the heart. Left-side failure leads to pulmonary congestion—the right side continues to send...
 01:17
Exercise and Cardiac Output
Sustained exercise increases the muscles' oxygen demand, which can be...
 01:17
Measurement of Blood Pressure