Related Experiment Video
Updated: Jul 16, 2026
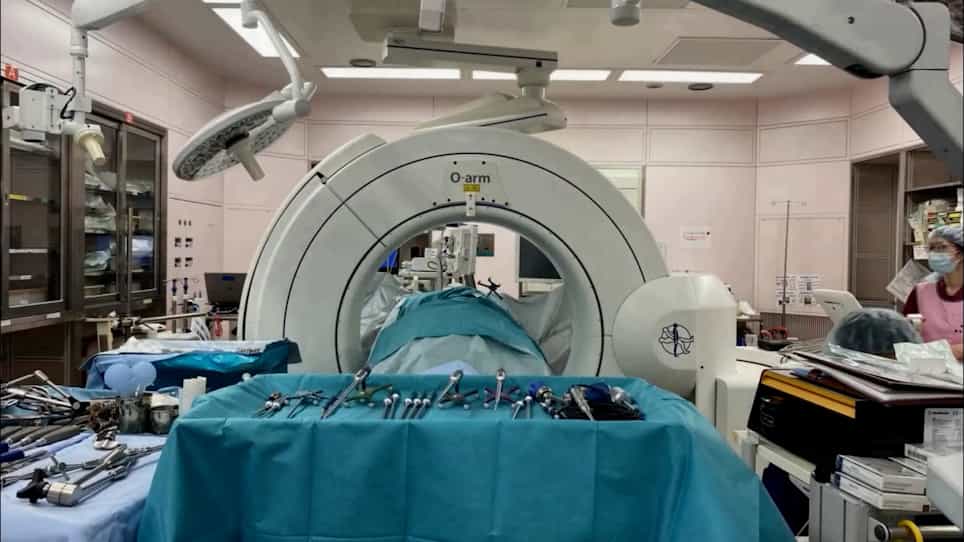

C-arm-Free Simultaneous OLIF51 and Percutaneous Pedicle Screw Fixation in a Single Lateral Position
Published on: September 16, 2022
Anterior vertebral tethering for adolescent idiopathic scoliosis: our initial ten year clinical experience
John T Braun1, Sofia C Federico2, David M Lawlor2
1Massachusetts General Hospital, Harvard Medical School, 55 Fruit St., Yawkey 3E, Boston, MA, 02114, USA. jbraun3@mgh.harvard.edu.

Background:
Anterior vertebral tethering (AVT) is a minimally invasive alternative to fusion surgery for adolescent idiopathic scoliosis (AIS) that offers the potential for definitive scoliosis treatment with the possibility of preservation of the growth, motion, function and overall health of the spine. This study represents our first ten years using AVT to treat AIS.
Methods:
In this retrospective review we analyzed our first 74 AIS patients treated with AVT 2010-2020. Multiple Lenke curve types 33-70° were treated with skeletal maturity spanning Risser -1 to 5.
Results:
Of 74 consecutive AIS patients treated with AVT, 52 patients (47 female, 5 male) had sufficient 2-year follow-up for inclusion. Forty-six of these 52 patients (88%) with 65 curves (35T, 30TL/L) were satisfactorily treated with AVT demonstrating curve correction from 48.6° pre-op (range 33°-70°) at age 15.1 years (range 9.2-18.8) and skeletal maturity of Risser 2.8 (range -1 to 5) to 23.2° post-op (range 0°-54°) and 24.0° final (range 0°-49°) at 3.3 years follow-up (range 2-10 years). Curve corrections from pre-op to post-op and pre-op to final were both significant (p < 0.001). The 0.8° change from post-op to final was not significant but did represent good control of scoliosis correction over time. Thoracic kyphosis and lumbar lordosis were maintained in a normal range throughout while axial rotation demonstrated a slight trend toward improvement. Skeletal maturity of Risser 4 or greater was achieved in all but one patient. Four of the 52 patients (8%) required additional procedures for tether rupture (3 replacements) or overcorrection (1 removal) to achieve satisfactory treatment status after AVT. An additional 6 of the 52 patients (12%), however, were not satisfactorily treated with AVT, requiring fusion for overcorrection (2) or inadequate correction (4).
Conclusions:
In this study, AIS was satisfactorily treated with AVT in the majority of patients over a broad range of curve magnitudes, curve types, and skeletal maturity. Though late revision surgery for overcorrection, inadequate correction, or tether rupture was not uncommon, the complication of overcorrection was eliminated after our first ten patients by a refinement of indications.
Level Of Evidence:
IV.
More Related Videos

Related Concept Videos
 01:54
The Spinal Cord
 01:16
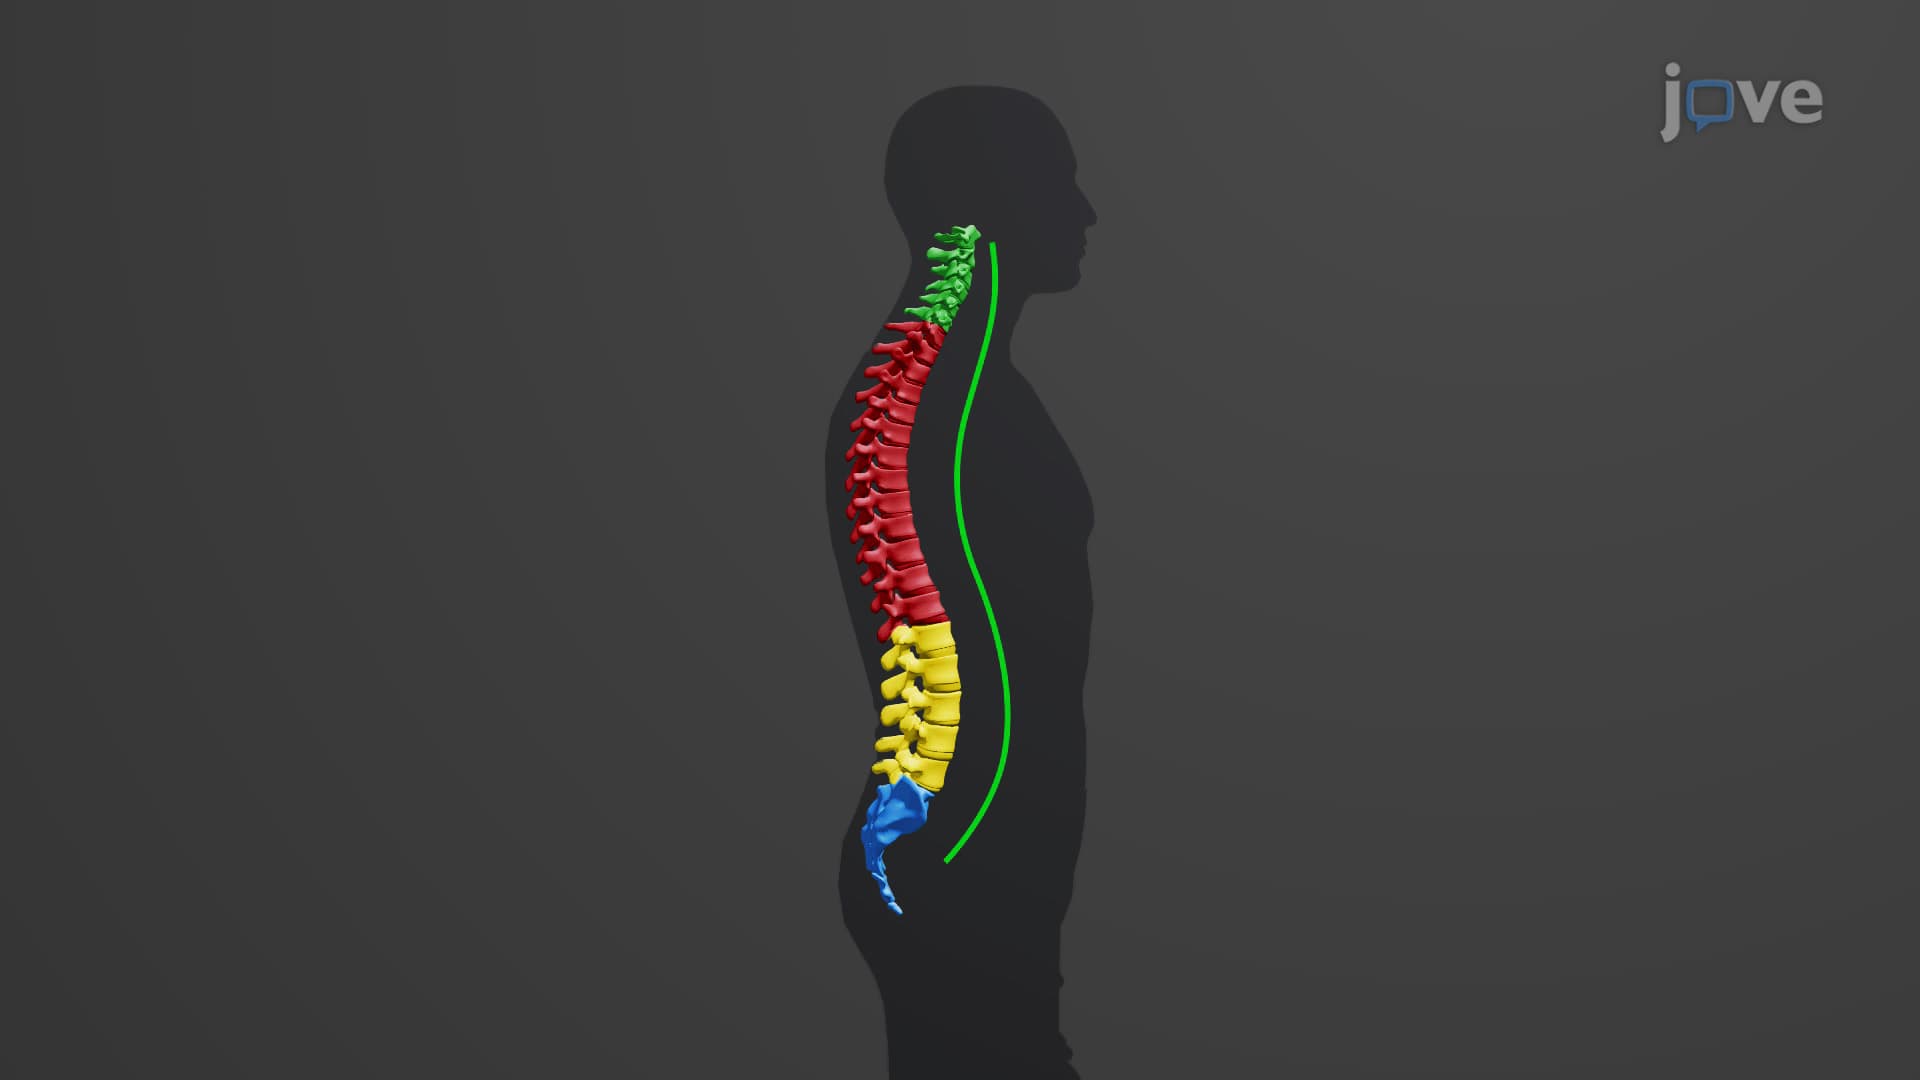
Vertebral Column: Regions and Curvature
Regions of the Vertebral Column
In an adult, the spine is subdivided into five regions: the cervical, the thoracic, the lumbar, the sacral, and the coccygeal region. The spine initially develops as a series of 33 vertebrae; after 20 years of age, the nine bones in the sacral region, five sacral, and four coccygeal bones fuse to form the...
 01:09
Changes in the Appendicular Skeleton with Age
Initially, the limb buds consist of a core of mesenchyme covered by a layer of ectoderm. The ectoderm at the end of the limb bud thickens to form a narrow crest called the apical ectodermal ridge. This ridge stimulates the underlying...
 01:16
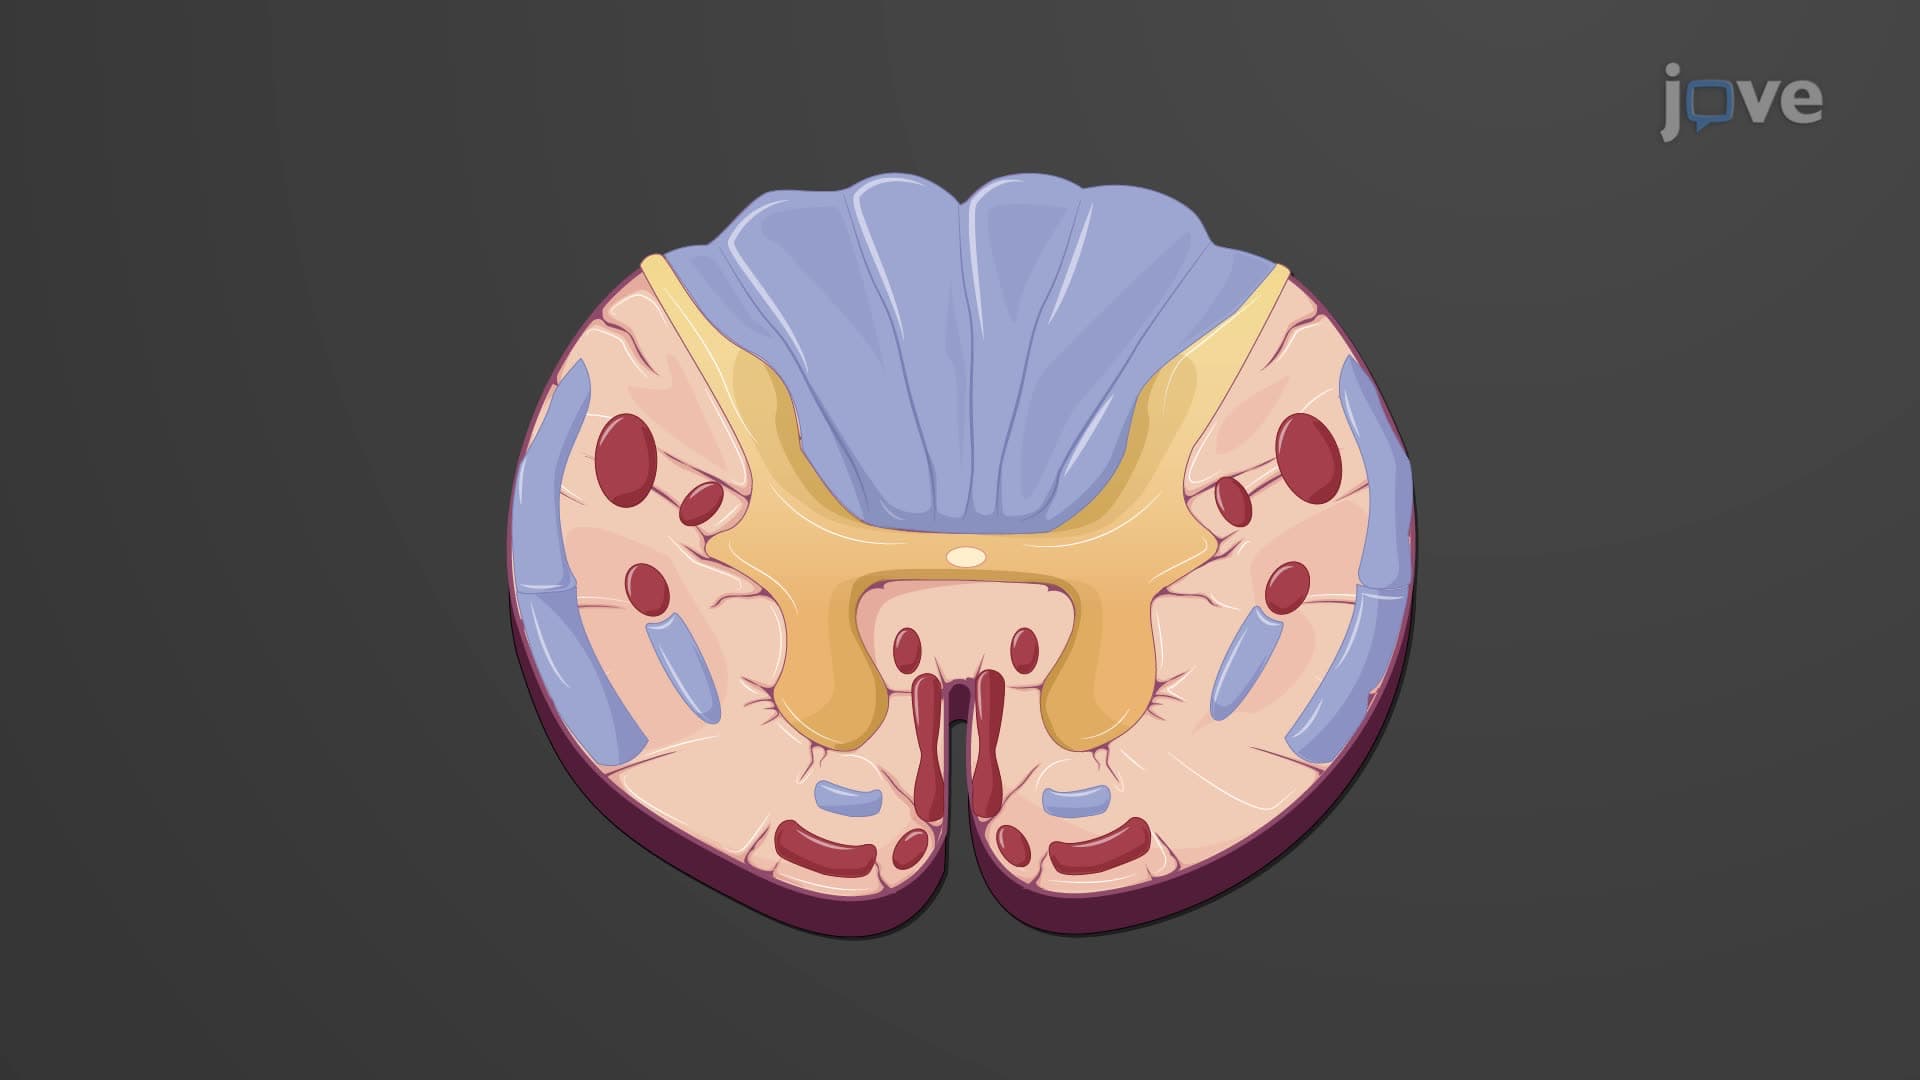
Spinal Cord: Cross-sectional Anatomy
Gray Matter and its Components
Central to the gray matter is...
 01:25
Secondary Spinal Cord Injury llI: Pathophysiology