Related Experiment Video
Updated: Jun 25, 2025


Cox-Maze IV Procedure Concomitant with Valvular Surgery In Situs Inversus Dextrocardia: A Single-Center Experience in China
Published on: February 11, 2022
Uncommon presentations of type A quadricuspid aortic valve in the Septuagenarian
Perry Choi1,2, Michael Paulsen1, Yihan Lin1
1Department of Cardiothoracic Surgery, Stanford University Medical Center, 300 Pasteur Drive Stanford, Stanford, CA, 94305, USA.

Background:
Quadricuspid aortic valve (QAV) is a rare congenital anomaly characterized by the presence of four cusps instead of the usual three. It is estimated to occur in less than 0.05% of the population, with Type A (four equal-sized leaflets) accounting for roughly 30% of QAV subtypes. Based on limited clinical series, the usual presentation is progressive aortic valve regurgitation (AR) with symptoms occurring in the fourth to sixth decade of life. Severe aortic valve stenosis (AS) and acute AR are very uncommon.
Case Presentation:
We describe two cases of Type A QAV in patients who remained asymptomatic until their seventies with very uncommon presentations: one with severe AS and one with acute, severe AR and flail leaflet. In Case A, a 72-year-old patient with history of moderate AS presents to clinic with progressive exertional dyspnea. During work-up for transcatheter vs. surgical replacement pre-operative computed tomography angiogram (CTA) reveals a quadricuspid aortic valve with severe AS, and the patient undergoes surgical aortic valve replacement. Pre-discharge transthoracic echocardiography (TTE) shows good prosthetic valve function with no gradient or regurgitation. In Case B, a 76-year-old patient is intubated upon arrival to the hospital for acute desaturation, found to have wide open AR on catheterization, and transferred for emergent intervention. Intraoperative TEE reveals QAV with flail leaflet and severe AR. Repair is considered but deferred ultimately due to emergent nature. Post-operative TTE demonstrates good prosthetic valve function with no regurgitation and normal biventricular function.
Conclusions:
QAV can present as progressive severe AS and acute AR, with symptoms first occurring in the seventh decade of life. The optimal treatment for QAV remains uncertain. Although aortic valve repair or transcatheter option may be feasible in some patients, aortic valve replacement remains a tenable option.
More Related Videos
 12:12
Echocardiographic Approaches and Protocols for Comprehensive Phenotypic Characterization of Valvular Heart Disease in Mice
Published on: February 14, 2017
 04:48
Noninvasive Determination of Vortex Formation Time Using Transesophageal Echocardiography During Cardiac Surgery
Published on: November 28, 2018
Related Concept Videos
 01:25
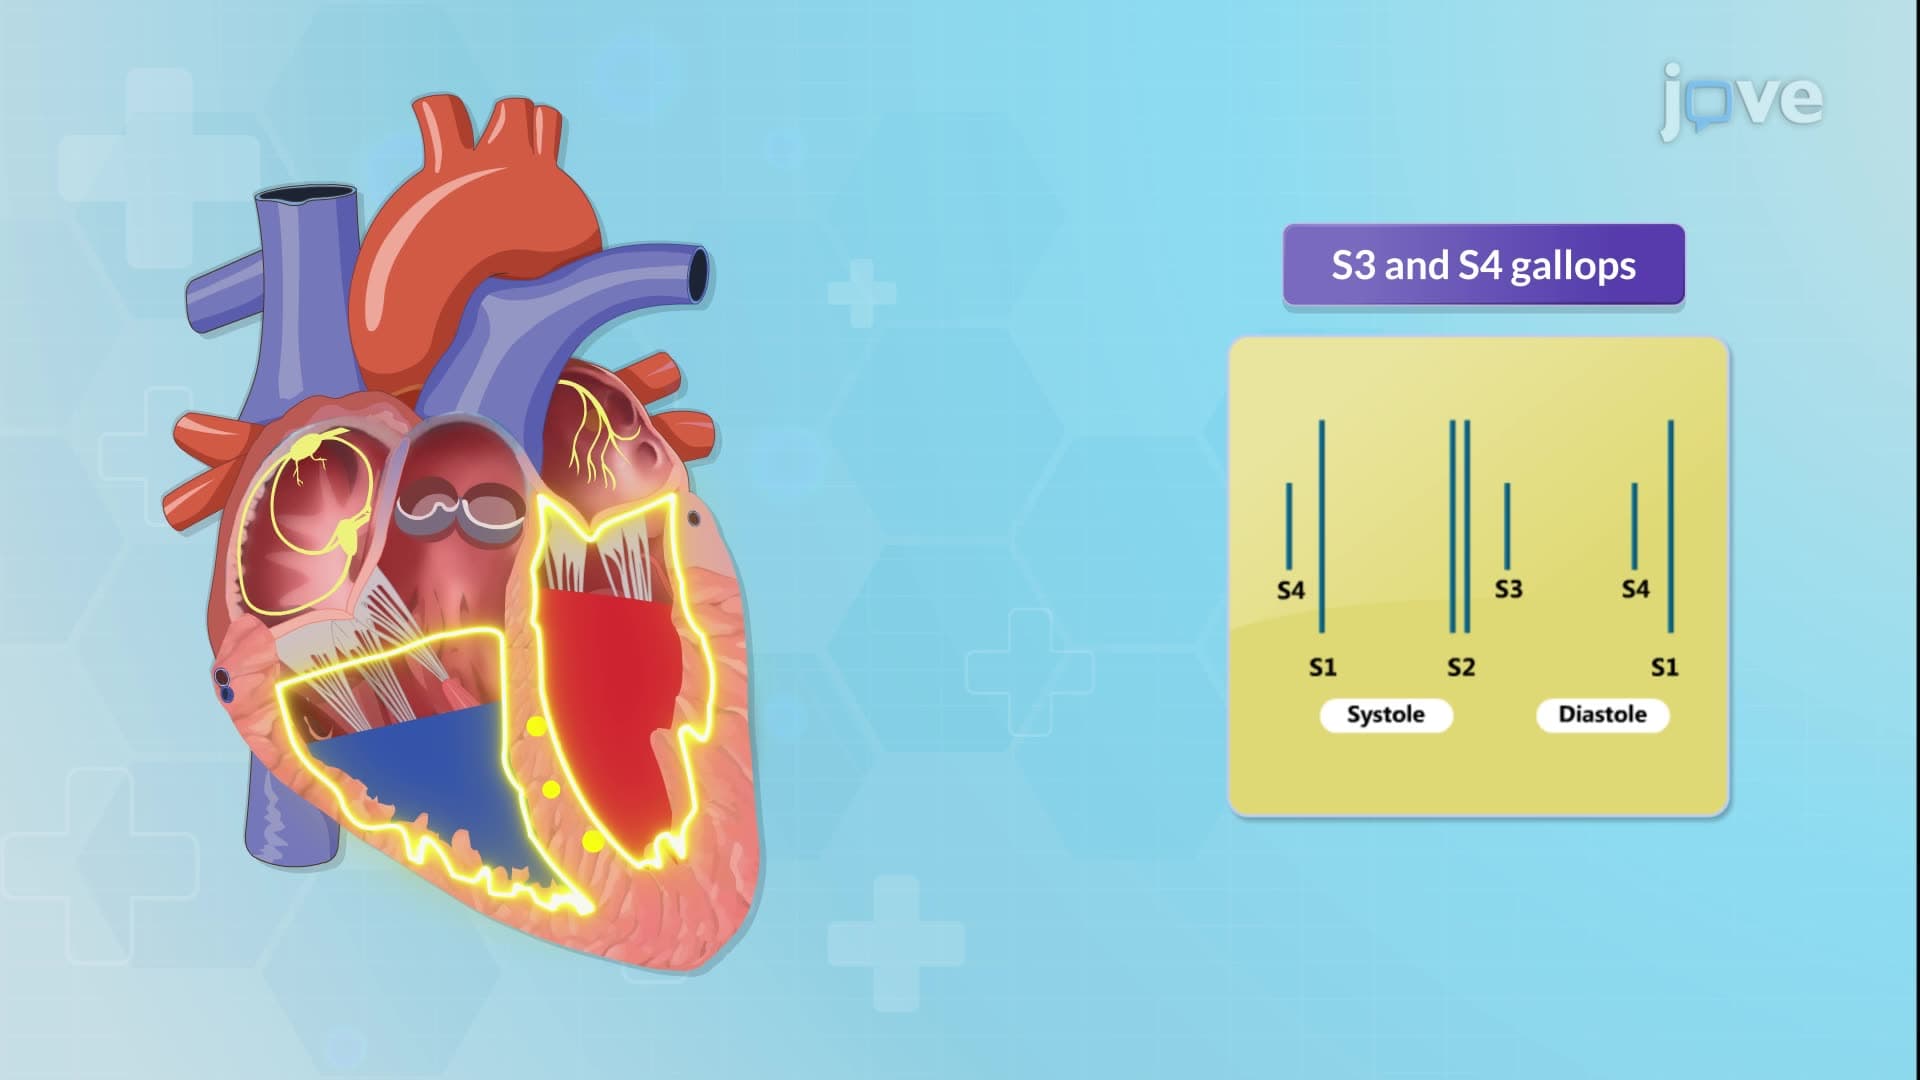
Cardiovascular System Abnormal Findings II: Auscultation
Abnormal Heart Sounds
Gallops:
 01:16
Heart Valves
The AV valves prevent the backflow of blood from the ventricles to the atria during ventricular contraction. These valves function with the assistance of the chordae tendineae and papillary muscles. When the ventricles are relaxed, the chordae tendineae are slack, allowing blood to flow from the atria into the...
 01:15
Thoracic Aorta
 01:25
Abdominal Aorta
The celiac trunk, a singular artery, divides into the left gastric artery, which...
 01:29
Cardiovascular System Abnormal Findings I: Inspection and Palpation
Abnormal findings observed during an inspection
 01:25
Assessment of apical radial pulse
The A-R pulse assessment involves simultaneous evaluation of the apical and radial pulses. When the apical and radial pulse rates vary, this assessment helps identify a pulse deficit.
Pre-Procedural Preparation