Related Experiment Video
Updated: Jun 23, 2025


Extra Cellular Matrix-Based and Extra Cellular Matrix-Free Generation of Murine Testicular Organoids
Published on: October 7, 2020
Pathogenesis and pathobiology of testicular germ cell tumours: a view from a developmental biological perspective
Alexander Fichtner1, Daniel Nettersheim2,3, Felix Bremmer1
1Institute of Pathology, University Medical Center, Göttingen, Germany.

Abstract:
Testicular germ cell tumours (GCT) are divided into three different subtypes (types I-III) regarding to their developmental origin, histological differences and molecular features. Type I GCT develop from disturbed primordial germ cells and most commonly occur in children and young adolescents, which is why they are referred to as prepubertal GCT. Type II GCT develop from a non-invasive germ cell neoplasia in situ (GCNIS) and show an isochromosome 12p (i12p) or gain of 12p material as a common and characteristic molecular alteration. Type III GCT originate from distorted postpubertal germ cells (e.g. spermatogonia) in adult patients and have changes on chromosome 9 with amplification of the DMRT1 gene. Type I GCT encompass prepubertal-type teratomas and yolk-sac tumours (YST). Type II GCT include seminoma, embryonal carcinoma, choriocarcinoma, postpubertal-type teratoma and postpubertal-type YST. Types I and II GCT both show similar morphology, but are separated from each other by the detection of a GCNIS and an i12p in type II GCT. For type II GCT it is especially important to detect non-seminomatous elements, as these tumours have a worse biological behaviour and need a different treatment to seminomas. In contrast to types I and II GCT, type III tumours are equivalent to spermatocytic tumours and usually occur in elderly men, with few exceptions in young adults. The development of types I and II GCT seems to depend not upon driver mutations, but rather on changes in the epigenetic landscape. Furthermore, different pluripotency associated factors (e.g. OCT3/4, SOX2, SOX17) play a crucial role in GCT development and can be used as immunohistochemical markers allowing to distinguish the different subtypes from each other in morphologically challenging tissue specimens. Especially in metastatic sites, a morphological and immunohistochemical diagnostic algorithm is important to detect small subpopulations of each non-seminomatous GCT subtype, which are associated with a poorer prognosis and need a different treatment. Furthermore, primary extragonadal GCT of the retroperitoneum or mediastinum develop from misguided germ cells during embryonic development, and might be challenging to detect in small tissue biopsies due to their rarity at corresponding sites. This review article summarises the pathobiological and developmental aspects of the three different types of testicular GCT that can be helpful in the histopathological examination of tumour specimens by pathologists.

Related Concept Videos
 01:15
Development of the Sexual Organs in the Embryo and Fetus
Near the gonadal ridges, two duct systems are present: the mesonephric ducts (Wolffian ducts) and paramesonephric ducts (Müllerian ducts). These ducts form the basis for the...
 01:27
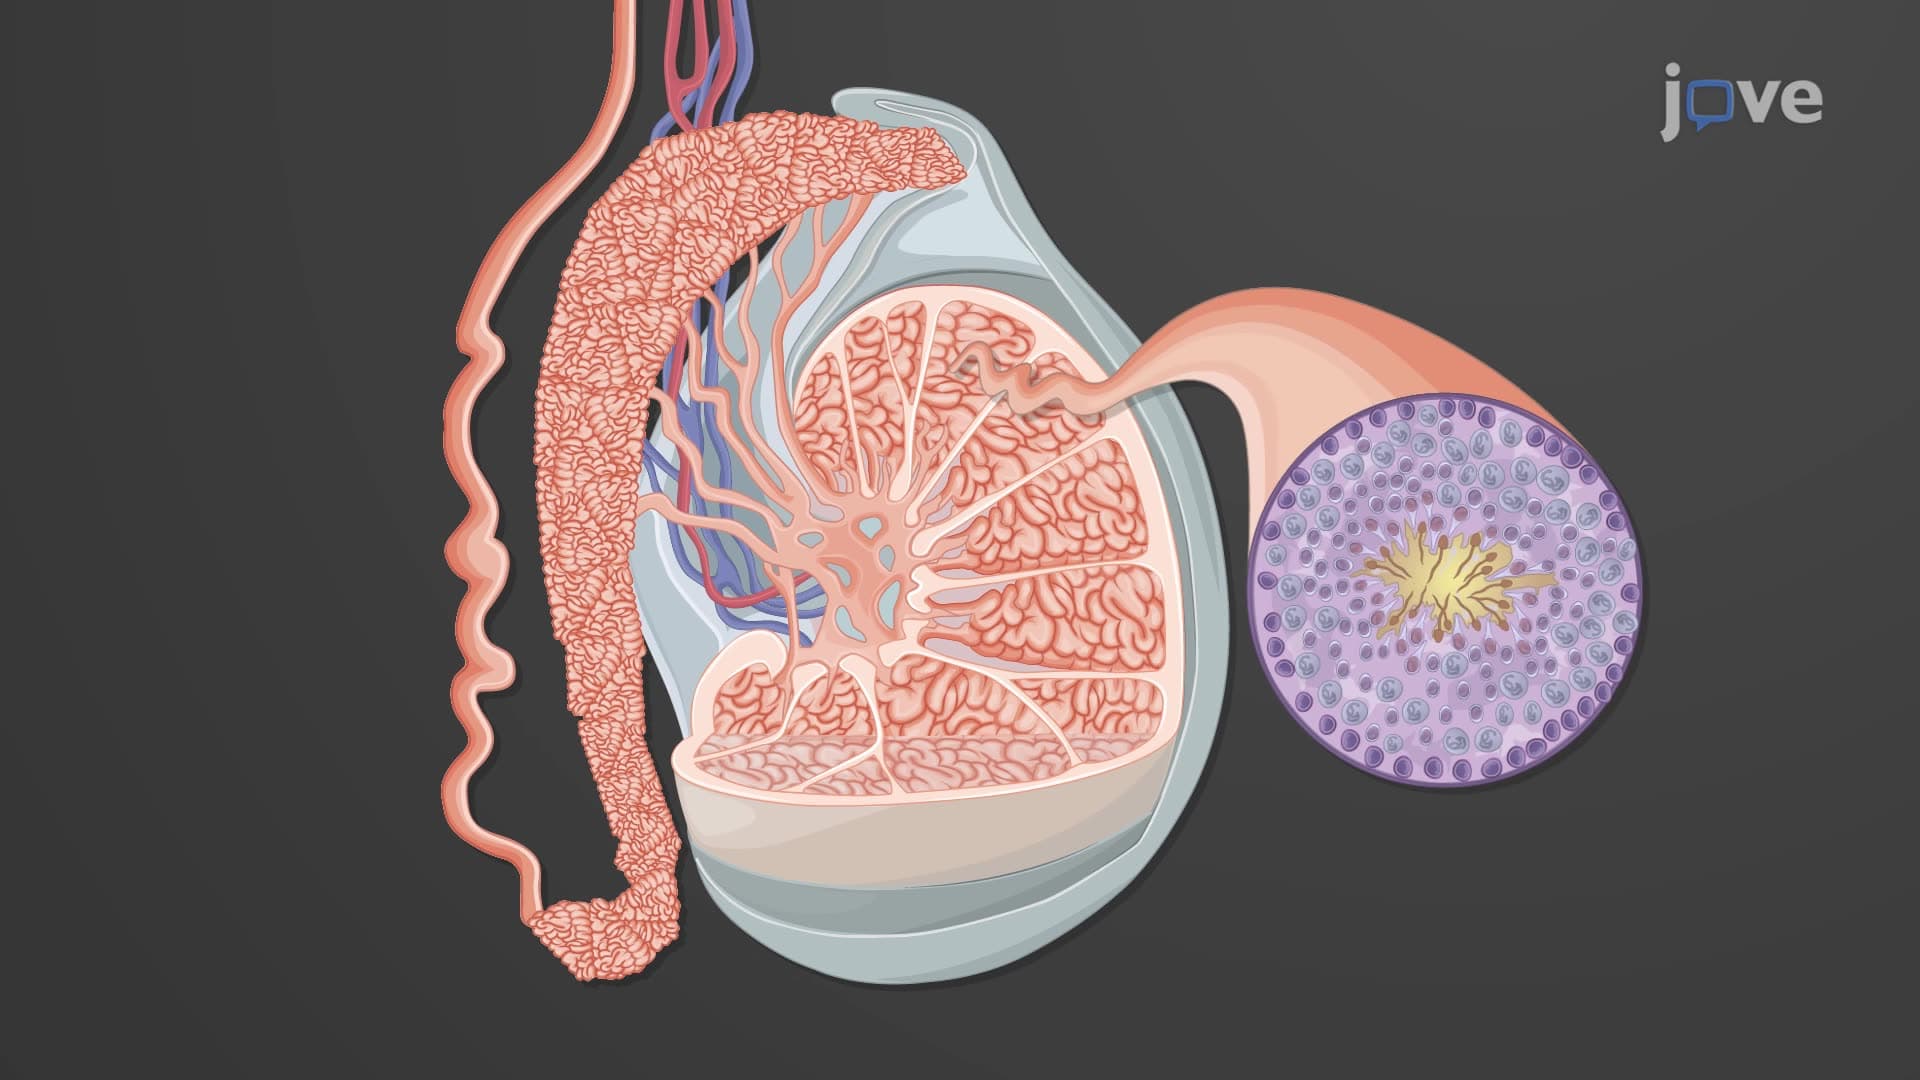
Testes: Histology
The spermatogenic cells, responsible for producing sperm, are...
 01:20
Disorders of the Male Reproductive System
Prostate disorders are another major concern. These conditions can impair urinary flow due to the prostate's location around the urethra....
 01:19
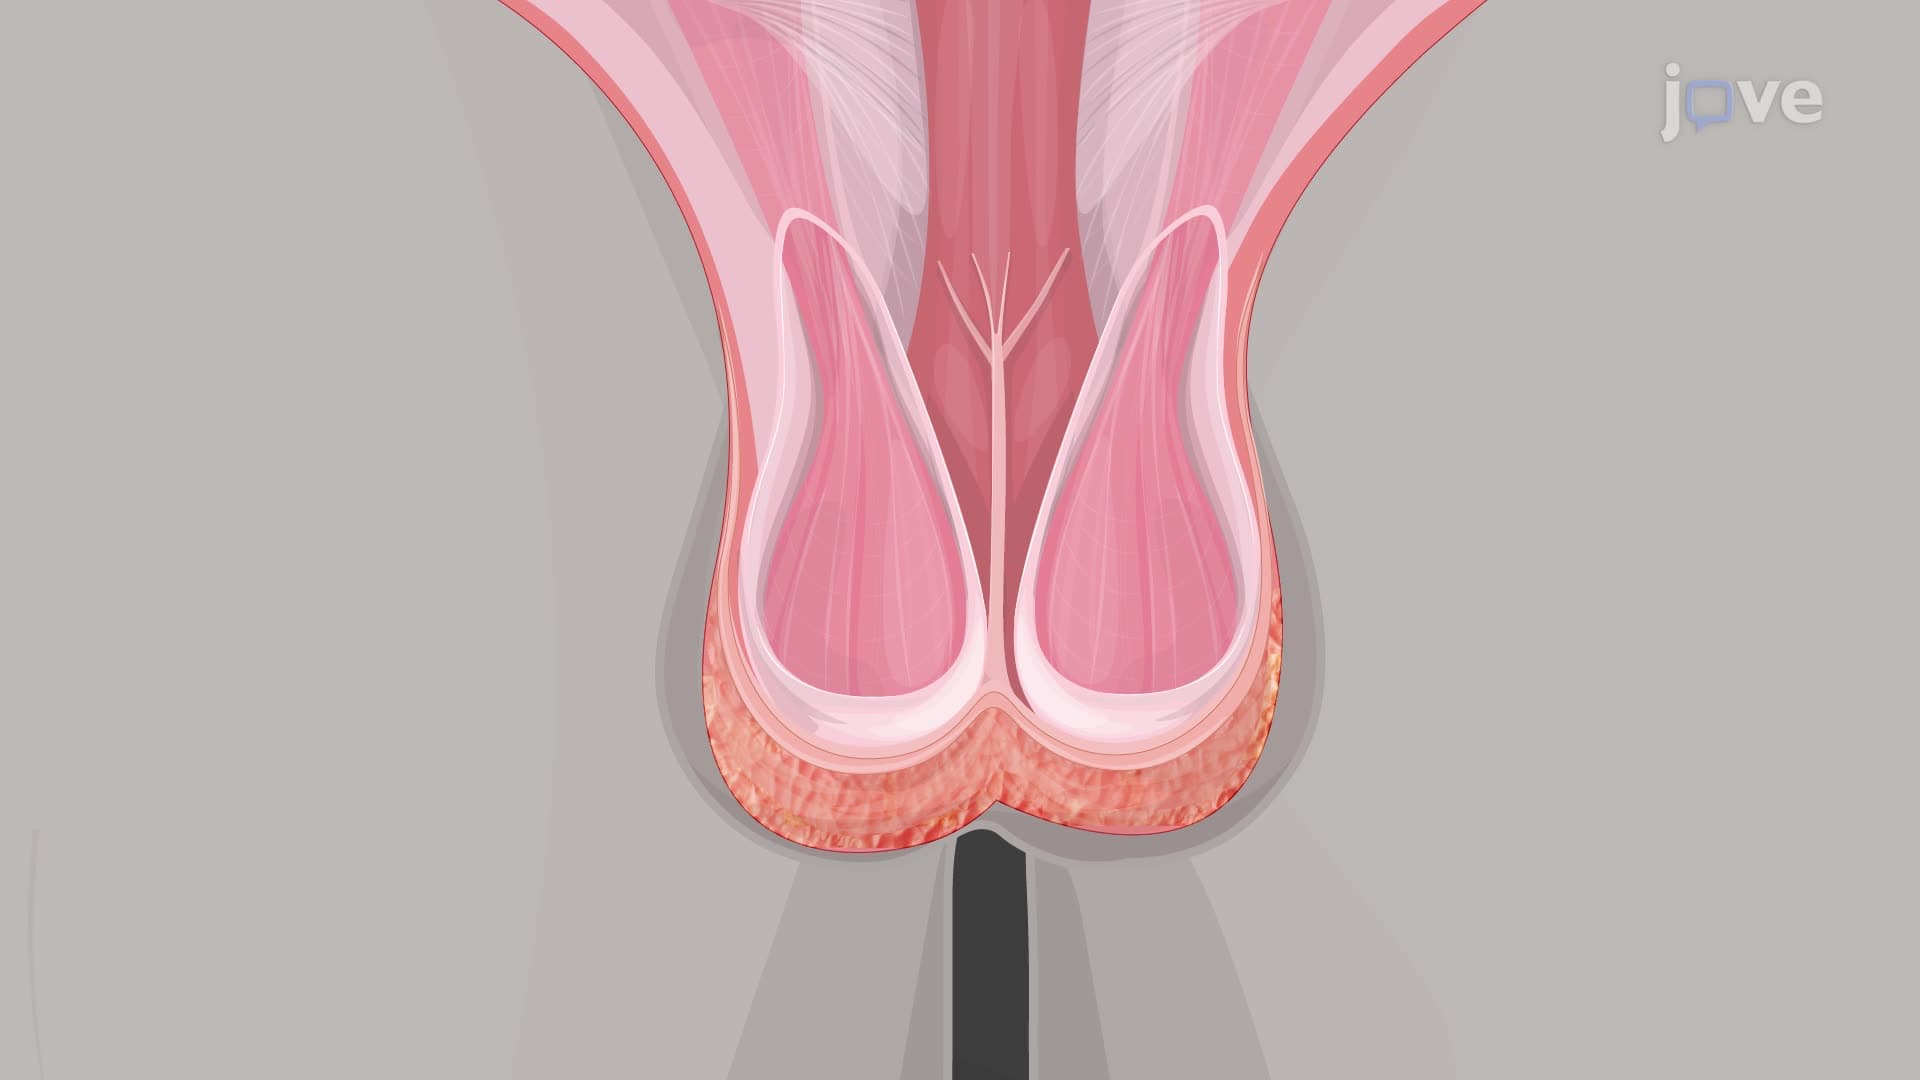
Testes: Gross Anatomy
Each testis is surrounded by the tunica albuginea, a dense connective tissue layer that provides structural support and protection. This layer is covered by an outer serous membrane called the tunica vaginalis, which helps reduce friction...
 01:41
Spermatogenesis