Related Experiment Video
Updated: Jun 22, 2025
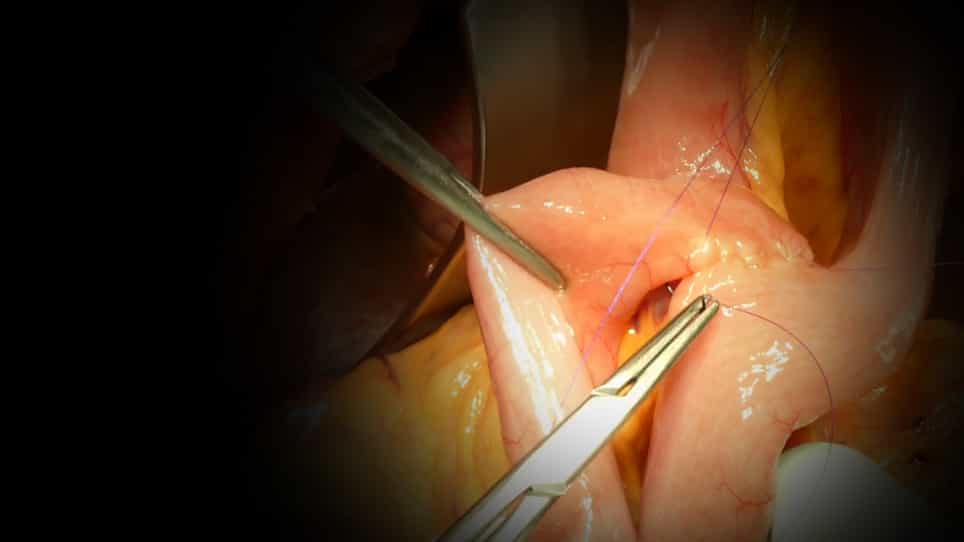

Modified Single-Loop Reconstruction for Pancreaticoduodenectomy
Published on: September 28, 2019
Who Do We Fail to Rescue After Pancreatoduodenectomy? Outcomes Among >4000 Procedures Expose Windows of Opportunity
Benedict Kinny-Köster1, Darius Halm1, Duc Tran1
1Department of General, Visceral and Transplantation Surgery, Heidelberg University Hospital.

Objective:
Our investigation on in-hospital mortality after 4474 pancreatoduodenectomies aimed to identify time-dependent risks as well as windows of opportunity to rescue patients from complications.
Background:
Pancreatoduodenectomy is generally considered a safe procedure with a 1% to 10% perioperative mortality based on complexity and surgical volume. Yet, patients are susceptible to life-threatening complications particularly with extended resections. Recognition of distinct vulnerabilities over time while patients recover is required to permit focused monitoring, sophisticated resource allocation, and the greatest surgical safety.
Methods:
Patients who deceased in-hospital after pancreatoduodenectomy between 2003 and 2021 were retrieved from the institutional pancreatectomy registry and analyzed in detail with respect to their postoperative course.
Results:
Among 4474 pancreatoduodenectomies, 156 patients deceased in-hospital (3.5%). When assessing root causes of mortality, we observed 3 different clusters of complications, which were postpancreatectomy-specific (51.9%), visceral vasculature-associated (25.6%), or cardiopulmonary in origin (17.9%). The median times of root cause onset in the 3 categories were postoperative day (POD) 9, POD 4.5 ( P =0.008), and POD 3 ( P <0.001), respectively. Medians of in-hospital mortality were POD 31, POD 18 ( P =0.009), and POD 8 ( P <0.001). Intervals between root cause onset and mortality varied with medians of 23 days, 11 days ( P =0.017), and 1 day ( P <0.001). The 3 categories were similarly distributed between different types of surgical complexity.
Conclusions:
Postpancreatectomy-specific complications prompt almost half of the in-hospital mortalities after pancreatoduodenectomy, with rather long intervals for interventions to prevent failure to rescue. In contrast, visceral vasculature-related events and cardiopulmonary complications dominate early in-hospital mortalities with short intervals until mortality, demanding rigorous management of such events or preoperative conditioning. These data externally validate a previous high-volume initiative and highlight distinct windows of opportunity to optimize perioperative safety.
Related Concept Videos
 01:29
Chronic Pancreatitis II: Collaborative Care
Assessment:
 01:26
Endoscopic Procedures V: ERCP
Patient...
 01:30
Acute Pancreatitis II: Clinical Manifestations and Management