Related Experiment Video
Updated: Jun 21, 2025

Author Spotlight: Integrating Alveolar-Capillary Reserve Measurements in Exercise Adaptation and Therapeutic Strategies
Published on: February 2, 2024
Differences of ventilatory muscle recruitment and work of breathing in COPD and interstitial lung disease during
Jeferson George Ferreira1,2, Vinícius Carlos Iamonti1, Mayra Caleffi Pereira1
1Pulmonary Division, Heart Institute (InCor), Hospital das Clínicas HCFMUSP, Faculdade de Medicina, Universidade de São Paulo, São Paulo, Brazil.

Introduction:
COPD and interstitial lung disease (ILD) are significant chronic respiratory disorders, impacting quality of life. Respiratory muscle roles and differences remain not entirely clear. The objective of the present study was to evaluate the degree of recruitment of the respiratory muscles and the work of breathing in COPD and ILD during exercise.
Methods:
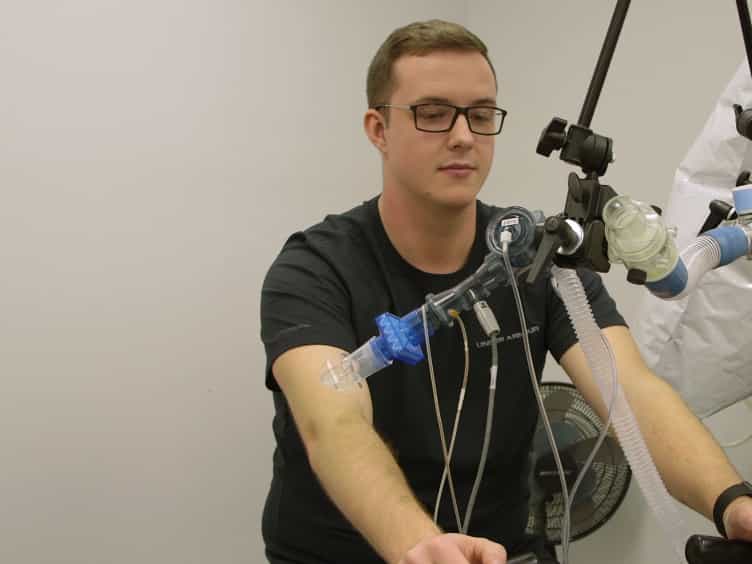
We compared the sensory-mechanical relationships in COPD, ILD and healthy controls (n=20 each). They performed pulmonary function, noninvasive and invasive respiratory muscle strength, surface electromyography and work-of-breathing assessments.
Results:
COPD and ILD did not show lower static muscle strength compared to controls, but did show poor performance in the exercise test with increased transdiaphragmatic pressure (P di). In ILD, there was a higher increase in oesophageal pressure and a lower gastric pressure (P ga) on inspiration; in COPD, there was a significant increase in P ga on inspiration. In ILD, there is greater recruitment of accessory inspiratory muscles, whereas in COPD, there is marked use of both inspiratory and expiratory muscles. The neuromechanical inefficiency (increased neural respiratory drive without the corresponding tidal volume) was found in both diseases. In COPD, there is a considerable increase in elastic work to overcome intrinsic positive end-expiratory pressure (PEEPi) and expiratory work of breathing, whereas in ILD, non-PEEPi elastic work of breathing is the highest part of the total work of breathing.
Conclusions:
Early and increased activity of the respiratory muscles and work-of-breathing components significantly contribute to dyspnoea, exercise intolerance and neuromechanical inefficiency of ventilation in COPD and ILD. The mechanisms of P di generation were different between diseases.
More Related Videos
 07:09
Assessment of Pulmonary Capillary Blood Volume, Membrane Diffusing Capacity, and Intrapulmonary Arteriovenous Anastomoses During Exercise
Published on: February 20, 2017
 00:07
Home-Based Prescribed Pulmonary Exercise in Patients with Stable Chronic Obstructive Pulmonary Disease
Published on: August 24, 2019
Related Concept Videos
 01:27
Chronic Obstructive Pulmonary Disease-IV: Assessement and Diagnostic Studies
Medical History
 01:20
Chronic Obstructive Pulmonary Disease-I: Introduction
 01:22
Chronic Obstructive Pulmonary Disease
Smoking is a primary risk factor for COPD, with over 80% of patients having a history of it. Patients typically experience progressive dyspnea or labored breathing, frequent coughing, and recurrent pulmonary infections. Many eventually succumb to respiratory failure, characterized by...
 01:20
Chronic Obstructive Pulmonary Disease-II: Pathophysiology
Chronic Inflammation
 01:19
Factors Affecting Pulmonary Ventilation
Alveolar Surface Tension
The alveolar fluid lines the luminal surface of the alveoli and exerts a force called surface tension. This force is caused by the polar water molecules in the liquid being more strongly attracted to each...
 01:20
COPD: Pathogenesis and Clinical Features
The primary cause for the onset of COPD is cigarette smoking and exposure to air pollution. These hazardous factors initiate a chain reaction within the lungs, resulting in chronic inflammation, damage to the airways, and a...