Related Experiment Video
Updated: Jun 20, 2025

05:34
5/6 Nephrectomy Using Sharp Bipolectomy Via Midline Laparotomy in Rats
Published on: April 4, 2025
544
Results of the EPISODE trial plead for reasonable practice-based serum phosphate lowering in patients on dialysis
Takayuki Hamano1, Masafumi Fukagawa2
1Department of Nephrology, Nagoya City University Graduate School of Medical Sciences, Nagoya, Japan; Department of Nephrology, The University of Osaka Graduate School of Medicine, Osaka, Japan.
Kidney International
|July 20, 2024

Abstract
No abstract available in PubMed .

Related Concept Videos
 01:27
Dialysis
288
Renal failure occurs when the kidneys lose their ability to filter waste products from the blood effectively. It can be classified into two types: acute renal failure (ARF) and chronic renal failure (CRF).
Acute kidney injury develops suddenly and can be caused by pre-renal causes (e.g., hypovolemia, shock), intrinsic renal causes (e.g., acute tubular necrosis), or post-renal causes (e.g., urinary obstruction). In contrast, chronic renal failure progresses gradually over time and is often...
Acute kidney injury develops suddenly and can be caused by pre-renal causes (e.g., hypovolemia, shock), intrinsic renal causes (e.g., acute tubular necrosis), or post-renal causes (e.g., urinary obstruction). In contrast, chronic renal failure progresses gradually over time and is often...
288
 01:11
Renal Failure: Dose Adjustments
79
In patients with renal impairment, drugs undergo significant changes in their pharmacokinetics, which require dosage adjustments to ensure safe and effective therapy.
Reduced renal clearance and elimination rate are common outcomes of renal impairment. These alterations lead to a prolonged elimination half-life and an altered apparent volume of distribution for drugs. As a result, dosage adjustments are typically necessary to maintain optimal drug levels in the body.
However, dosage adjustments...
79
 01:28
Antihypertensive Drugs: Potassium-Sparing Diuretics
504
Liddle syndrome is a genetically inherited form of hypertension characterized by the overactivity of epithelial sodium channels in the nephron, the functional unit of the kidney. This heightened activity leads to increased sodium reabsorption and excessive excretion of potassium. To counteract this, potassium-sparing diuretics such as amiloride are used. They function by blocking these sodium channels, thereby reducing the influx of sodium into the epithelial cells and minimizing the loss of...
504
 01:22
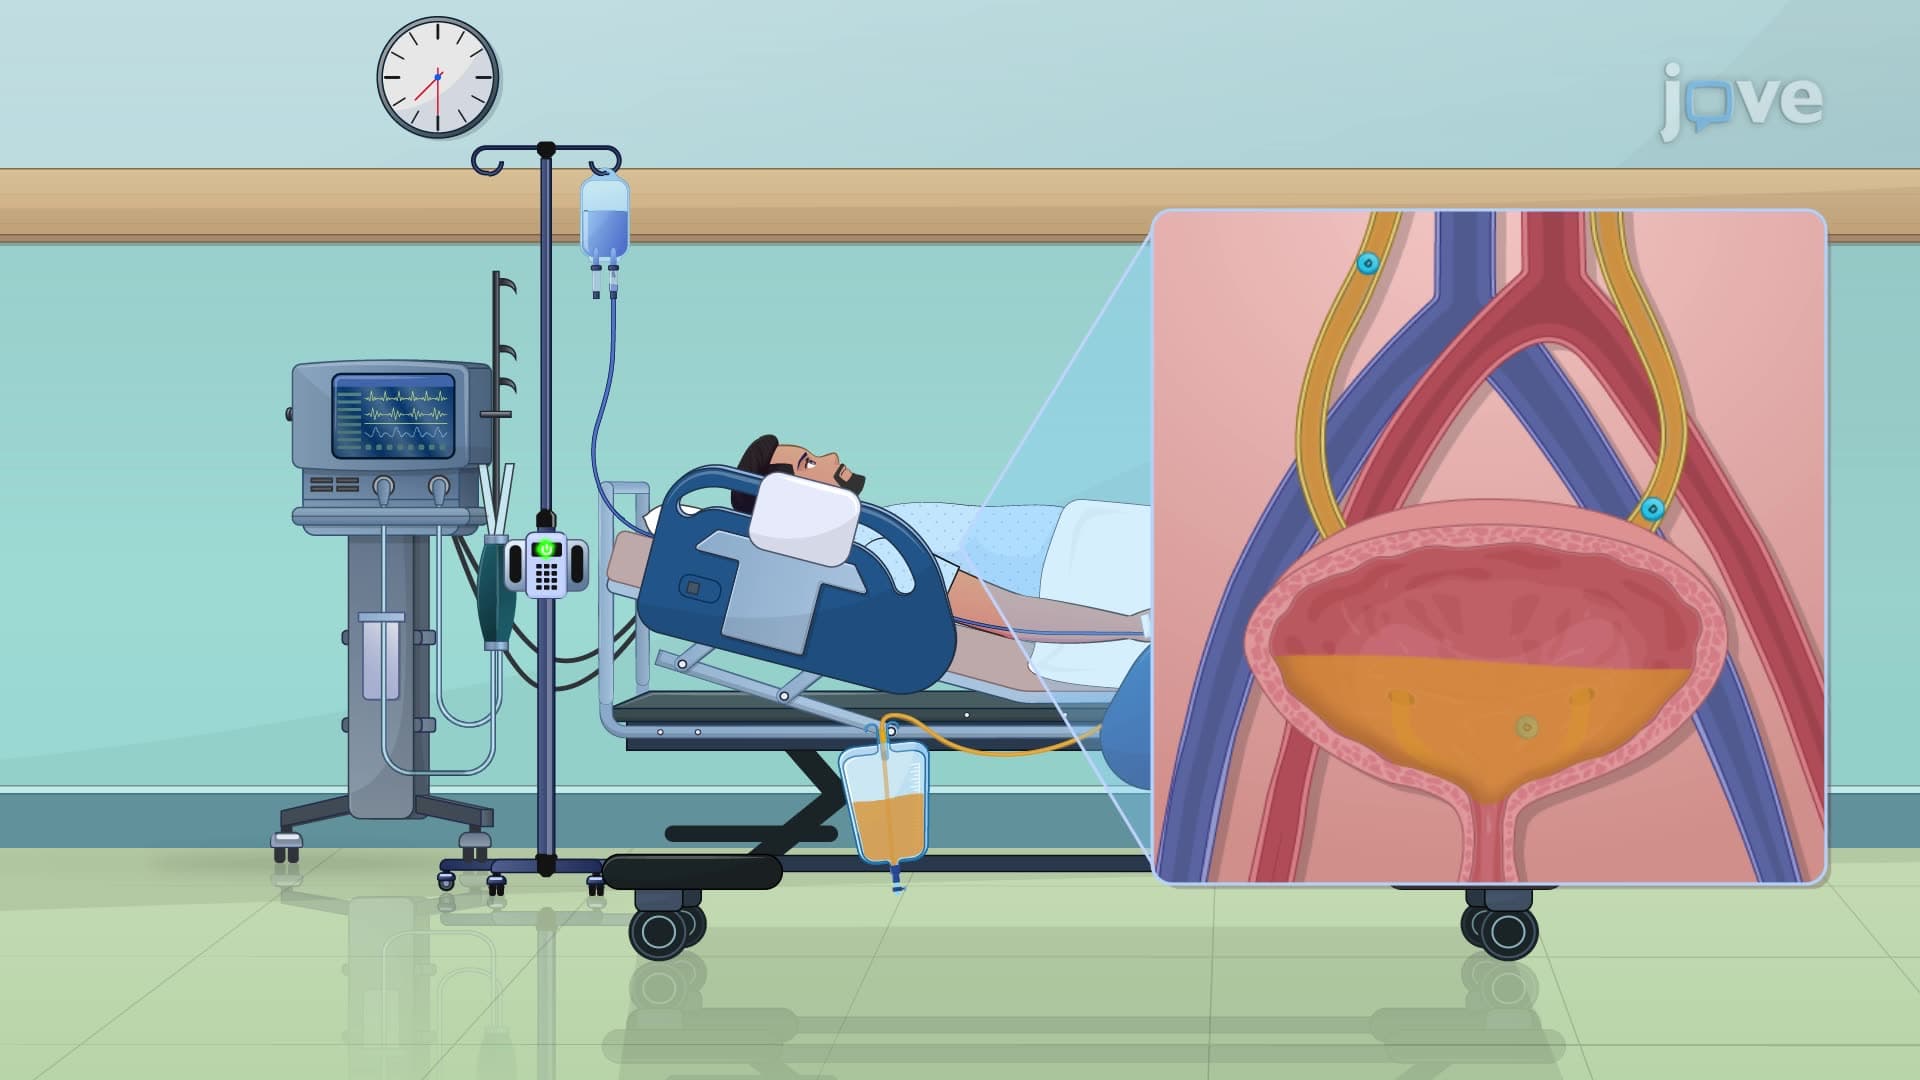
Renal Drug Excretion: Effect of Urine pH, Flow Rate, and Drug pKa
159
The pH of urine, the drug's pKa, and the urine flow rate are vital parameters for drug reabsorption and excretion. Urinary pH varies between 4.6 and 8.0 and is influenced by diet, drug intake, and the patient's pathophysiology. It affects a drug's ionization state and reabsorption. For instance, carbohydrate-rich food produces alkaline urine promoting drug excretion, while proteins and certain medications like ascorbic acid lead to acidic urine enhancing reabsorption.
The pKa of a...
The pKa of a...
159
 01:28
Renal Drug Excretion: Tubular Secretion
167
Active tubular secretion is a robust, energy-demanding process that utilizes carrier systems to transport drugs into renal tubules. The active renal secretion systems include the organic anion transporter (OAT) for weak acids and the organic cation transporter (OCT) for weak bases. Structurally similar drugs can compete for the same transporter, potentially leading to drug accumulation and toxicity. However, this principle can be exploited therapeutically. One example is probenecid (Probalan),...
167
 01:29
Renal Regulation of Acid-Base Balance
384
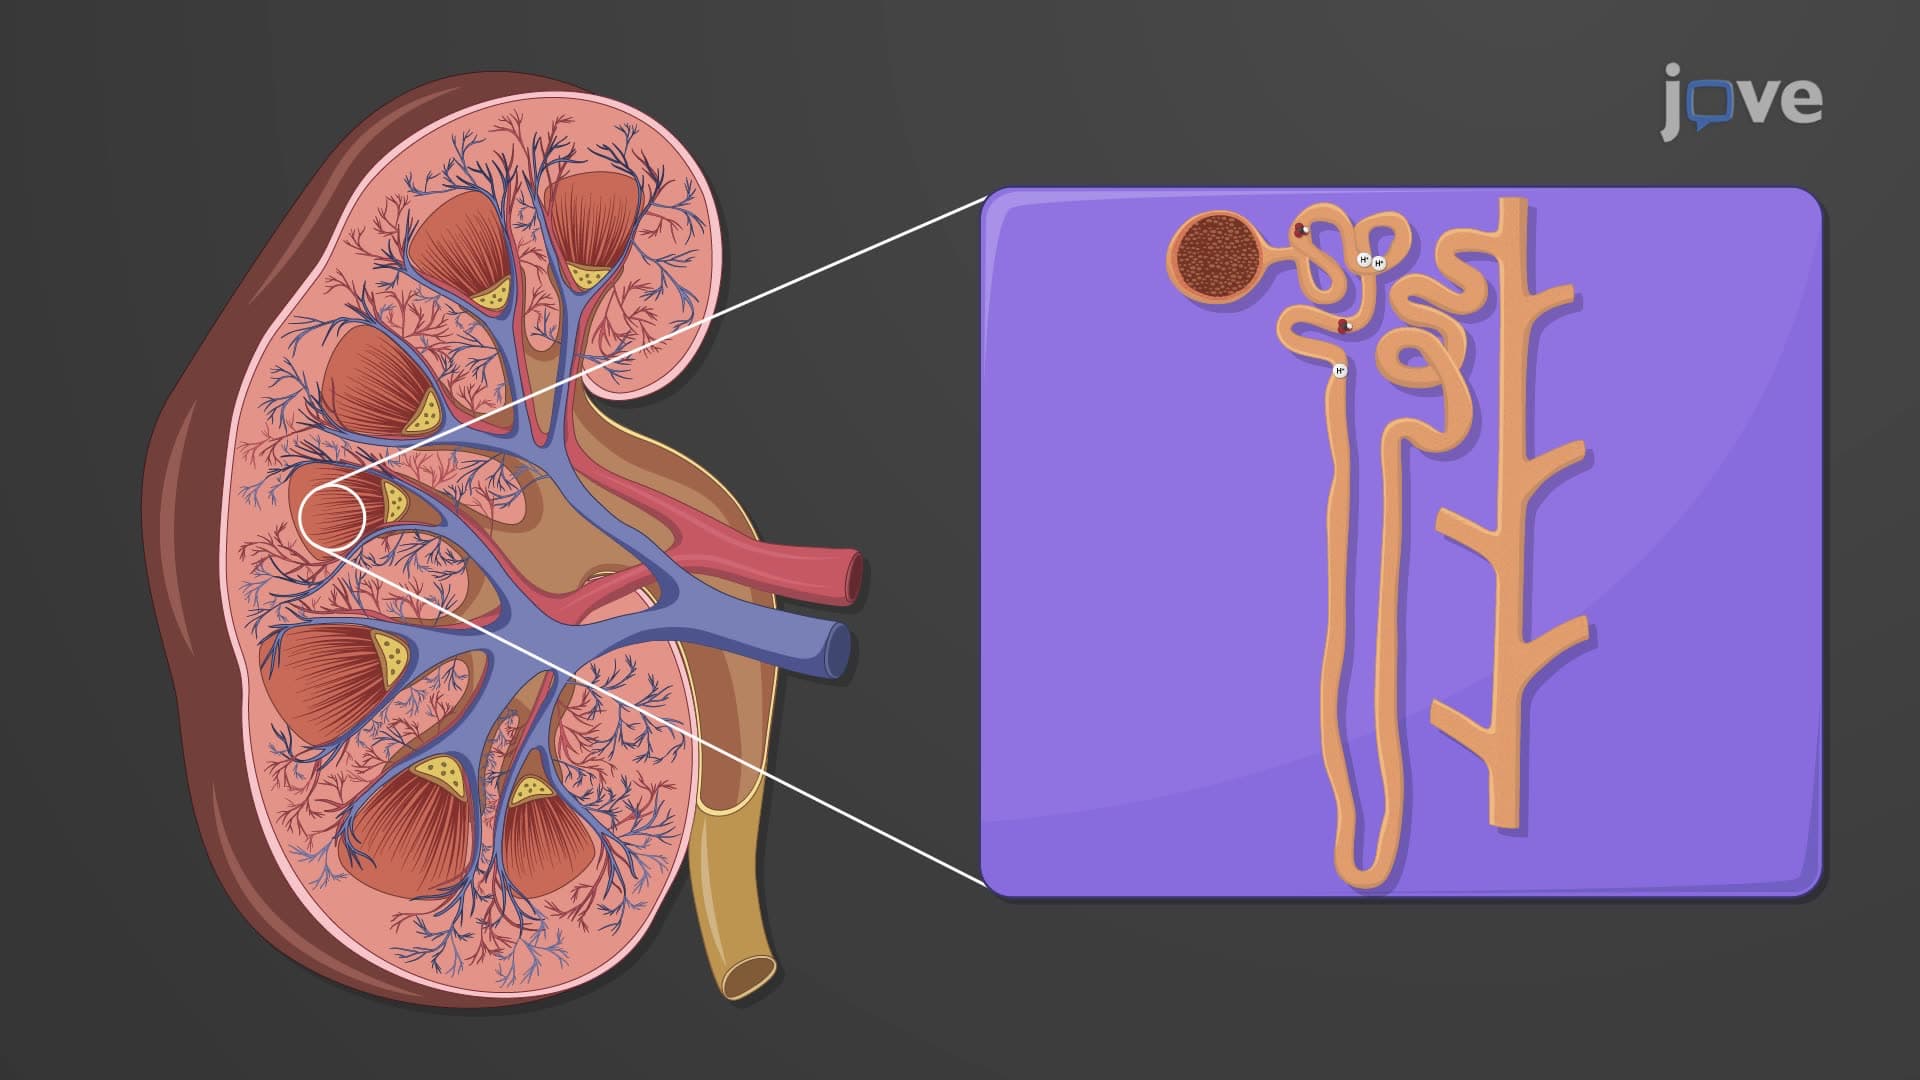
Metabolic reactions in the body produce nonvolatile acids, such as sulfuric acid, which generate an acid load of approximately 1 mEq of H+ per kilogram of body weight daily. Excreting H+ in the urine is essential to balance this acid load.
In the kidneys, cells within the proximal convoluted tubules (PCT) and the collecting ducts secrete hydrogen ions (H+) into the tubular fluid. Specifically, in the PCT, Na+/H+ antiporters secrete H+ while reabsorbing Na+.
However, the intercalated cells in...
In the kidneys, cells within the proximal convoluted tubules (PCT) and the collecting ducts secrete hydrogen ions (H+) into the tubular fluid. Specifically, in the PCT, Na+/H+ antiporters secrete H+ while reabsorbing Na+.
However, the intercalated cells in...
384