Characteristics of Pediatric In-Hospital Cardiac Arrests and Resuscitation Duration
Related Experiment Video
Updated: Jun 18, 2025

Author Spotlight: Simulating Pediatric Cardiac Surgery Using a Neonatal Piglet Model
Published on: May 26, 2023
Amanda O'Halloran1,2, Ryan W Morgan1, Kevin Kennedy3
1Department of Anesthesiology and Critical Care Medicine, University of Pennsylvania Perelman School of Medicine and Children's Hospital of Philadelphia, Philadelphia.

Insights
Cardiopulmonary resuscitation (CPR) duration impacts survival in pediatric cardiac arrest. Shorter CPR durations were linked to younger age, emergency department locations, and minority groups. Survival odds varied with hospital CPR duration quartiles.
Area of Science:
- Pediatric Emergency Medicine
- Cardiology
- Resuscitation Science
Background:
- Cardiopulmonary resuscitation (CPR) duration is a critical factor influencing survival rates in patients experiencing cardiac arrest.
- Understanding factors associated with CPR duration is essential for optimizing resuscitation strategies in pediatric populations.
Purpose of the Study:
- To identify patient and event characteristics associated with CPR duration in hospitalized children without return of circulation (ROC).
- To evaluate the association between hospital-level median CPR duration and survival to discharge among pediatric patients experiencing in-hospital cardiac arrest.
Main Methods:
- A retrospective cohort study utilizing data from the Get With the Guidelines-Resuscitation registry (2000-2021).
- Patient-level analysis assessed factors associated with CPR duration in children without ROC using multivariable hierarchical linear regression.
- Hospital-level analysis examined the association between CPR duration quartiles and survival to discharge using random intercept multivariable hierarchical logistic regression.
Main Results:
- Among 3,859 pediatric patients without ROC, factors like initial rhythm, age, event location, and race/ethnicity were associated with CPR duration.
- Shorter CPR durations were observed in neonates, emergency department locations, and among racial/ethnic minority groups.
- Survival to discharge varied significantly across hospital quartiles of median CPR duration for events without ROC, with intermediate durations showing higher survival odds.
Conclusions:
- Patient and event factors influence CPR duration in pediatric in-hospital cardiac arrest.
- Hospital-level median CPR duration is associated with survival to discharge, suggesting an optimal range.
- Further research is needed to establish optimal CPR duration guidelines and address disparities in pediatric resuscitation care.
Importance:
Cardiopulmonary resuscitation (CPR) duration is associated with cardiac arrest survival.
Objectives:
To describe characteristics associated with CPR duration among hospitalized children without return of circulation (ROC) (patient-level analysis) and determine whether hospital median CPR duration in patients without ROC is associated with survival (hospital-level analysis).
Design, Setting, And Participants:
This retrospective cohort study of patients undergoing pediatric in-hospital CPR between January 1, 2000, and December 31, 2021, used data from the Get With the Guidelines-Resuscitation registry. Children receiving chest compressions for at least 2 minutes and/or defibrillation were included in the patient-level analysis. For the hospital-level analysis, sites with at least 20 total events and at least 5 events without ROC were included. Data were analyzed from December 1, 2022, to November 15, 2023.
Exposures:
For the patient-level analysis, the exposure was CPR duration in patients without ROC. For the hospital-level analysis, the exposure was quartile of median CPR duration in events without ROC at each hospital.
Main Outcomes And Measures:
For the patient-level analysis, outcomes were patient and event factors, including race and ethnicity and event location; we used a multivariable hierarchical linear regression model to assess factors associated with CPR duration in patients without ROC. For the hospital-level analysis, the main outcome was survival to discharge among all site events; we used a random intercept multivariable hierarchical logistic regression model to examine the association between hospital quartile of CPR duration and survival to discharge.
Results:
Of 13 899 events, 3859 patients did not have ROC (median age, 7 months [IQR, 0 months to 7 years]; 2175 boys [56%]). Among event nonsurvivors, median CPR duration was longer in those with initial rhythms of bradycardia with poor perfusion (8.37 [95% CI, 5.70-11.03] minutes; P < .001), pulseless electrical activity (8.22 [95% CI, 5.44-11.00] minutes; P < .001), and pulseless ventricular tachycardia (6.17 [95% CI, 0.09-12.26] minutes; P = .047) (vs asystole). Shorter median CPR duration was associated with neonates compared with older children (-4.86 [95% CI, -8.88 to -0.84] minutes; P = .02), emergency department compared with pediatric intensive car7 e unit location (-4.02 [95% CI, -7.48 to -0.57] minutes; P = .02), and members of racial or ethnic minority groups compared with White patients (-3.67 [95% CI, -6.18 to -1.17]; P = .004). Among all CPR events, the adjusted odds of survival to discharge differed based on hospital quartile of median CPR duration among events without ROC; compared with quartile 1 (15.0-25.9 minutes), the adjusted odds ratio for quartile 2 (26.0-29.4 minutes) was 1.22 (95% CI, 1.09-1.36; P < .001); for quartile 3 (29.5-32.9 minutes), 1.23 (95% CI, 1.08-1.39; P = .002); and for quartile 4 (33.0-53.0 minutes), 1.04 (95% CI, 0.91-1.19; P = .58).
Conclusions And Relevance:
In this retrospective cohort study of pediatric in-hospital CPR, several factors, including age and event location, were associated with CPR duration in event nonsurvivors. The odds of survival to discharge were lower for patients at hospitals with the shortest and longest median CPR durations among events without ROC. Further studies are needed to determine the optimal duration of CPR during pediatric in-hospital cardiac arrest and to provide training guidelines for resuscitation teams to eliminate disparities in resuscitation care.
More Related Videos
 10:55
A Piglet Perinatal Asphyxia Model to Study Cardiac Injury and Hemodynamics after Cardiac Arrest, Resuscitation, and the Return of Spontaneous Circulation
Published on: January 13, 2023
 05:36
Standardized Model of Ventricular Fibrillation and Advanced Cardiac Life Support in Swine
Published on: January 30, 2020
Related Concept Videos
 01:23
Acute Respiratory Failure-IV
 01:26
Respiratory Volumes and Capacities I
 01:30
Cardiac Action Potential
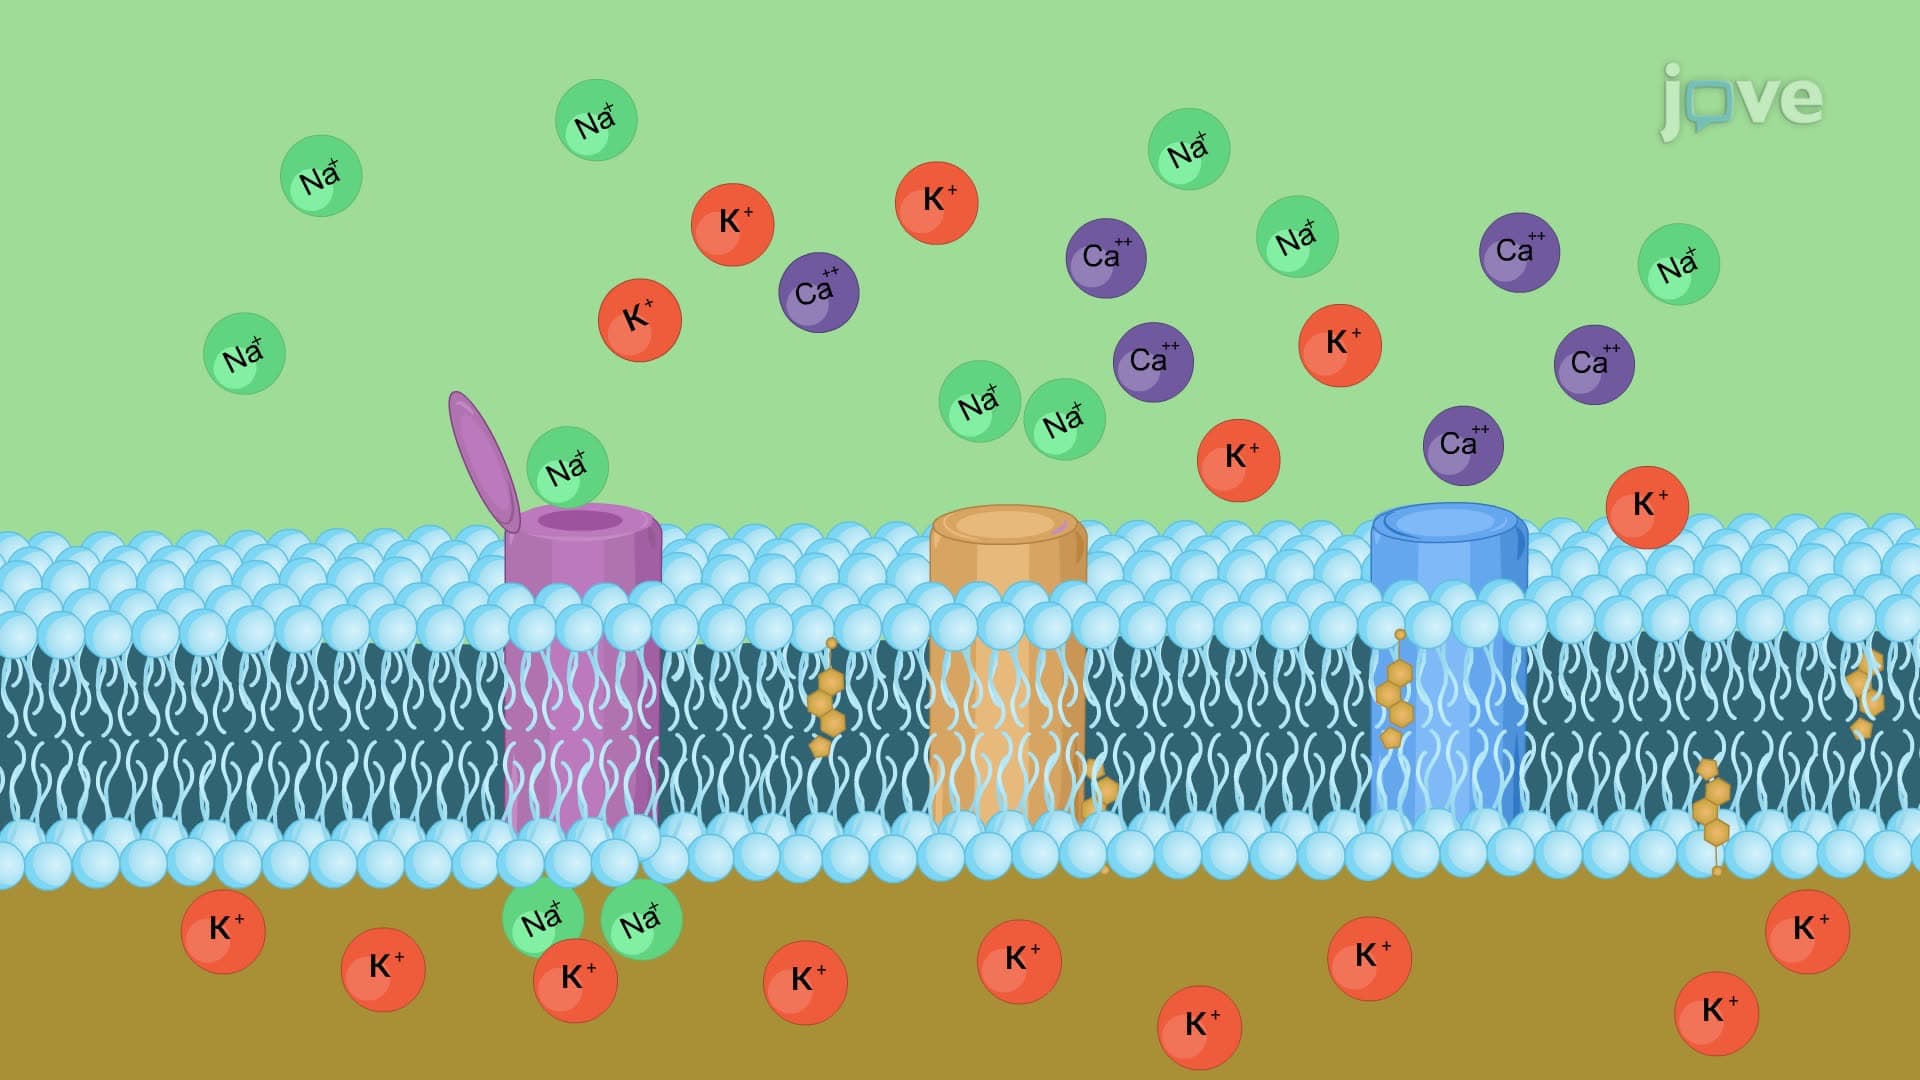
The cardiac action potential process involves a series of phases characterized by the movement of ions across the cardiac cell membranes, leading to the depolarization and repolarization of the cardiac myocytes.
Ionic Basis of Cardiac Action Potentials
 01:27
Specialized Characteristics of Cardiac Muscles
Cardiac muscle cells are smaller than skeletal muscles, averaging 10–20 mm in diameter and 50–100 mm in length. However, they have large energy demands for continuous contraction and relaxation. This energy is almost exclusively derived from aerobic metabolism of energy...
 01:20
Assessment of Ventilation I: Respiratory Rate
A Ventilation assessment is critical for monitoring a patient's health status. Respiration, one of the most accessible vital signs, provides insights into the function of numerous body systems and can indicate serious health issues, such as brainstem injuries from head trauma.
Critical Guidelines for Assessing Ventilation: