

Double coronary artery occlusion presenting as inferior ST segment elevation myocardial infarction and Wellens
Enrico Marchi1, Iacopo Muraca1, Daniel Cesarini1
1Interventional Cardiology Unit, Careggi University Hospital, Largo G.A. Brambilla 3, 50141 Florence, Italy.

Insights
ST elevation myocardial infarction (STEMI) with multiple blocked arteries is rare but dangerous, potentially causing shock. This case highlights a patient with simultaneous right coronary artery and left anterior descending artery occlusions, successfully treated with percutaneous coronary intervention.
Area of Science:
- Cardiovascular Medicine
- Interventional Cardiology
- Acute Coronary Syndromes
Background:
- ST-elevation myocardial infarction (STEMI) typically involves a single culprit lesion.
- Multiple coronary artery occlusions occur in 2.5% of STEMI cases, posing a significant risk.
- Simultaneous coronary artery occlusion can lead to life-threatening complications like cardiogenic shock and ventricular arrhythmias.
Background:
ST elevation myocardial infarctions are usually a consequence of the occlusion of a single coronary artery, but in 2.5% of the cases, two or more culprit lesions are found. Simultaneous coronary artery occlusion is a potentially life-threatening condition that leads to cardiogenic shock or ventricular arrhythmias.
Case Summary:
We presented the case of a 74-year-old man presenting with chest pain and ST segment elevation (STE) in inferior leads and evidence of alternating STE in anterior leads in a pattern like Wellens syndrome type A in subsequent electrocardiogram (ECGs). Emergency coronary angiography (CA) revealed thrombotic occlusion of the proximal right coronary artery (RCA) and sub-occlusion of mid left anterior descending artery (LAD). During the CA, he became haemodynamically unstable requiring intravenous inotropes and vasopressors, and he underwent primary percutaneous coronary intervention of both RCA and LAD culprit lesions. His subsequent hospital stay was uneventful, and he was discharged 5 days later.
Discussion:
ST elevation myocardial infarction with more than one culprit coronary artery is a rare but at high risk of haemodynamic decompensation. The causes of occlusion of multiple coronary arteries may be several: coronary embolism, coronary ectasia, simultaneous plaque disruption, coronary vasospasm, hypercoagulability states, smoking, and illicit drug abuse. The presumed mechanism behind the presented case may be a combination of release of pro-thrombotic cytokines due to the thrombotic occlusion of the first coronary and low output state secondary to myocardial dysfunction leading to impaired flow in a severe stenotic coronary artery with subsequent thrombosis.


Related Concept Videos
 01:21
Coronary Circulation
Coronary circulation begins at the base of the aorta, where two main arteries arise—the left and right coronary arteries. These arteries encircle the heart in the coronary sulcus and supply the...
 01:17
Ischemic Heart Disease: Overview
Atherosclerosis, the primary malefactor, orchestrates this dangerous condition. It manifests as the accumulation of fatty deposits, akin to insidious plaques, within arterial walls. As time elapses, these plaques metamorphose, hardening and...
 01:25
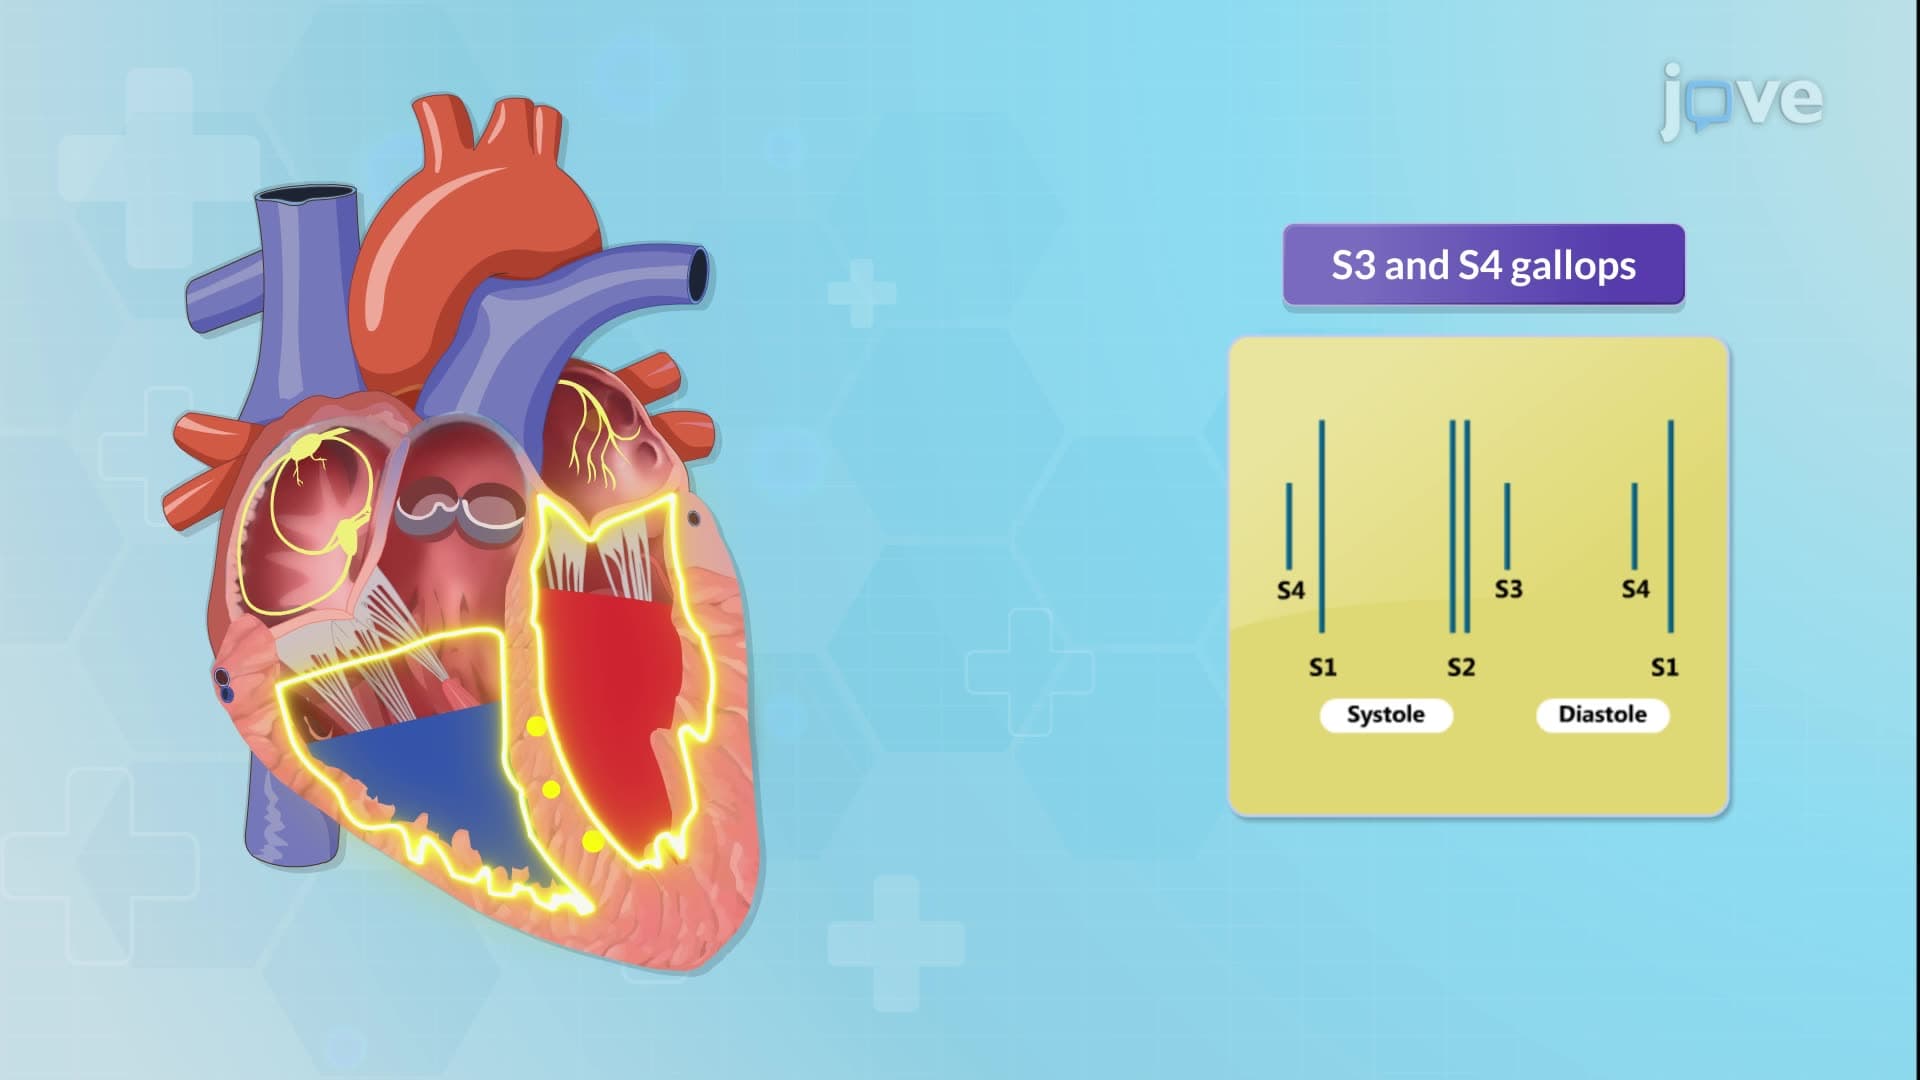
Cardiovascular System Abnormal Findings II: Auscultation
Abnormal Heart Sounds
Gallops:
 01:18
Physiology of the Heart: The Cardiac Cycle
Diastole: The Relaxation Phase
During diastole, all four heart chambers relax. The atrioventricular (AV) valves open, and the semilunar valves close. This phase sees the lowest chamber pressures, promoting ventricular filling. Venous blood enters the heart through the...