Related Experiment Video
Updated: Jun 14, 2025
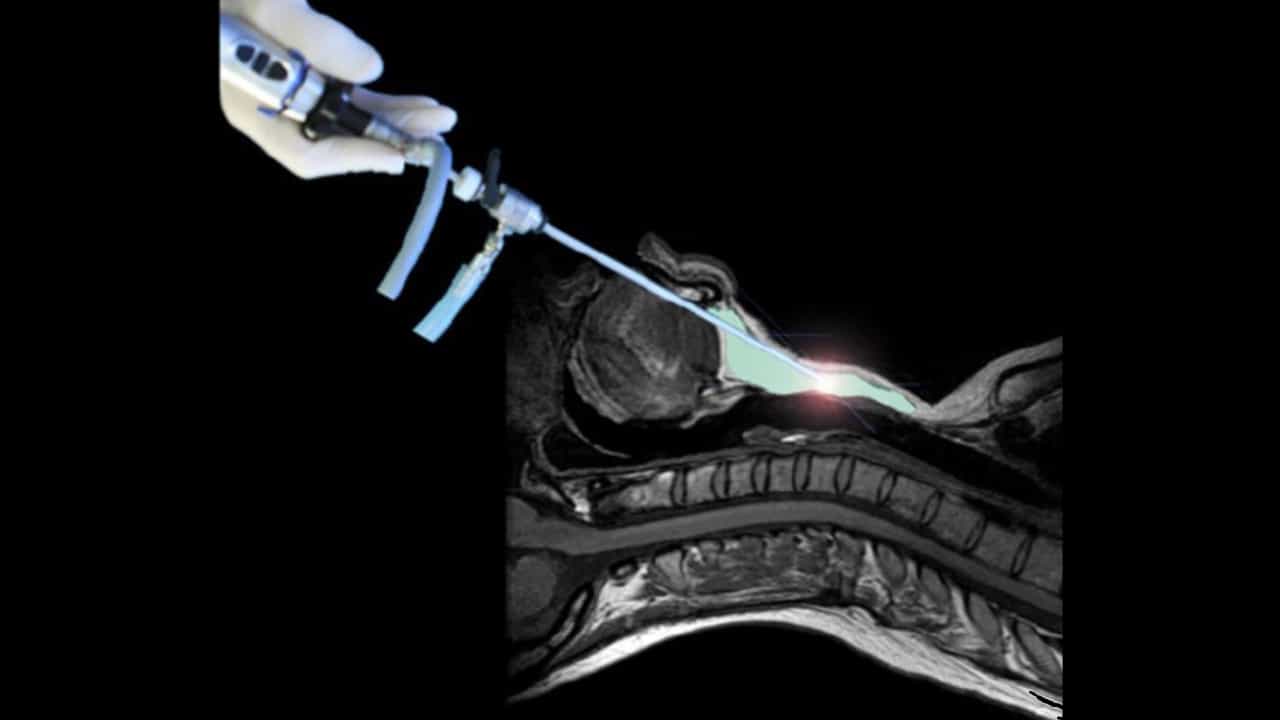

Transoral Robotic Total Thyroidectomy and Bilateral Central Regional Lymph Node Dissection for Papillary Thyroid Carcinoma
Published on: September 15, 2023
Postoperative radiotherapy for completely resected thymoma and thymic carcinoma: A systematic review and
Tianyu He1, Jiacheng Yao1, Jun Chen2
1Department of Radiation Oncology, The First Hospital of China Medical University, Shenyang, China.

Background:
The role of postoperative radiotherapy (PORT) after complete tumor resection in patients with thymoma or thymic carcinoma remains controversial. We performed a meta-analysis to identify groups that would benefit from PORT.
Methods:
Multiple scientific databases were systematically searched for studies comparing overall survival (OS) and/or disease-free survival (DFS) between PORT and surgery alone in patients with completely resected thymomas or thymic carcinomas until April 10, 2024. A random-effects model was used for the statistical analysis.
Results:
A total of 31 studies with 10543 patients were included (17 studies involving 4763 patients with thymoma, seven studies involving 1045 patients with thymic carcinoma, and seven studies involving 4735 patients with mixed histological types). Notably, PORT significantly prolonged OS (hazard ratio [HR] = 0.73, 95% confidence interval [CI]: 0.59-0.91) and DFS (HR = 0.62, 95% CI: 0.43-0.89). Similar results were also observed when the multivariate-adjusted HRs were used as the measure of effect (OS: HR = 0.60, 95% CI: 0.43-0.83; DFS: HR = 0.48, 95% CI: 0.29-0.79). In subgroup analyses, PORT was associated with a longer OS and DFS for thymoma (HR = 0.73, 95% CI: 0.56-0.96 and HR = 0.65, 95% CI: 0.46-0.93), thymic carcinoma (HR = 0.72, 95% CI: 0.49-1.07 and HR = 0.38, 95% CI: 0.19-0.77), and stage 3-4 disease (HR = 0.50, 95% CI: 0.34-0.74 and HR = 0.44, 95% CI: 0.27-0.70), but not for stage 2 disease (HR = 0.81, 95% CI: 0.55-1.19 and HR = 0.97, 95% CI: 0.51-1.83).
Conclusions:
PORT is likely to improve OS and DFS in patients with completely resected stage 3-4 thymoma or thymic carcinoma; however, the value of PORT for stage 2 disease requires further evaluation in large-scale studies.

