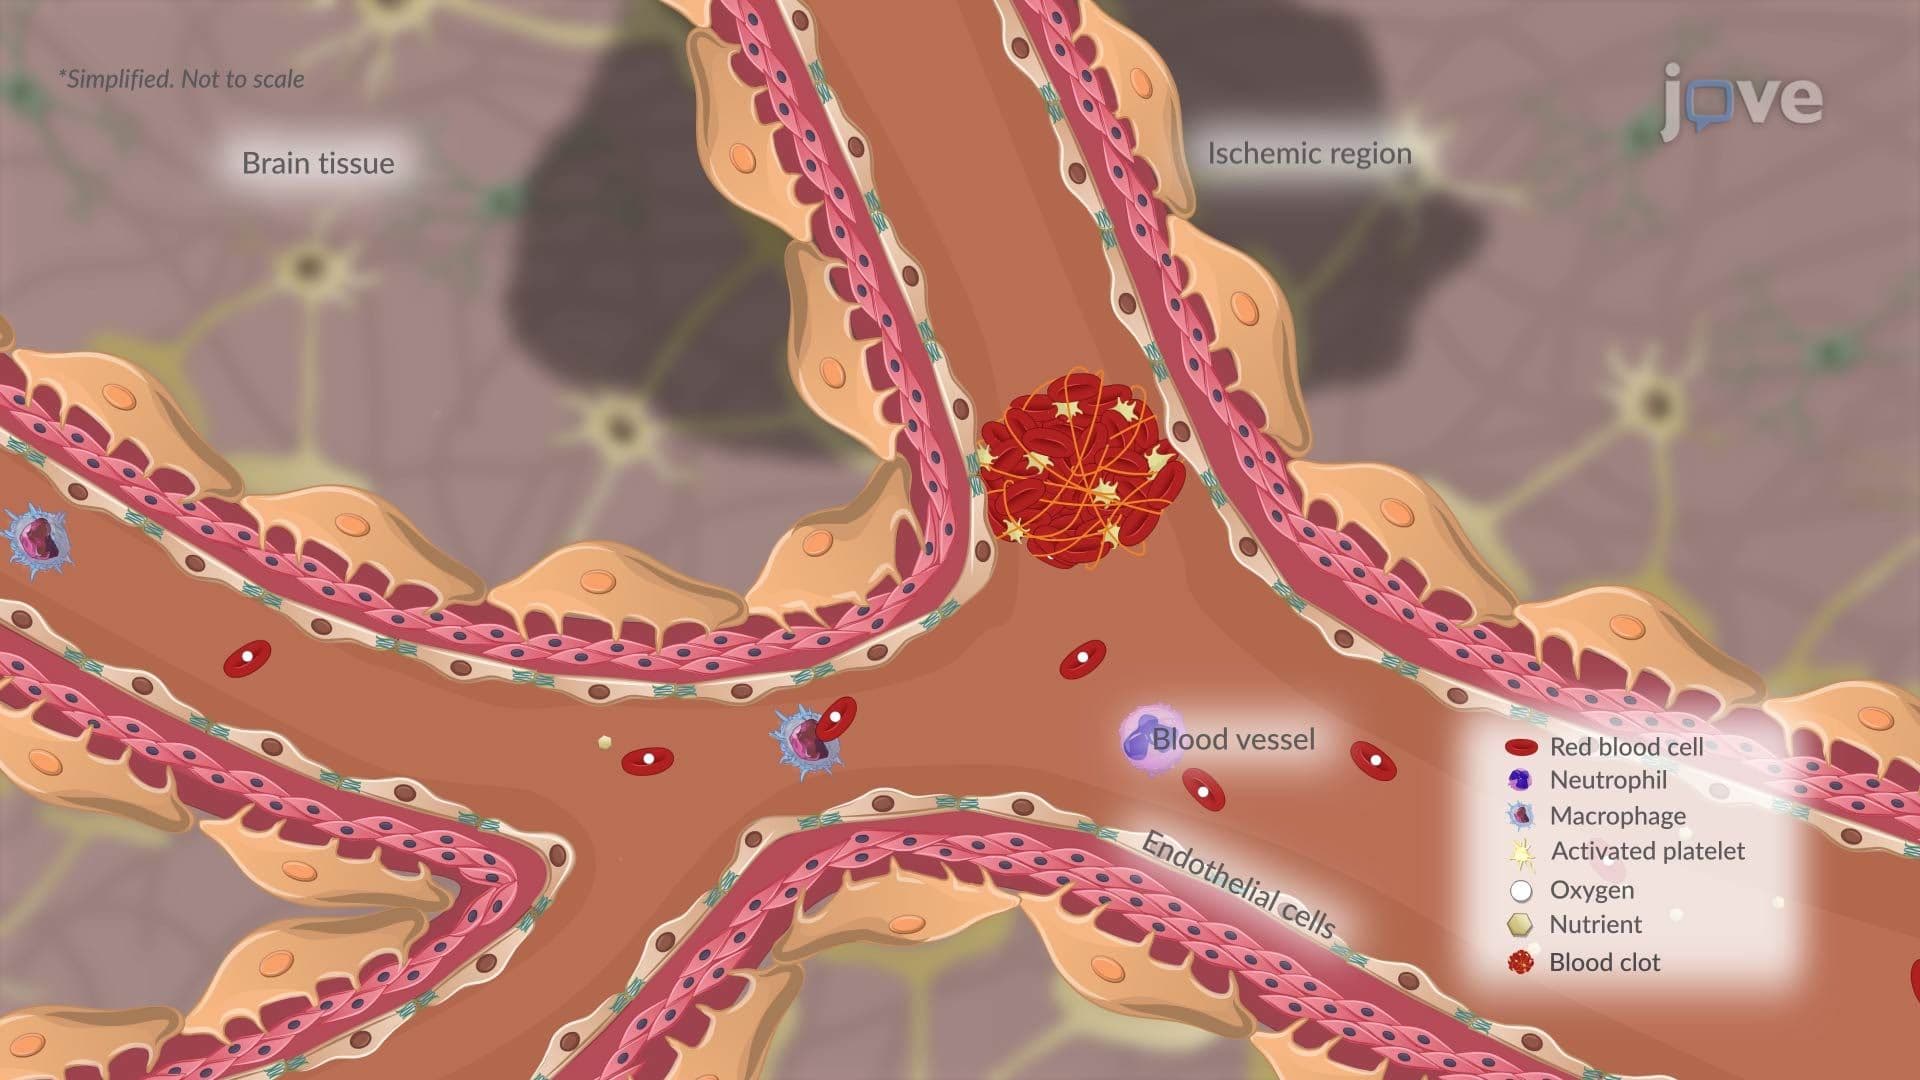
Cerebral perfusion in patients with unilateral internal carotid artery occlusion by dual post-labeling delays arterial spin labeling imaging
Related Experiment Video
Updated: May 2, 2026
Optimized System for Cerebral Perfusion Monitoring in the Rat Stroke Model of Intraluminal Middle Cerebral Artery Occlusion
Published on: February 17, 2013
Gui-Rong Zhang1, Yan-Yan Zhang1, Wen-Bin Liang1
1Department of Medical Imaging, The Second Affiliated Hospital of Xi'an Jiaotong University, Xi'an 710043, Shaanxi Province, China.

Background:
Global and regional cerebral blood flow (CBF) changes in patients with unilateral internal carotid artery occlusion (ICAO) are unclear when the dual post-labeling delays (PLD) arterial spin labeling (ASL) magnetic resonance imaging (MRI) technique is used. Manual delineation of regions of interest for CBF measurement is time-consuming and laborious.
Aim:
To assess global and regional CBF changes in patients with unilateral ICAO with the ASL-MRI perfusion technique.
Methods:
Twenty hospitalized patients with ICAO and sex- and age-matched controls were included in the study. Regional CBF was measured by Dr. Brain's ASL software. The present study evaluated differences in global, middle cerebral artery (MCA) territory, anterior cerebral artery territory, and Alberta Stroke Program Early Computed Tomography Score (ASPECTS) regions (including the caudate nucleus, lentiform nucleus, insula ribbon, internal capsule, and M1-M6) and brain lobes (including frontal, parietal, temporal, and insular lobes) between ICAO patients and controls at PLD 1.5 s and PLD 2.5 s.
Results:
When comparing CBF between ICAO patients and controls, the global CBF in ICAO patients was lower at both PLD 1.5 s and PLD 2.5 s; the CBF on the occluded side was lower in 15 brain regions at PLD 1.5 s, and it was lower in 9 brain regions at PLD 2.5 s; the CBF in the contralateral hemisphere was lower in the caudate nucleus and internal capsule at PLD 1.5 s and in M6 at PLD 2.5 s. The global CBF in ICAO patients was lower at PLD 1.5 s than at PLD 2.5 s. The ipsilateral CBF at PLD 1.5 s was lower than that at PLD 2.5 s in 15 regions, whereas the contralateral CBF was lower at PLD 1.5 s than at PLD 2.5 s in 12 regions. The ipsilateral CBF was lower than the contralateral CBF in 15 regions at PLD 1.5 s, and in M6 at PLD 2.5 s.
Conclusion:
Unilateral ICAO results in hypoperfusion in the global and MCA territories, especially in the ASPECTS area. Dual PLD settings prove more suitable for accurate CBF quantification in ICAO.
More Related Videos
 06:59
Middle Cerebral Artery Occlusion Allowing Reperfusion via Common Carotid Artery Repair in Mice
Published on: January 23, 2019
 05:23
Author Spotlight: Noninvasive Cerebral Blood Flow Determination in Human Functional Brain Region for Diagnosis of Neurological Disorders
Published on: May 31, 2024