Related Experiment Video
Updated: Jun 11, 2025
Low-Cost Single-Port LoCoSP Device for a Transcervical Approach in Minimally Invasive Transhiatal Esophagectomy
Published on: September 11, 2021
Robot-assisted minimally invasive esophagectomy for esophageal cancer in the left lateral decubitus position
Shigeru Lee1, Tatsuro Tamura2, Yuichiro Miki2
1Department of Gastroenterological Surgery, Osaka Metropolitan University Graduate School of Medicine, 1-4-3, Asahimachi, Abeno-ku, Osaka, 545-8585, Japan. sgr-lee@omu.ac.jp.

Background:
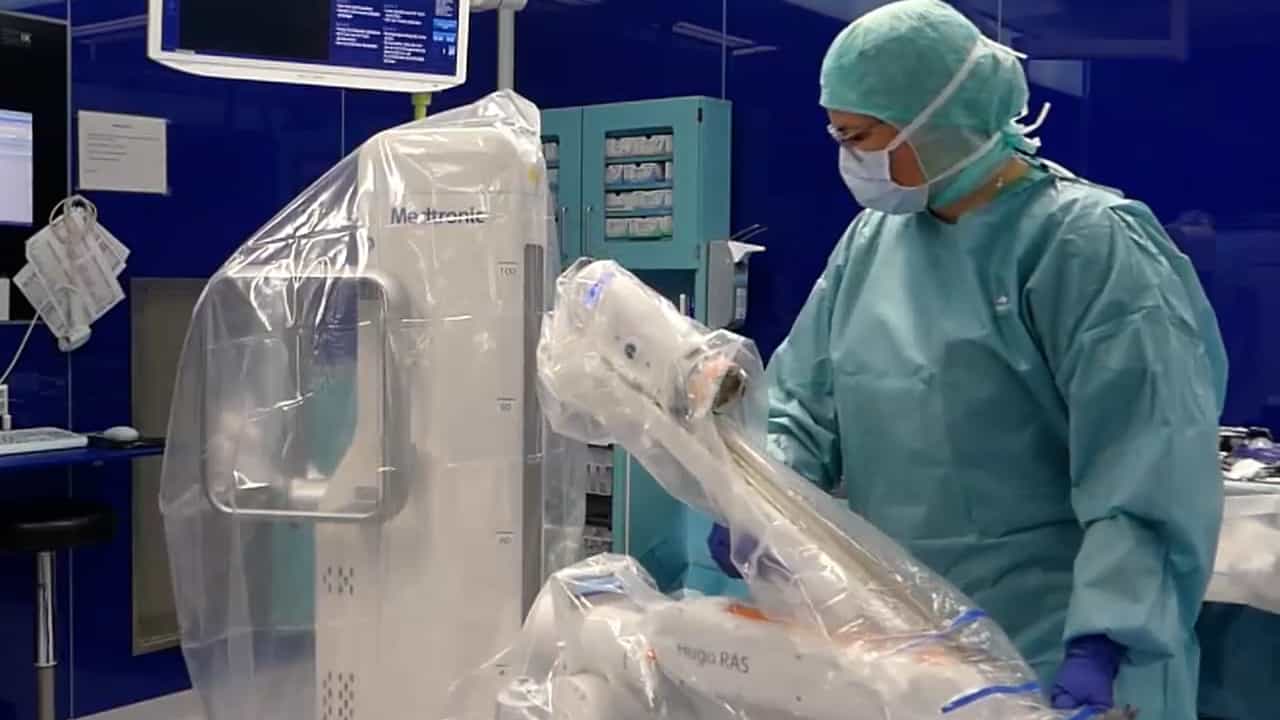
The use of robot-assisted minimally invasive esophagectomy (RAMIE) in the prone position for esophageal cancer has been currently increasing worldwide. In future, as surgical-assisted robots become more widespread, it is estimated that only two methods of transthoracic approach will remain: RAMIE and open thoracotomy for thoracic esophageal cancer. RAMIE in the left lateral decubitus position (RAMIE-LLDP) has the same field of view as open thoracotomy, is safe in emergency situations, and provides education on open thoracotomy.
Methods:
Between September 2020 and April 2024, RAMIE-LLDP was performed in 64 consecutive patients with esophageal cancer. RAMIE-LLDP was performed with the operating table rotated and tilted 45° to the ventral side under artificial pneumothorax. The hand-control setting of the surgical-assist robot system was reversed left to right when the Patient Cart was rolled from the same direction as the RAMIE in the prone position.
Results:
The mean total surgery and console times during the thoracic procedure were 254-min overall and 225 min in the last 24 cases and 195-min overall and 178- min in the last 24 cases, respectively. The mean amount of blood loss was 203.4 g overall and 28.3 g in the last 24 cases. Postoperative recurrent laryngeal nerve palsy with Clavien-Dindo classification (CD) was ≥ 2 in six patients (9.4%). Postoperative pneumonia with CD ≥ 2 was observed in 11 patients (17.2%). Conversion to open thoracotomy was observed in three patients (4.7%). In all three patients, an immediate conversion to thoracotomy without patients' position change was actually possible and no serious complications were noted. No mortality occurred within 30 days postoperatively.
Conclusion:
RAMIE-LLDP which facilitates emergency thoracotomy has perioperative results comparable to those of conventional thoracoscopic esophagectomy and is educational for open surgery. RAMIE-LLDP is the safest and most optimal surgery for esophageal cancer.