Related Experiment Video
Updated: Jun 10, 2025
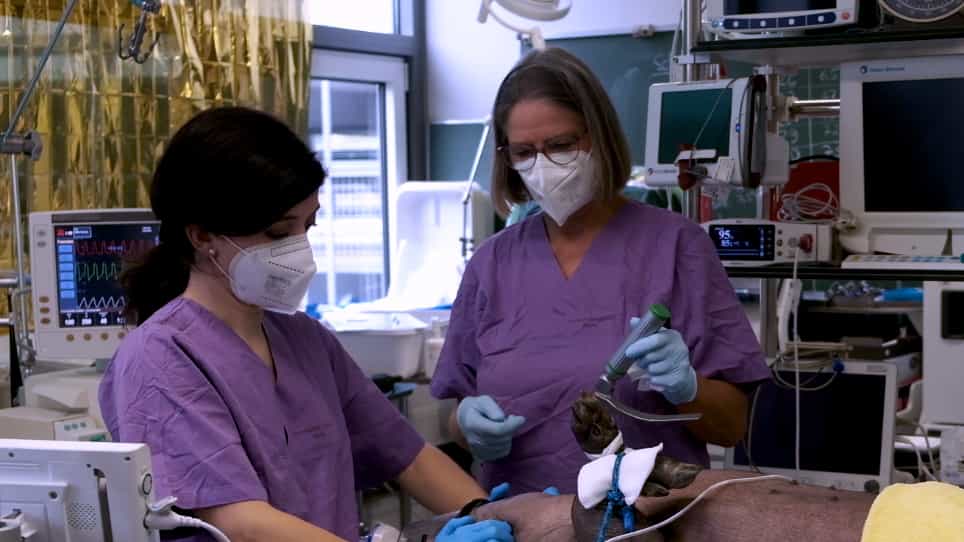

Endotracheal Intubation Using a Flexible Intubation Endoscope as a Standardized Model for Safe Airway Management in Swine
Published on: August 25, 2022
Effect of administration sequence of induction agents on first-attempt failure during emergency intubation: A
Pierre Catoire1,2, Brian Driver3, Matthew E Prekker3,4
1Emergency Department, Hôpital Pitié-Salpêtrière, Assistance-Publique Hôpitaux de Paris, Paris, France.

Background:
Emergency tracheal intubation is associated with a risk of clinical adverse events, including the risk of first-attempt failure. Induction agents usually include a sedative and a neuromuscular blocking agent (i.e., paralytic). Whether the order of administration (i.e., sedative vs. paralytic given first) is associated with first-attempt failure or adverse events is unknown.
Methods:
This study analyzed data from a single-center prospective cohort collected from 2021 to 2024 at Hennepin County Medical Center, which included all patients undergoing orotracheal intubation in the emergency department. Patients with no detail on administration sequence order were excluded. A Bayesian logistic regression analysis was used to measure the effect of drug sequence order (sedative first vs. paralytic first). The primary outcome was first-attempt failure. The key secondary outcome was peri-intubation hypoxemia (SpO2 < 90%). We estimated the odds ratio (OR), 95% credible interval (CrI), and the probability that the OR was inferior to 1 (existence of an effect) and inferior to 0.9 (significant effect). Frequentist analysis and reanalysis with various priors were performed as sensitivity analyses.
Results:
A total of 2216 patients were included for analysis. The most frequently used sedative and paralytic agents were etomidate (88.9%) and rocuronium (77.8%), respectively. The paralytic was given first to 56.6% of the patients. After adjustment for age, sex, body mass index, and sedative and paralytic agents, the OR for a paralytic-first strategy for first-attempt failure was 0.73 (95% CrI 0.46-1.02). The probability that the OR was less than 1 was estimated at 95.7% and less than 0.9 at 87.6%. There was a 33.5% and 8.0% probability that administering the paralytic first resulted in an OR < 1 and OR < 0.9 for the risk of hypoxemia, respectively. Sensitivity analyses were consistent with the main results.
Conclusions:
In this Bayesian analysis a paralytic-first drug sequence was associated with reduced first-attempt failure during emergency tracheal intubation.


Related Concept Videos
 01:15
Endotracheal Intubation I: Procedure
The ET tube comprises various components, including a standard adaptor to attach a bag-valve-mask (BVM) or ventilator, a cuff, a pilot balloon, and radiopaque markings along its length to measure the insertion distance. The tube sizes...
 01:17
Endotracheal Intubation II: Nursing Management
1. Nursing Care of Patients Before Intubation
Before the endotracheal intubation procedure, nurses play an essential role in ensuring the process goes smoothly. The nurses must be familiar with intubation...
 01:24
Endotracheal Tube Extubation
Procedure
Extubation removes the endotracheal tube (ETT) from the patient on mechanical ventilation. It requires a well-coordinated, multidisciplinary approach involving physicians, nurses, respiratory therapists, and other healthcare professionals....
 01:30
Cardiopulmonary Resuscitation V: Advanced Airway Management Techniques
 01:22
Cardiopulmonary Resuscitation II: ACLS Airway Management
 01:19
Depolarizing Blockers: Pharmocokinetics