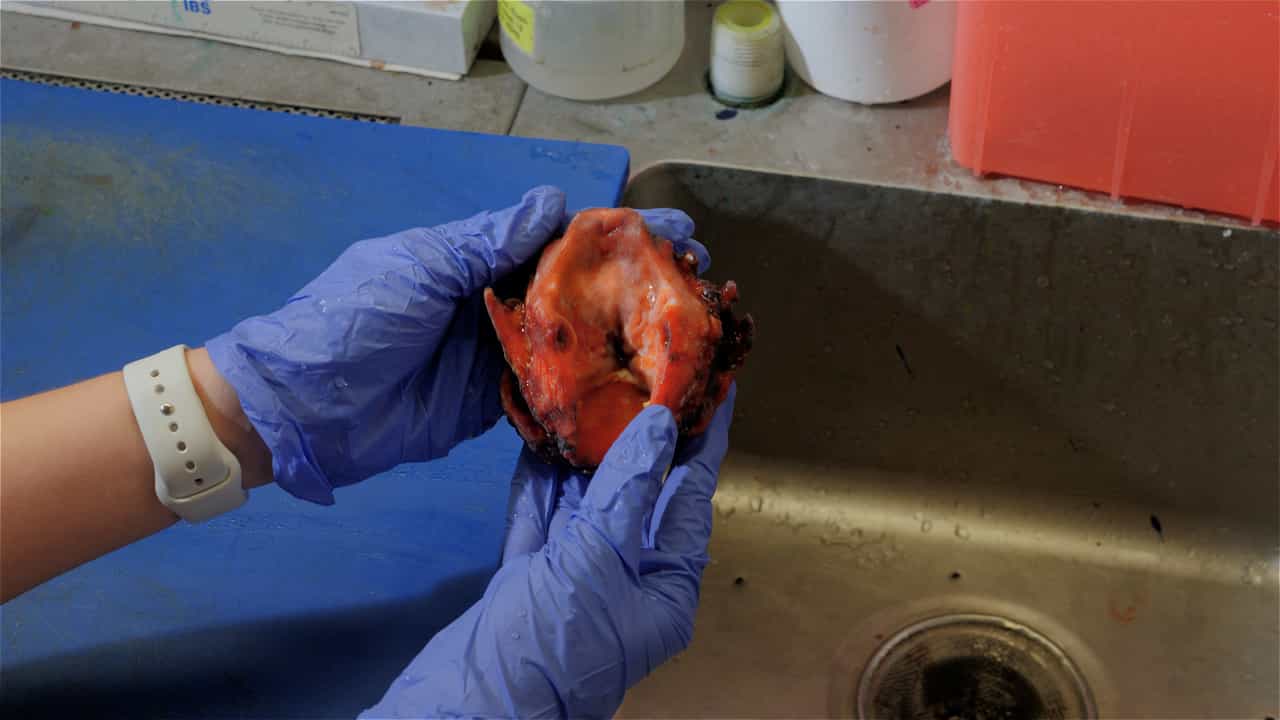
Related Experiment Video
Updated: Jun 8, 2025

Intraoperative Assessment of Resection Margins in Oral Cavity Cancer: This is the Way
Published on: May 10, 2021
Margin-to-depth ratio as an independent prognostic factor in resected oral cavity squamous cell carcinoma: A
Hanpon Klibngern1, Chung-Jan Kang2, Li-Yu Lee3
1Department of Otolaryngology, Faculty of Medicine, Chiang Mai University, Chiang Mai 50200, Thailand.

Background:
The prognostic significance of margin-to-depth ratio (MDR) in oral cavity squamous cell carcinoma (OCSCC) remains unclear, particularly in comparison to traditional margin status. We aimed to examine the association between MDR and clinical outcomes in a large Taiwanese cohort.
Methods:
A total of 18,324 patients with first primary OCSCC were categorized by margin status: positive (1013), <5 mm (8371), and ≥ 5 mm (8940). Disease-specific survival (DSS) and overall survival (OS) served as the main outcome measures.
Results:
After excluding patients with positive margins (MDR = 0), the optimal MDR cutoff value for DSS and OS was 0.6. Patients with MDR > 0.6 showed significantly better 5-year DSS and OS rates (87 %, 81 %) compared to those with MDR ≤ 0.6 (71 %, 63 %) and MDR = 0 (53 %, 43 %). Multivariable analysis identified MDR ≤ 0.6 as independently associated with both DSS and OS in the entire cohort (hazard ratio [HR] = 1.34/1.32). This finding was consistent in the subgroups with surgical margins < 5 mm (HR = 1.39 for DSS and 1.38 for OS) and margins ≥ 5 mm (HR = 1.21 for both DSS and OS). In subgroups with surgical margins < 5 mm and ≥ 5 mm, an MDR > 0.6 was associated with better survival outcomes.
Conclusions:
An MDR (cutoff: 0.6) is independently associated with prognosis in OCSCC, offering improved risk stratification compared to margin status alone. While MDR may guide surgical margin modification, further research is needed to determine whether MDR could serve as a postoperative indicator for adjuvant therapy in patients with close or clear margins.