Related Experiment Video
Updated: Jun 13, 2025
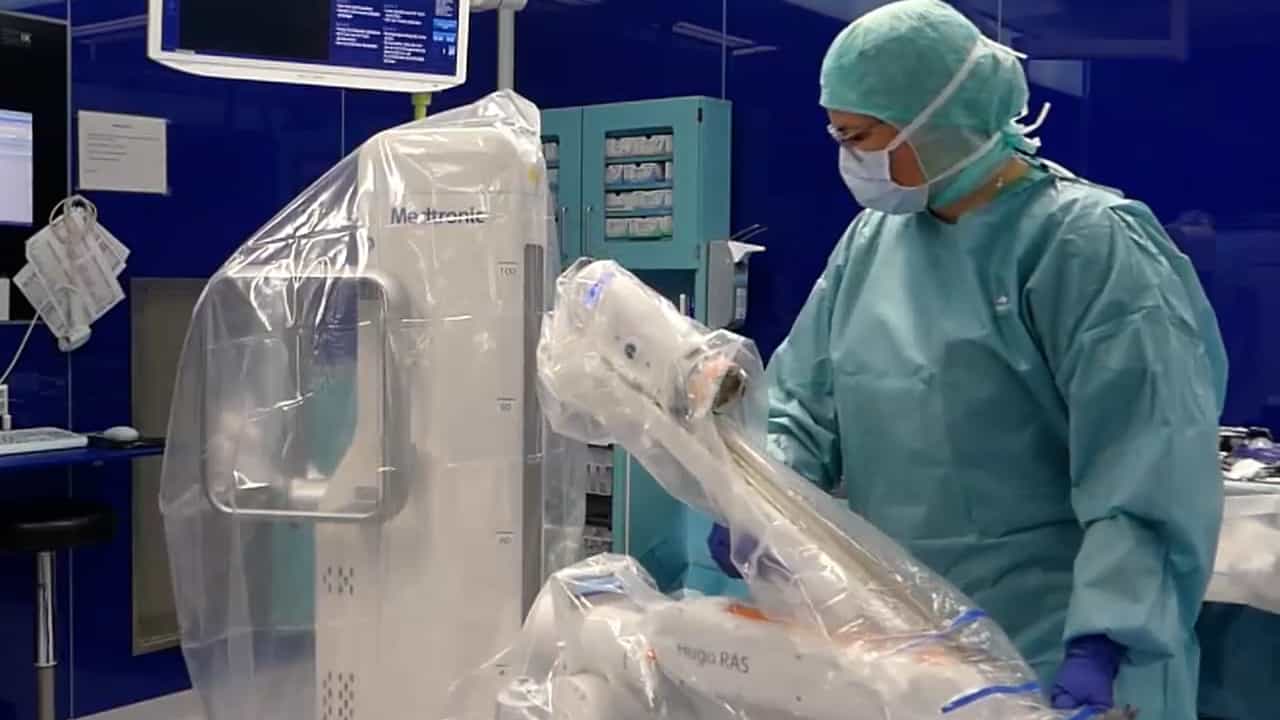

Robotics in Surgery: A Modular Robotic Platform Driven Gastric Wedge Resection
Published on: February 7, 2025
Identification and Categorization of Technical Errors and Hazard Zones of Robotic Versus Laparoscopic Total
Zhuoyu Jia1, Shougen Cao1, Daosheng Wang1
1Department of Gastrointestinal Surgery, Affiliated Hospital of Qingdao University, Qingdao and Gastrointestinal Tumor Translational Medicine Research Institute of Qingdao University, China.

Objective:
The current research aimed to conduct a detailed analysis of intraoperative surgical performance, short-term outcomes, identify and categorize technical errors, and hazard zones enacted during total gastrectomy performed robotically and laparoscopically by surgeons. Prospective research is needed to determine whether the technical advantages of robotic surgery translate to patient outcomes.
Background:
At present, a growing number of clinical studies have demonstrated that the quality of intraoperative surgical performance has a direct impact on the clinical outcomes of the patient. The current research aimed to conduct a detailed analysis of intraoperative surgical performance and short-term outcomes, and identify and categorize technical errors, and hazard zones enacted during total gastrectomy performed robotically and laparoscopically by surgeons.
Methods:
Eighty-two patients were recruited and participated in this study, with 40 cases undergoing RTG and 42 cases for LTG. Patients undergoing RTG and LTG were recruited and randomized into the study. Six consultant/attending surgeons participated in this study and all surgical procedures were recorded. The unedited surgical video recordings were handed over to third-party experts for granular analysis of the procedures using objective clinical human reliability analysis for the quality of intraoperative performance, technical errors, and intraoperative complications.
Results:
The technical errors enacted and identified in the RTG and the LTG were 46.11 ± 5.63 versus 58.79 ± 8.45 ( P < 0.001), respectively. The highest number of technical errors was identified during the dissection of the supra-pancreatic lymph nodes (task zone 3), including No. 5, 7, 8a, 9, 11p, and 12a to complete the nodal clearance around the celiac artery and its trifurcation (7.29 ± 1.88 vs 9.43 ± 2.24, P < 0.001) in both RTG and LTG. The number of lymph nodes harvested with RTG was higher than LTG (35.36 ± 7.51 vs 30.54 ± 6.95, P = 0.016), especially in the upper margin of the pancreas (13.32 ± 4.17 vs 9.36 ± 3.81, P < 0.001). The total cost of hospitalization in the RTG group is 3% more than the LTG group ($15953.41±3533.91 vs $12198.26±2761.27, P < 0.001).
Conclusions:
This study offers compelling objective clinical human reliability analysis evidence demonstrating that RTG facilitates significantly superior technical performance compared with LTG. Whether examining short-term clinical outcomes or intraoperative operations, the robotic surgery system consistently outperforms laparoscopic surgery. Lymph node dissection in the supra-pancreatic region emerged as a major hazard zone in both procedures.
More Related Videos
 10:31
Intraoperative Gastroscopy for Tumor Localization in Laparoscopic Surgery for Gastric Adenocarcinoma
Published on: August 9, 2016
 03:32
Single Incision Plus One Port Laparoscopic Proximal Gastrectomy with Double Channel Anastomosis for Gastric Cancer Treatment
Published on: December 27, 2024