Related Experiment Video
Updated: Jun 7, 2025

A Semi-Automated and Reproducible Biological-Based Method to Quantify Calcium Deposition In Vitro
Published on: June 2, 2022
The Effect of Denosumab on Risk for Emergently Treated Hypocalcemia by Stage of Chronic Kidney Disease : A Target
Steven T Bird1, Kate Gelperin1, Elizabeth R Smith2
1Office of Pharmacovigilance and Epidemiology, Center for Drug Evaluation and Research, U.S. Food and Drug Administration, Silver Spring, Maryland (S.T.B., K.G., A.N., D.J.G.).

Background:
There is a paucity of data on treatment of osteoporosis in patients with advanced chronic kidney disease (CKD).
Objective:
To assess the risk for emergently treated hypocalcemia with denosumab by stage of CKD and presence of CKD-mineral and bone disorder (CKD-MBD).
Design:
Target trial emulation.
Setting:
Medicare fee-for-service data with prescription drug coverage, 2012 to 2020.
Participants:
Female patients aged 65 years or older initiating denosumab, oral bisphosphonates, or intravenous (IV) bisphosphonates for osteoporosis.
Measurements:
Hospital and emergency department admissions (that is, emergent care) for hypocalcemia were assessed in the first 12 treatment weeks. Inverse probability of treatment weighted cumulative incidence and weighted risk differences (RDs) were calculated.
Results:
A total of 361 453 patients treated with denosumab, 829 044 treated with oral bisphosphonates, and 160 413 treated with IV bisphosphonates were identified. Risk for emergently treated hypocalcemia with denosumab versus oral bisphosphonates increased with worsening CKD stage (P < 0.001), with greatest risk among dialysis-dependent (DD) patients (3.01% vs. 0.00%; RD, 3.01% [95% CI, 2.27% to 3.77%]) and non-dialysis-dependent (NDD) patients with CKD stages 4 and 5 (0.57% vs. 0.03%; RD, 0.54% [CI, 0.41% to 0.68%]). Among patients with stages 4 and 5 CKD (NDD + DD), denosumab had a greater risk for emergently treated hypocalcemia versus oral bisphosphonates in those with CKD-MBD (1.53% vs. 0.02%; RD, 1.51% [CI, 1.21% to 1.78%]) than in those without CKD-MBD (0.22% vs. 0.03%; RD, 0.19% [CI, 0.08% to 0.31%]). Denosumab also showed increased risk compared with IV bisphosphonates.
Limitation:
Generalizability to men and non-Medicare populations.
Conclusion:
Risk for emergently treated hypocalcemia with denosumab increased with worsening CKD stage and was highest in DD patients and those with CKD-MBD.
Primary Funding Source:
U.S. Food and Drug Administration.
Insights
Denosumab poses an increased risk of emergent hypocalcemia in osteoporosis patients with advanced chronic kidney disease (CKD). The risk is highest in dialysis-dependent patients and those with CKD-mineral and bone disorder (CKD-MBD).
Area of Science:
- Nephrology
- Endocrinology
- Pharmacology
Background:
- Osteoporosis treatment in advanced chronic kidney disease (CKD) lacks sufficient data.
- Assessing denosumab's safety profile in CKD patients is crucial.
Purpose of the Study:
- To evaluate the risk of emergent hypocalcemia associated with denosumab treatment in patients with varying stages of CKD.
- To investigate the influence of CKD-mineral and bone disorder (CKD-MBD) on this risk.
Main Methods:
- Target trial emulation using Medicare fee-for-service data (2012-2020).
- Analysis included female patients aged 65+ initiating denosumab, oral bisphosphonates, or IV bisphosphonates.
- Emergent hypocalcemia events within the first 12 weeks were assessed using inverse probability of treatment weighting.
Main Results:
- Denosumab use was associated with increased hypocalcemia risk compared to oral and IV bisphosphonates, particularly in advanced CKD stages.
- Dialysis-dependent (DD) patients showed the highest risk (3.01% vs. 0.00% for oral bisphosphonates).
- Patients with CKD stages 4-5 and CKD-MBD experienced a significantly higher risk with denosumab.
Conclusions:
- Denosumab treatment in osteoporosis patients with advanced CKD, especially those who are dialysis-dependent or have CKD-MBD, carries an elevated risk of emergent hypocalcemia.
- This finding highlights the need for careful patient selection and monitoring when using denosumab in this population.


Related Concept Videos
 01:17
Hormones and Bone Tissue
Hormones That Influence Osteoblasts and/or Maintain the Matrix
Several hormones are necessary for controlling bone growth and maintaining the bone matrix. The pituitary gland secretes growth hormone (GH), which, as its name implies, controls bone growth. This happens in several ways: first, it triggers chondrocyte...
 01:21
Skeleton and Calcium Homeostasis
 01:29
Bone Disorders
Bone deposition is also affected by the levels of sex hormones like estrogen and testosterone that promote osteoblast activity and bone matrix synthesis. When the level of these hormones decreases due to aging, it causes a reduction in bone deposition. As a result, bone resorption by osteoclasts...
 01:40
Bone Remodeling
 00:51
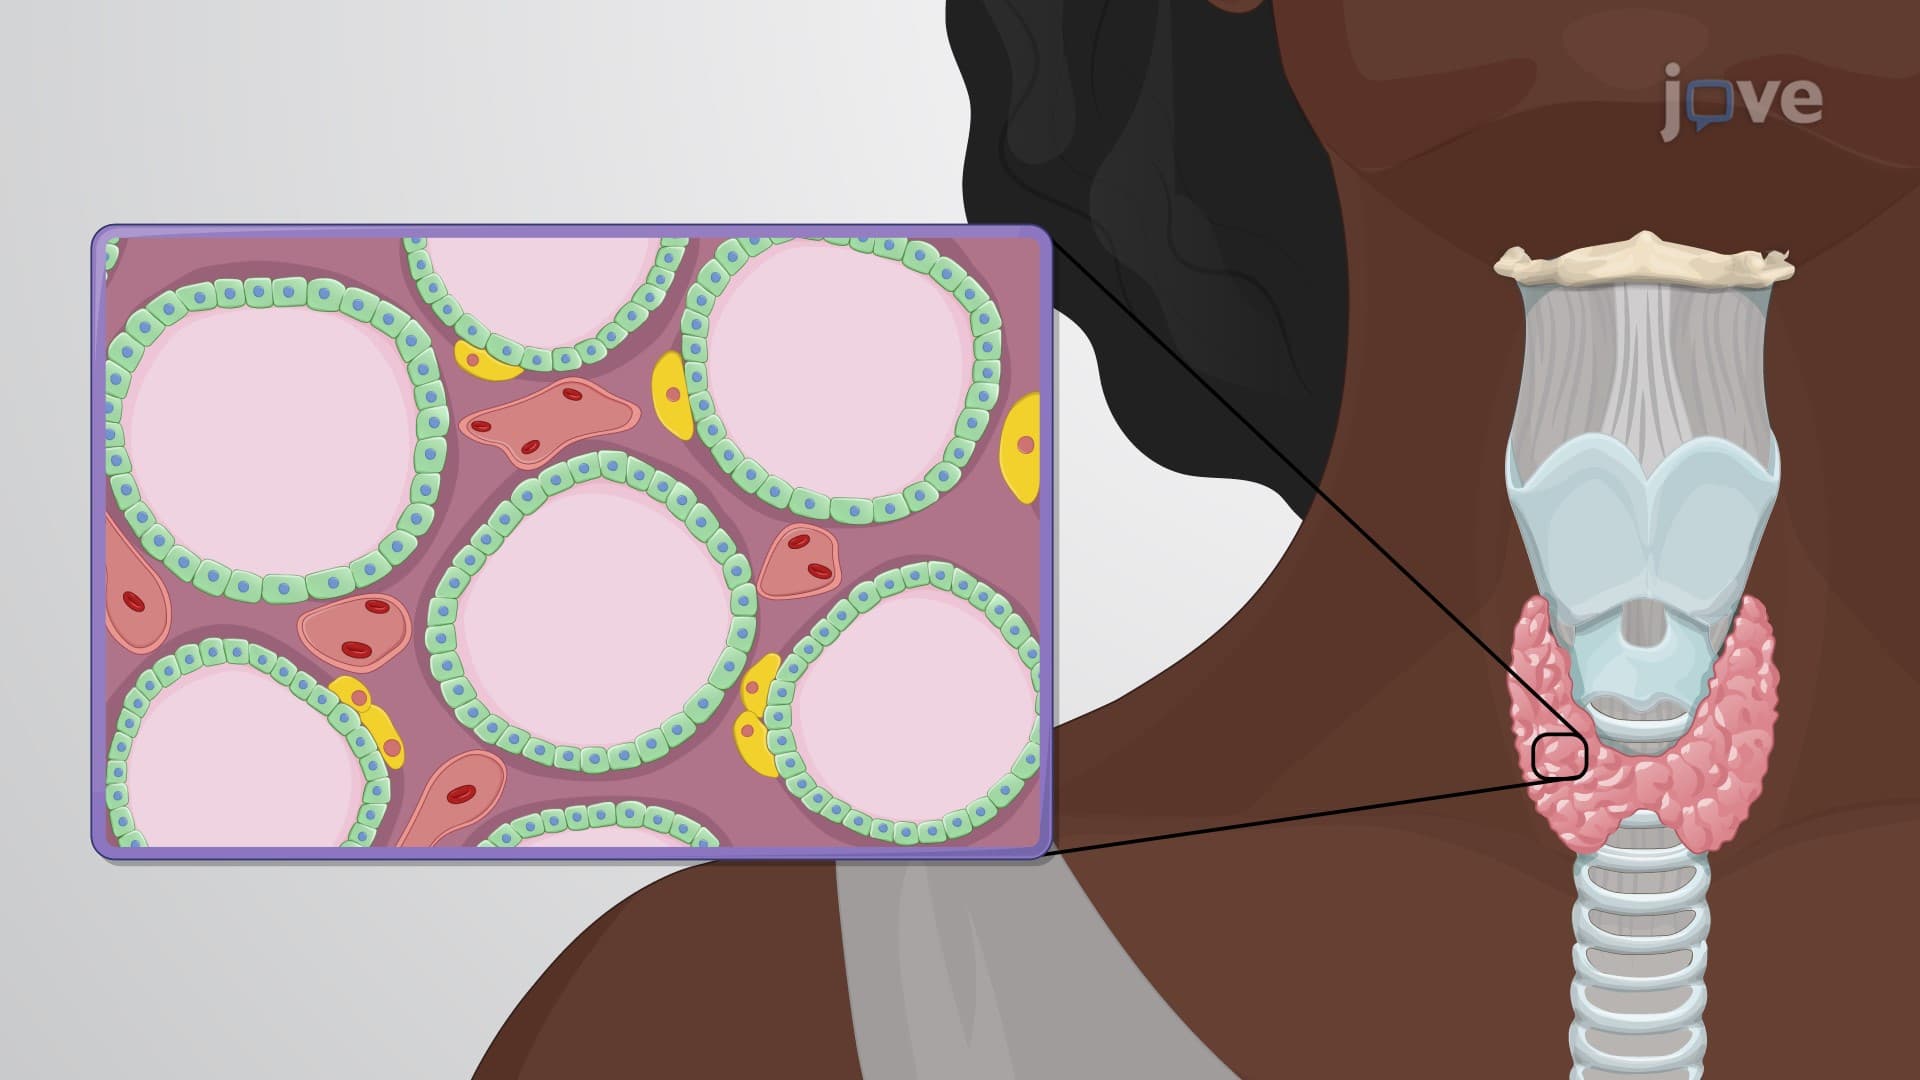
Synthesis and Functions of Calcitonin
The exact mechanisms by which calcitonin operates in calcium homeostasis remain elusive, but its significance is evident in several vital...
 01:25
Role of Vitamins in Maintaining Bone Health
Vitamin A
Vitamin A is involved in the process of bone remodeling. Retinoic acid, the active metabolite of Vitamin A, has nuclear receptors in osteoblasts and osteoclasts, which are involved in bone remodeling.
Vitamin B12
Vitamin B12 acts as a cofactor during the formation of osteoblast-related proteins, such as osteocalcin. Vitamin B12 plays a role...