Related Experiment Video
Updated: Jun 6, 2025


Quantitating Iron Transport Across the Mouse Placenta In Vivo Using Nonradioactive Iron Isotopes
Published on: May 10, 2022
Low-Dose Prophylactic Oral Iron Supplementation (Ferrous Fumarate, Ferrous Bisglycinate, and Ferrous Sulphate) in
Nils Thorm Milman1,2, Thomas Bergholt1,2
1Department of Obstetrics and Gynecology, Herlev and Gentofte University Hospital DK-2730, Herlev, Denmark.

Background: Many pregnant women are reluctant to follow the recommendation concerning oral iron prophylaxis due to concerns about gastrointestinal (GI) side effects. Objective: To assess the frequency of GI complaints during low-dose oral iron prophylaxis and compare three iron formulas in equipotent doses: ferrous fumarate versus ferrous bisglycinate versus ferrous sulphate, in healthy women with an uncomplicated single pregnancy. Methods: Results from two randomized, double-blind studies are reported: the Gentofte study comprising 404 women allocated into four groups taking 20, 40, 60, and 80 mg of elemental iron as ferrous fumarate/day and the Naestved study comprising 78 women allocated into two groups: 25 mg of elemental iron as ferrous bisglycinate/day and 50 mg of elemental iron as ferrous sulphate/day between meals from 15 to 19 weeks of gestation to delivery. GI complaints (nausea, vomiting, epigastric pain/pyrosis, belching, meteorism, borborygmi, intestinal colic, flatulence, loose stools, constipation, and use of laxatives), as well as black stools, were recorded by interview at the time of inclusion and at regular intervals during gestation. Results: At inclusion, the frequency of total combined GI complaints in all women (n = 482) was 21%. The Gentofte study showed that in the groups taking 20-60 mg iron/day as fumarate, there was no association between the iron dose and the frequency of GI side effects. An iron dose of 80 mg as fumarate was associated with significantly higher frequencies of constipation and the use of laxatives. Comparing the three equipotent doses of iron formulas, which can prevent iron deficiency, ferrous bisglycinate 25 mg iron had the most favourable GI side effect profile, while ferrous fumarate 40 mg iron and ferrous sulphate 50 mg iron had higher but similar GI side effect profiles. The frequency of black stools increased with the iron dose. Ferrous bisglycinate 25 mg iron had a lower frequency of black stools (8%) than ferrous fumarate 40 mg iron (22%) and ferrous sulphate 50 mg iron (31%). Conclusion: Low-dose iron supplementation appears to have no clinically significant GI side effects, as none of the included women presented with GI complaints of such severity that it necessitated either reduction of iron dose, change to an alternative iron formula, or discontinuation of iron supplement. However, ferrous bisglycinate 25 mg iron/day is associated with significantly fewer GI complaints than ferrous fumarate 40 mg iron/day and ferrous sulphate 50 mg iron/day. Ferrous bisglycinate may be preferred for iron prophylaxis, especially in women experiencing GI side effects when taking other conventional iron formulas.
Background: Many pregnant women are reluctant to follow the recommendation concerning oral iron prophylaxis due to concerns about gastrointestinal (GI) side effects. Objective: To assess the frequency of GI complaints during low-dose oral iron prophylaxis and compare three iron formulas in equipotent doses: ferrous fumarate versus ferrous bisglycinate versus ferrous sulphate, in healthy women with an uncomplicated single pregnancy. Methods: Results from two randomized, double-blind studies are reported: the Gentofte study comprising 404 women allocated into four groups taking 20, 40, 60, and 80 mg of elemental iron as ferrous fumarate/day and the Naestved study comprising 78 women allocated into two groups: 25 mg of elemental iron as ferrous bisglycinate/day and 50 mg of elemental iron as ferrous sulphate/day between meals from 15 to 19 weeks of gestation to delivery. GI complaints (nausea, vomiting, epigastric pain/pyrosis, belching, meteorism, borborygmi, intestinal colic, flatulence, loose stools, constipation, and use of laxatives), as well as black stools, were recorded by interview at the time of inclusion and at regular intervals during gestation. Results: At inclusion, the frequency of total combined GI complaints in all women (n = 482) was 21%. The Gentofte study showed that in the groups taking 20-60 mg iron/day as fumarate, there was no association between the iron dose and the frequency of GI side effects. An iron dose of 80 mg as fumarate was associated with significantly higher frequencies of constipation and the use of laxatives. Comparing the three equipotent doses of iron formulas, which can prevent iron deficiency, ferrous bisglycinate 25 mg iron had the most favourable GI side effect profile, while ferrous fumarate 40 mg iron and ferrous sulphate 50 mg iron had higher but similar GI side effect profiles. The frequency of black stools increased with the iron dose. Ferrous bisglycinate 25 mg iron had a lower frequency of black stools (8%) than ferrous fumarate 40 mg iron (22%) and ferrous sulphate 50 mg iron (31%). Conclusion: Low-dose iron supplementation appears to have no clinically significant GI side effects, as none of the included women presented with GI complaints of such severity that it necessitated either reduction of iron dose, change to an alternative iron formula, or discontinuation of iron supplement. However, ferrous bisglycinate 25 mg iron/day is associated with significantly fewer GI complaints than ferrous fumarate 40 mg iron/day and ferrous sulphate 50 mg iron/day. Ferrous bisglycinate may be preferred for iron prophylaxis, especially in women experiencing GI side effects when taking other conventional iron formulas.
Related Concept Videos
 01:21
Drugs for Treatment of Constipation-Predominant IBS
 01:25
Factors Influencing Drug Absorption: Disease States and Pharmacology
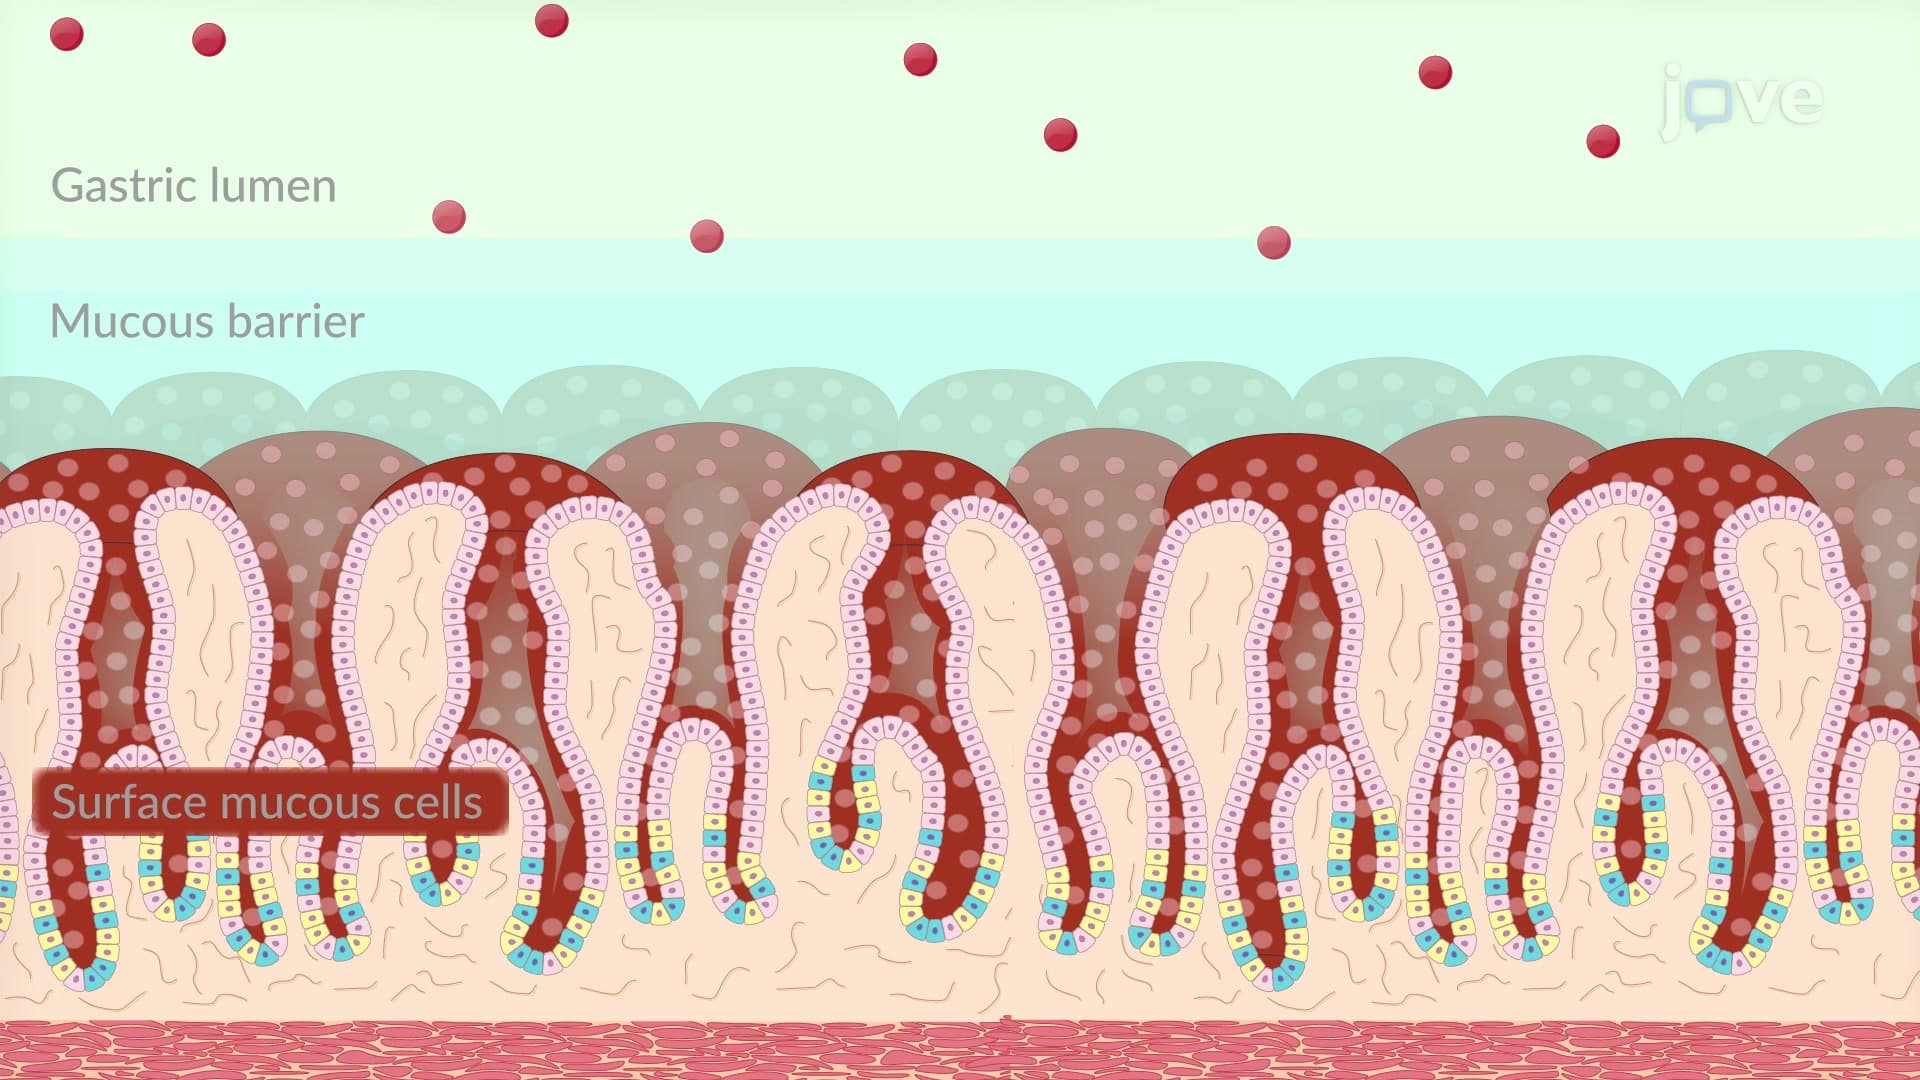
Substances such as alcohol and specific drugs, including antineoplastics, can also negatively impact drug absorption. For instance,...
 01:19
Drug Absorption: Factors Affecting GI Absorption
 01:30
Inflammatory Bowel Disease III: Diagnostic Studies and Management I-Nutritional Therapy
Diagnostic studies
A colonoscopy is the definitive screening test, distinguishing ulcerative colitis from other colon diseases with similar symptoms. During a colonoscopy test, inflamed mucosa with exudate ulcerations can be observed, and biopsies are taken to determine the histologic characteristics of the...
 01:21
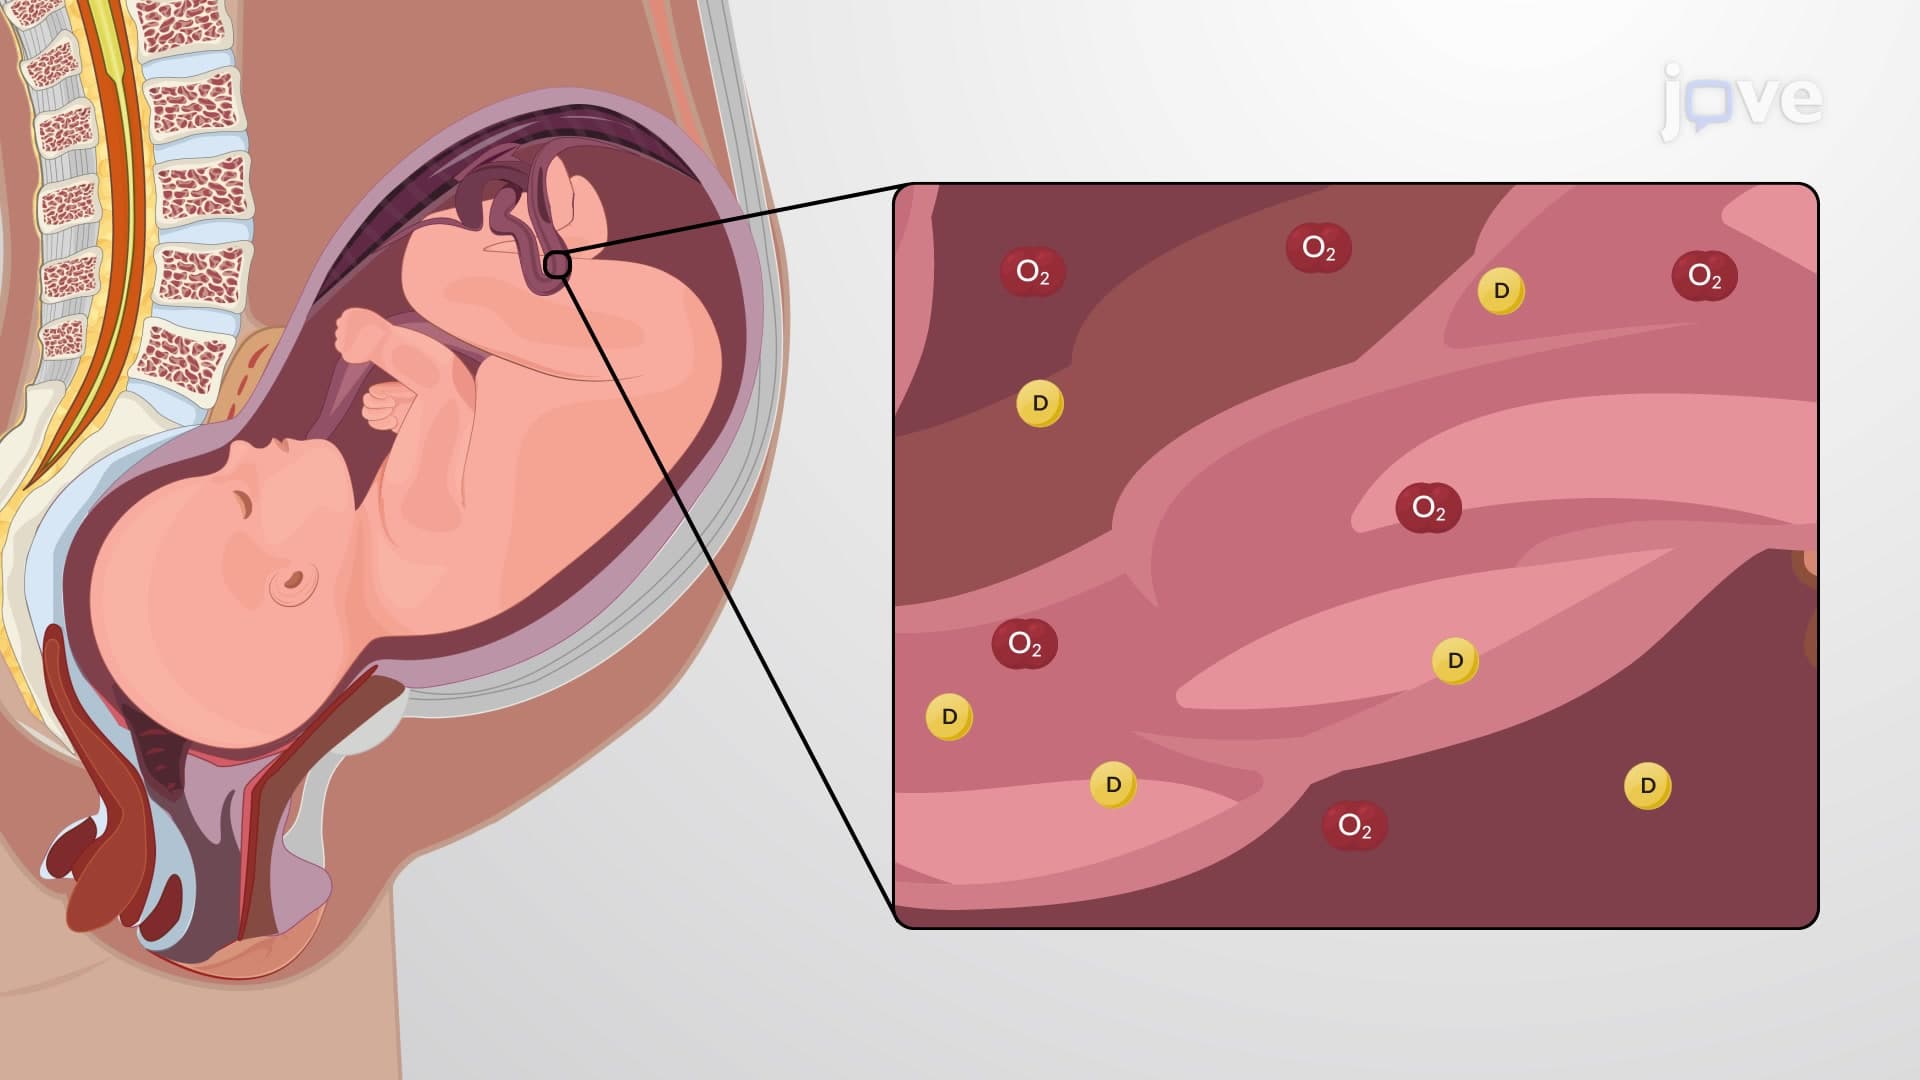
Factors Affecting Drug Response: Overview
 01:20
Drugs for Peptic Ulcer Disease: Prostaglandin Analogs as Mucosal Protective Agents
Non-steroidal anti-inflammatory drugs (NSAIDs) can induce peptic ulcers by inhibiting cyclooxygenase, decreasing...