Related Experiment Video
Updated: Jun 6, 2025


Halogenated Agent Delivery in Porcine Model of Acute Respiratory Distress Syndrome via an Intensive Care Unit Type Device
Published on: September 24, 2020
Chloride removal and bicarbonate replacement by isotonic sodium bicarbonate-based continuous hemodiafiltration: a
Yoshihiro Inoue1, Yayoi Tsuchihashi2, Hassu Kin2
1Department of Clinical Engineering, St. Luke's International Hospital, 9-1, Akashi-Cho, Chuo-Ku, Tokyo, 104-8560, Japan. yoshino@luke.ac.jp.

Background:
Previous reports highlighted the efficacy of hemofiltration utilizing isotonic sodium bicarbonate solution as replacement fluid for severe metabolic acidosis. This approach corrects metabolic acidosis by eliminating chloride and supplementing bicarbonate. Here, we present the results of an in vitro study aimed at determining the effect of Isotonic sodium bicarbonate-based Continuous HemoDiafiltration (IBB-CHDF).
Methods:
Conventional Continuous HemoDiaFiltration (CHDF) and IBB-CHDF utilized aqueous solutions mimicking blood's electrolyte composition. To assess the efficacy and safety, we compared serial changes in pH, HCO3-, Na+, and K+ concentrations. Blood flow rate was 100 mL/min, and the dialysis fluid flow rate maintained 1.0 L/h for both CHDF and IBB-CHDF. Replacement flow rates ranged from 0.5 to 1.5 L/h for CHDF and 0.1 to 1.5 L/h for IBB-CHDF.
Results:
At a replacement flow rate of 0.5 L/h with IBB-CHDF, bicarbonate increased from 14.7 mEq/L to within the physiological range (25.9 mEq/L), whereas in conventional CHDF, the post-treatment bicarbonate concentration did not increase (16.5 mEq/L). The maximum bicarbonate concentration achieved was 22.0 mEq/L at a replacement flow rate of 1.5 L/h in conventional CHDF. Notably, in IBB-CHDF, the sodium concentration remained constant at 150 mEq/L, 10 mEq/L higher than conventional CHDF, and did not escalate despite increasing the replacement flow rate.
Conclusion:
IBB-CHDF effectively corrects metabolic acidosis without inducing sodium and water overload by eliminating excess chloride while providing bicarbonate.
More Related Videos
 07:38
Functional Characterization of Na+/H+ Exchangers of Intracellular Compartments Using Proton-killing Selection to Express Them at the Plasma Membrane
Published on: March 30, 2015
 09:02
Percutaneous Hepatic Perfusion PHP with Melphalan as a Treatment for Unresectable Metastases Confined to the Liver
Published on: July 31, 2016
Related Concept Videos
 01:29
Roles of Electrolytes: Chloride and Bicarbonate
Conditions such as hypochloremia can arise from insufficient chloride reabsorption by the kidneys, often compounded by extended bouts of diarrhea, vomiting,...
 01:22
Bicarbonate-Carbonic Acid Buffer
 01:24
Diagnosing Acidosis and Alkalosis
First, the pH level is assessed to determine whether the blood pH is normal (7.35–7.45), low (acidosis), or high (alkalosis).
Next, the PCO2 and...
 01:29
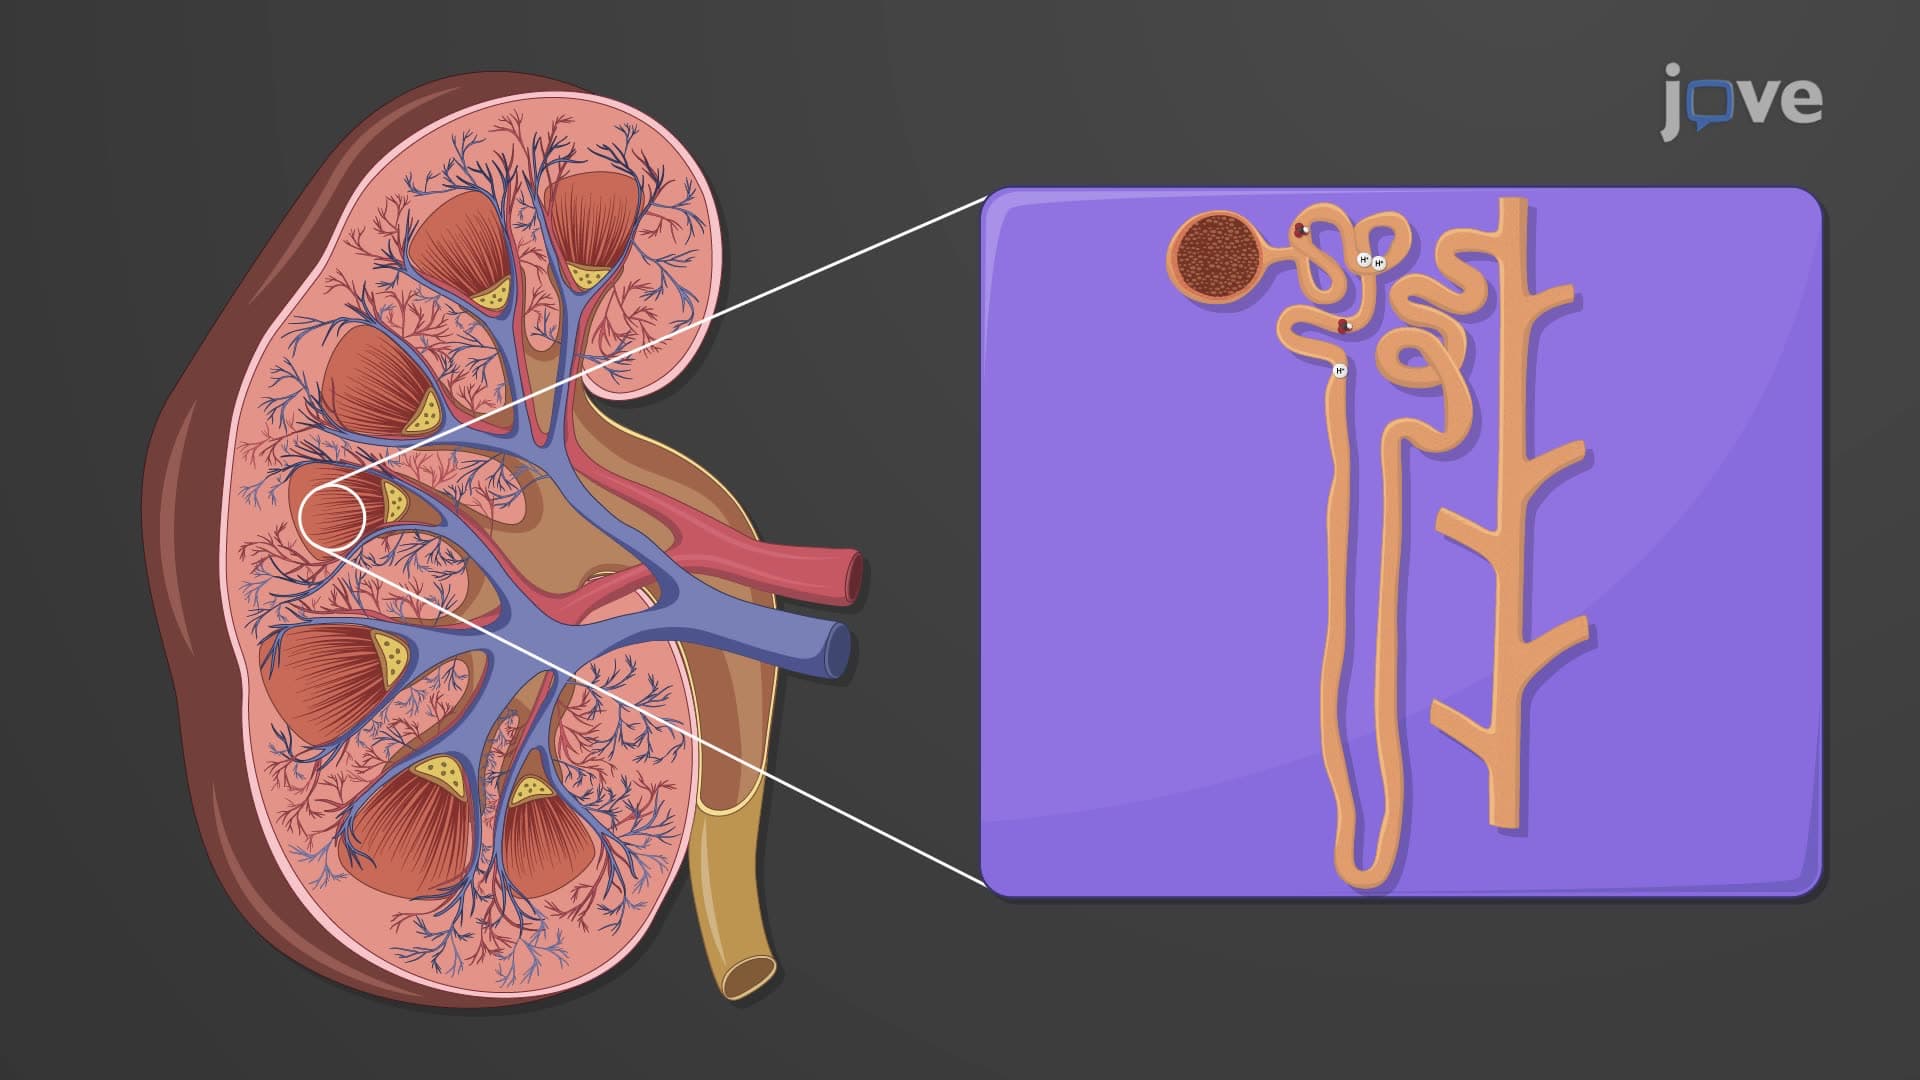
Renal Regulation of Acid-Base Balance
In the kidneys, cells within the proximal convoluted tubules (PCT) and the collecting ducts secrete hydrogen ions (H+) into the tubular fluid. Specifically, in the PCT, Na+/H+ antiporters secrete H+ while reabsorbing Na+.
However, the intercalated cells in...
 01:29
Disorders of Acid-Base Balance
Respiratory Acidosis and Alkalosis
Respiratory acidosis occurs due to an increase in the partial pressure of carbon dioxide PCO2 in the blood. It often arises from shallow breathing or impaired gas exchange caused by...
 01:28
Compensation Mechanisms
Respiratory Compensation
This mechanism addresses metabolic-induced pH imbalances by adjusting breathing rates. Respiratory compensation begins within minutes of detecting a pH...