Related Experiment Video
Updated: Jun 5, 2025


Catheter Ablation in Combination With Left Atrial Appendage Closure for Atrial Fibrillation
Published on: February 26, 2013
Risk of Bleeding, Thrombosis and Death among Atrial Fibrillation Patients Treated with Oral Anticoagulants Across
Xinhai Huang1, Donglin Xie1, Jie Huang1
1School of Pharmacy, Fujian Medical University, Fuzhou, China; Department of Pharmacy, Fujian Maternity and Child Health Hospital College of Clinical Medicine for Obstetrics & Gynecology and Pediatrics, Fujian Medical University, Fuzhou, China.

Insights
Patients with atrial fibrillation (AF) and reduced kidney function taking oral anticoagulants (OACs) face increased death risks. Lower estimated glomerular filtration rate (eGFR) correlates with higher mortality and bleeding events, though direct OACs show promise.
Area of Science:
- Nephrology and Cardiology
- Pharmacology and Therapeutics
- Epidemiology and Public Health
Background:
- Limited data exist on oral anticoagulant (OAC) clinical benefits and harms for stroke prevention in atrial fibrillation (AF) patients with chronic kidney disease (CKD).
- Nuanced stratification of estimated glomerular filtration rate (eGFR) using the CKD-EPI equation is crucial for understanding risks in AF patients with varying kidney function.
Purpose of the Study:
- To evaluate the clinical benefits and harms of OACs in AF patients with CKD, focusing on nuanced eGFR stratification.
- To compare risks of major bleeding, thrombosis, and all-cause death across different eGFR categories in AF patients treated with OACs.
Main Methods:
- Retrospective study involving 9,510 AF patients across 12 centers in China.
- Patients categorized into eGFR groups: ≥60, 45-59, 30-44, and <30 ml/min/1.73 m².
- Logistic regression analysis used to compare risks of bleeding, thrombosis, and death.
Main Results:
- AF patients with eGFR 45-59, 30-44, and <30 ml/min/1.73 m² had significantly increased all-cause death risk compared to eGFR ≥60 ml/min/1.73 m².
- Higher eGFR was associated with significantly lower risks of all-cause death and major bleeding.
- Direct OACs demonstrated a reduced risk of major bleeding in patients with eGFR 30-44 ml/min/1.73 m² compared to warfarin.
Conclusions:
- In AF patients on OACs, reduced eGFR (45-59, 30-44, <30 ml/min/1.73 m²) is linked to significantly higher all-cause mortality.
- The risk of all-cause death escalates with declining eGFR.
- Direct OACs represent safe alternatives to warfarin for AF patients with eGFR 30-44 ml/min/1.73 m².
Abstract:
There are limited data about the clinical benefits and harm of oral anticoagulants (OACs) for stroke prevention in patients with atrial fibrillation (AF) and chronic kidney disease using CKD-EPI (Chronic Kidney Disease Epidemiology Collaboration) creatinine equation for glomerular filtration rate (GFR) estimation in nuanced GFR stratification. We conducted a retrospective study in 12 centers in China and included 9,510 patients with AF. We grouped patients into the following estimated GFR (eGFR) categories: ≥60 (n = 7,616), 45 to 59 (n = 1,139), 30 to 44 (n = 474), and <30 (n = 281) ml/min/1.73 m2. Logistic regression was used to the compare risks of major bleeding, minor bleeding, total bleeding, thrombosis, and all-cause deaths in patients with AF with eGFR 45 to 59, 30 to 44, <30 ml/min/1.73 m2, and ≥60 ml/min/1.73 m2 after taking OACs. Patients with AF treated with OACs with eGFR 45 to 59, 30 to 44, and <30 ml/min/1.73 m2 had a significantly increased risk of all-cause deaths compared with eGFR ≥60 ml/min/1.73 m2 (adjusted odds ratio [aOR] 1.326, 95% confidence interval [CI] 1.049 to 1.665, p = 0.016; aOR 1.634, 95% CI 1.197 to 2.200, p = 0.002; aOR 2.492, 95% CI 1.766 to 3.471, p <0.001; respectively). Higher eGFR was associated with a significantly lower risk of all-cause deaths (aOR 0.990, 95% CI 0.986 to 0.994, p <0.001) and major bleeding (aOR 0.988, 95% CI 0.979 to 0.998, p = 0.018). Direct OACs remarkably reduced risk of major bleeding in those with eGFR 30 to 44 ml/min/1.73 m2 compared with warfarin. In conclusion, in patients with AF treated with OACs, patients with eGFR 45 to 59, 30 to 44, and <30 ml/min/1.73 m2 had a significantly increased risk of all-cause deaths compared with eGFR ≥60 ml/min/1.73 m2, and the risk of all-cause deaths increased with decreasing eGFR. Direct OACs are at least safe alternatives to warfarin in patients with AF with eGFR 30 to 44 ml/min/1.73 m2.


Related Concept Videos
 01:30
Anticoagulant Drugs: Low-Molecular-Weight Heparins
 01:18
Anticoagulant Drugs: Vitamin K Antagonists and Direct Oral Anticoagulants
Warfarin, a prominent vitamin K antagonist family member, exerts its effect by inhibiting the enzyme VKORC1 (vitamin K epoxide reductase complex 1). By hindering this enzyme, warfarin...
 01:11
Renal Failure: Dose Adjustments
Reduced renal clearance and elimination rate are common outcomes of renal impairment. These alterations lead to a prolonged elimination half-life and an altered apparent volume of distribution for drugs. As a result, dosage adjustments are typically necessary to maintain optimal drug levels in the body.
However, dosage adjustments...
 01:20
Antiplatelet Drugs: Prostaglandin Synthesis, P2Y12 and Glycoprotein IIb/IIIa Inhibitors
Prostaglandin synthesis inhibitors, exemplified by the widely known aspirin, wield their power by irreversibly acetylating...
 01:17
Factors Affecting Renal Clearance: Renal Impairment
One condition associated with renal failure is uremia. Uremia is characterized by impaired glomerular filtration and fluid accumulation in the body. This condition hinders the renal clearance of drugs, resulting in drug accumulation and potential...
 01:02
Renal Drug Excretion: Glomerular Filtration
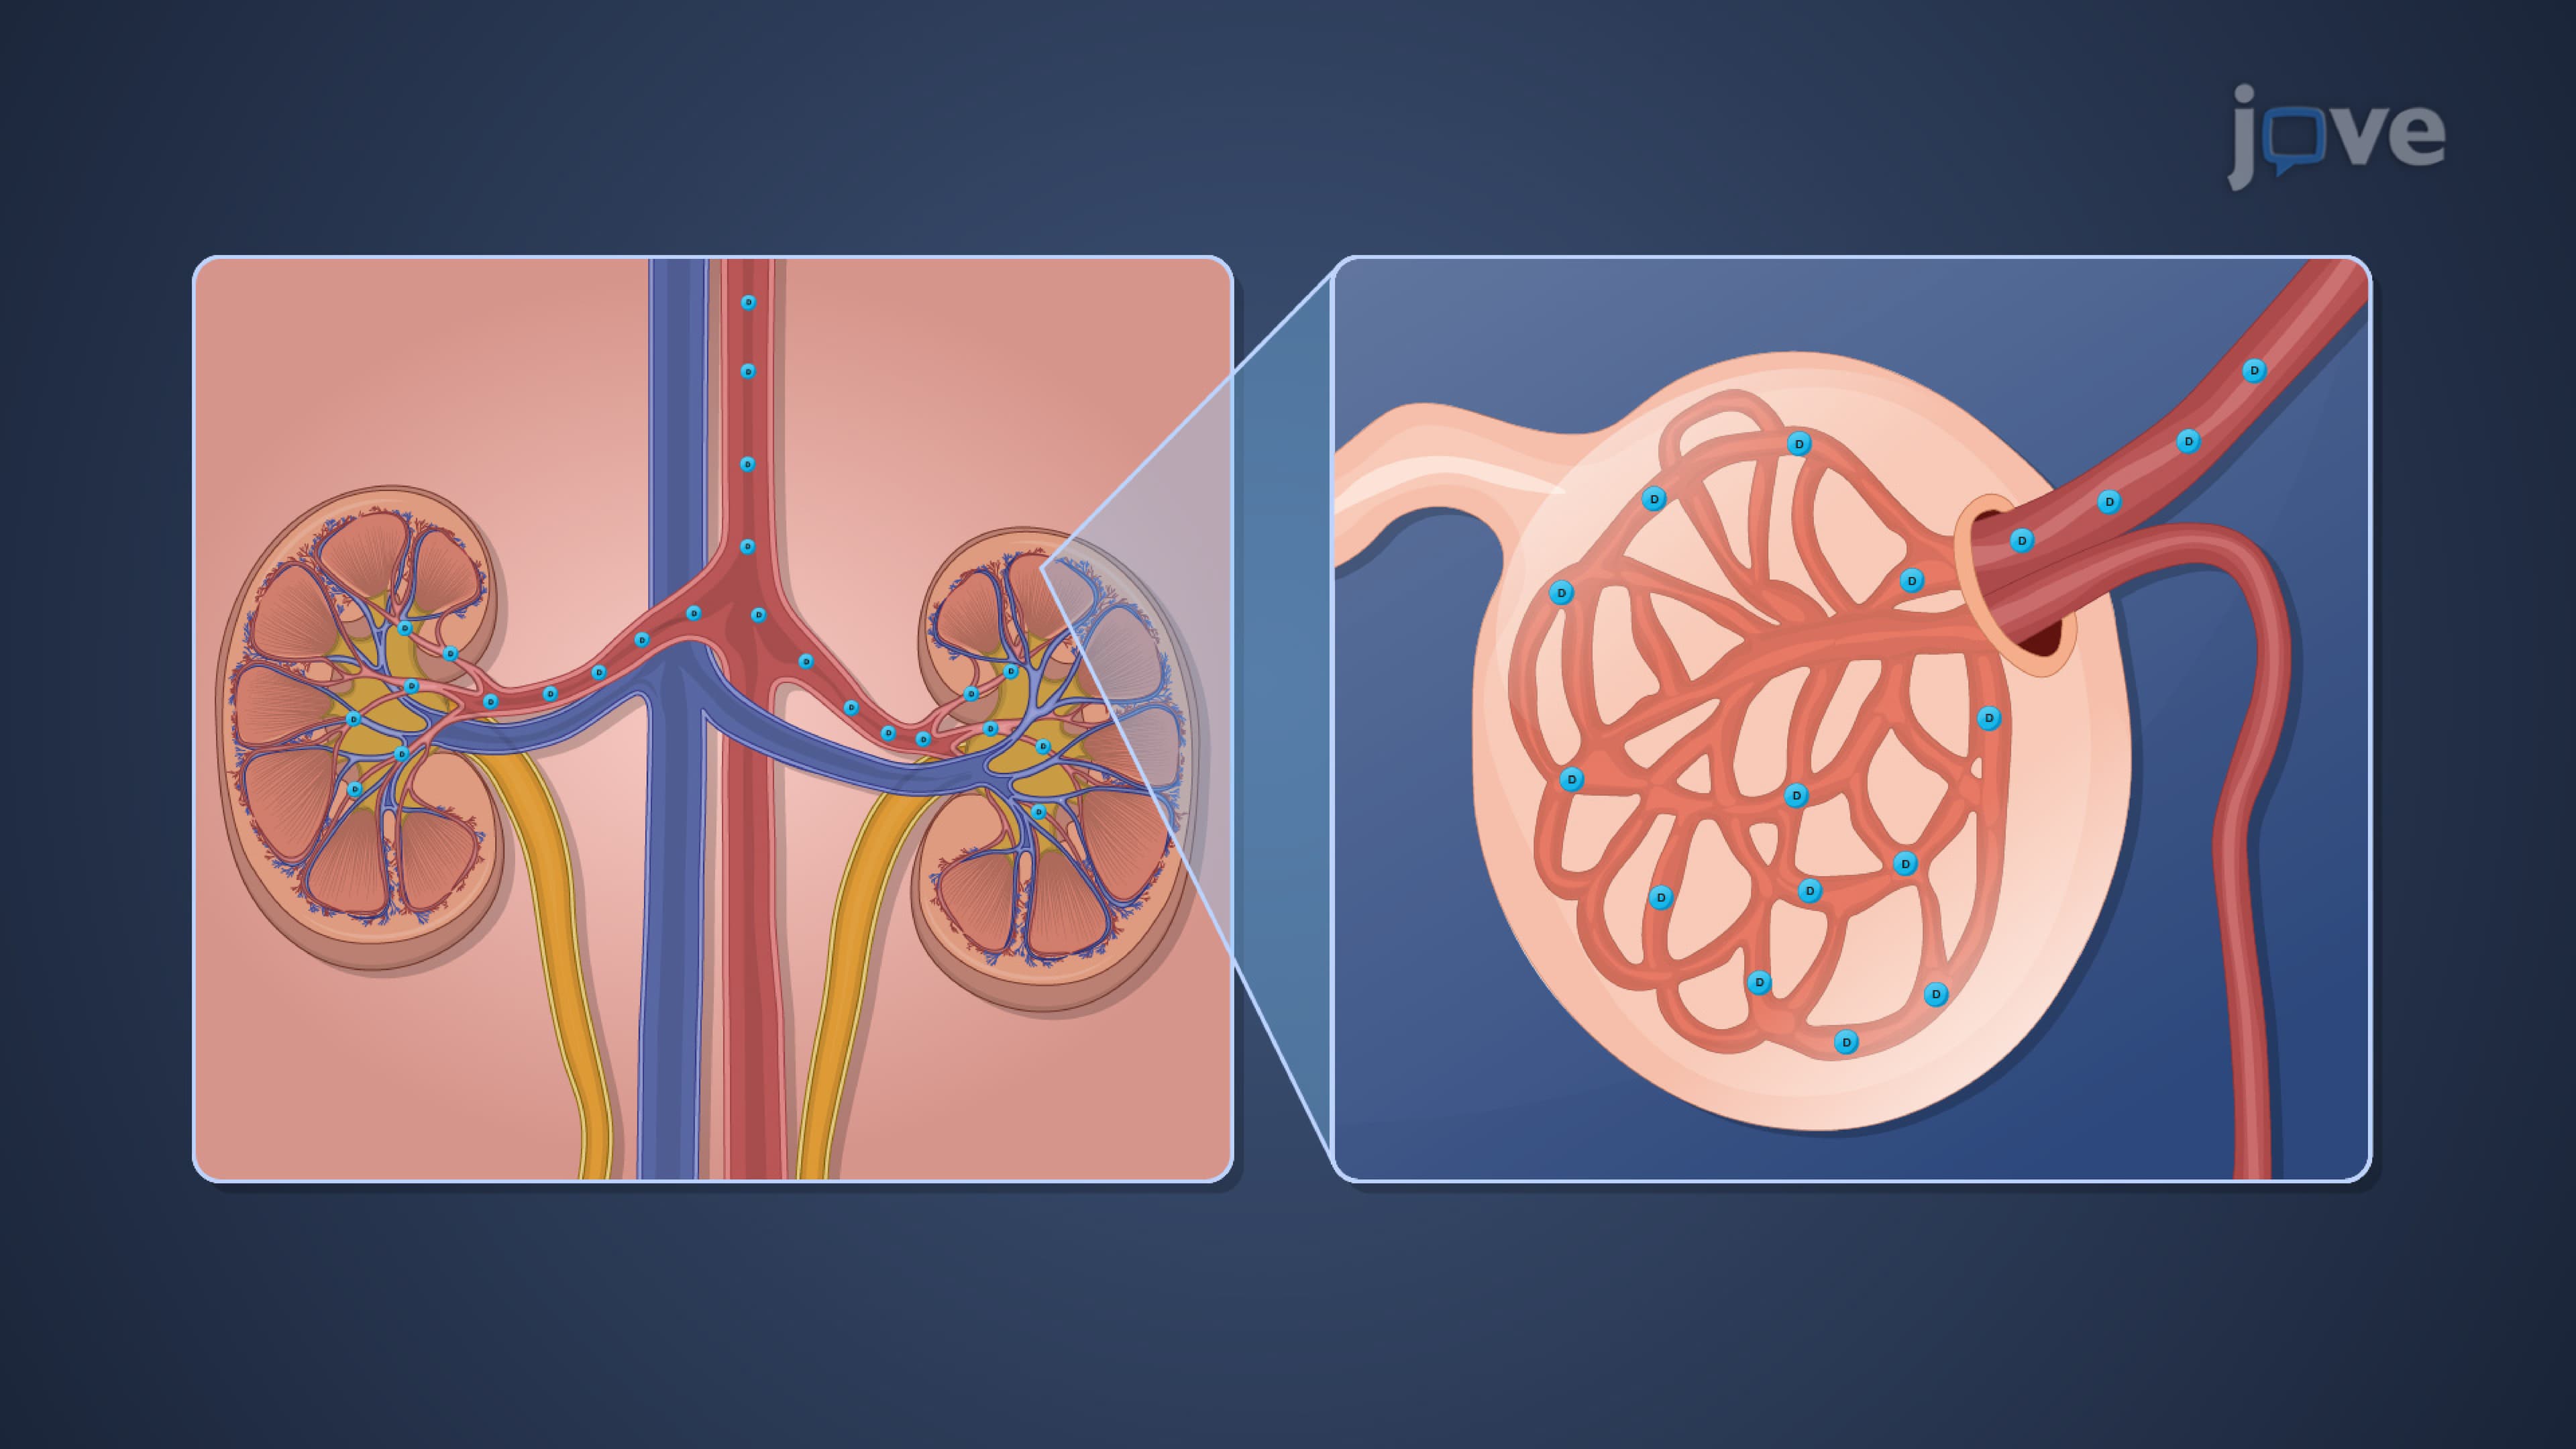
Drugs gain access to the kidney via the renal artery, which progressively branches off into afferent arterioles....