Related Experiment Video
Updated: Jun 5, 2025
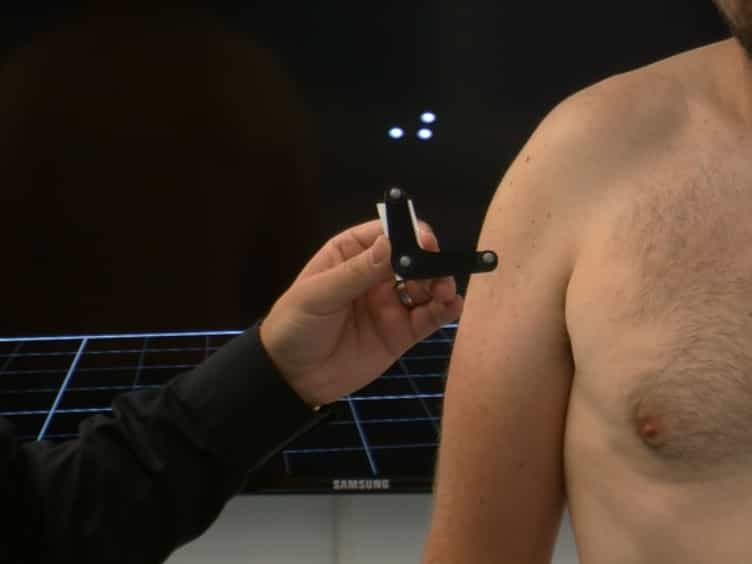

Measurement of Dynamic Scapular Kinematics Using an Acromion Marker Cluster to Minimize Skin Movement Artifact
Published on: February 10, 2015
Is the YES/NO classification accurate in screening scapular dyskinesis in asymptomatic individuals? - A novel
Lawrence S Ramiscal1, Lori A Bolgla1, Chad E Cook2
1Department of Physical Therapy, Augusta University, Augusta, GA, USA.

Background:
Scapular dyskinesis is a known risk factor for shoulder pain, making it important to screen for prevention. Physical therapists screen scapular dyskinesis by visually comparing asymmetries in scapular movement during overhead reach using the Scapular Dyskinesis Test Yes/No classification (Y/N). Although scapular kinematics has been used to quantify scapular dyskinesis, current measurement techniques are inaccurate. Optimal scapular muscle activity is crucial for normal shoulder function and is measured using surface electromyography (sEMG). Research suggests that impaired scapular muscles can lead to scapular dyskinesis. Despite kinematics being a poor reference standard, there is currently no validated method to identify movement asymmetries using muscle activity as an alternative. We utilized sEMG to establish Y/N's validity. We hypothesized that Y/N is a valid tool using sEMG as a viable surrogate measure for identifying scapular dyskinesis.
Methods:
We employed a known-groups (symmetrical vs. asymmetrical shoulders) validity design following the Standards for Reporting Diagnostic Accuracy Studies. Seventy-two asymptomatic subjects were evaluated using Y/N as the index test and sEMG as the reference standard. We created a criterion to assign the sEMG as the reference standard to establish the known groups. We calculated the sensitivity (Sn), specificity (Sp), positive and negative predictive values (PPV, NPV), likelihood ratios (LR+, LR-), and diagnostic odds ratio (DOR) using a 2 × 2 table analysis.
Results:
The diagnostic accuracy values were Sn = 0.56 (0.37-0.74), Sp = 0.36 (0.08-0.65), PPV = 0.68 (0.49-0.88), NPV = 0.25 (0.04-0.46), LR+ = 0.87 (0.50-1.53), and LR- = 1.22 (0.50-2.97).
Conclusion:
The Y/N's diagnostic accuracy was poor against the sEMG, suggesting clinicians should rely less on Y/N to screen scapular dyskinesis in the asymptomatic population. Our study demonstrated that sEMG might be a suitable alternative as a reference standard in validating methods designed to screen movement asymmetries.

