Related Experiment Video
Updated: Jun 4, 2025
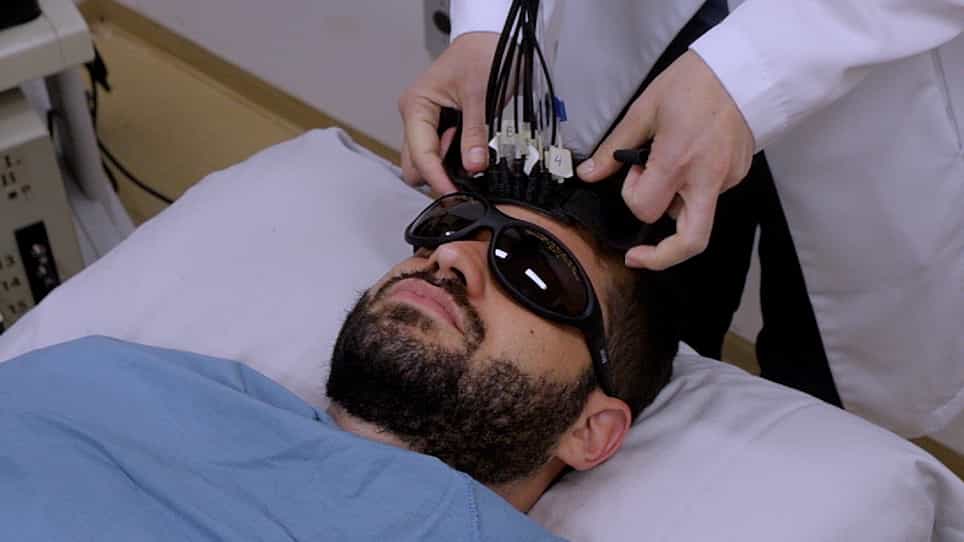

Real-Time Monitoring of Neurocritical Patients with Diffuse Optical Spectroscopies
Published on: November 19, 2020
Optimization of the cardiac delirium index by including age, decrease in butyrylcholinesterase actitivity,
Thomas S Zajonz1, Fabian Edinger1, Melanie Markmann1
1Department of Anaesthesiology, Operative Intensive Care Medicine and Pain Therapy, University Hospital of Giessen, Justus-Liebig University Giessen, Giessen, Germany.

Insights
Postoperative delirium (POD) risk after cardiac surgery is better predicted by the Cardiac Delirium (CARDEL) index when butyrylcholinesterase (BChE) activity is included. This optimized model improves early risk stratification for patients undergoing cardiac procedures.
Area of Science:
- Cardiology
- Neurology
- Biochemistry
Background:
- Postoperative delirium (POD) following cardiac surgery is a significant concern, impacting patient morbidity and mortality.
- Butyrylcholinesterase (BChE) plays a role in acetylcholine hydrolysis and may influence POD.
- The Cardiac Delirium (CARDEL) index is used to predict POD, but its predictive power may be enhanced.
Purpose of the Study:
- To evaluate the applicability of the CARDEL index for predicting POD after cardiac surgery.
- To determine if integrating BChE activity into the CARDEL index improves its predictive accuracy for POD.
Main Methods:
- A secondary analysis of a prospective observational study involving patients undergoing elective coronary artery bypass graft surgery.
- Multivariate regression analysis was used to identify POD risk factors, including BChE activity and HbA1c.
- Receiver operating characteristic (ROC) analysis was employed to compare the predictive power of the standard CARDEL index versus an optimized model including BChE.
Main Results:
- Of 93 patients, 21.5% developed POD.
- Independent risk factors for POD included elevated preoperative HbA1c, a decrease in BChE activity, and postoperative hemoglobin changes.
- The CARDEL index had moderate predictive power (AUCROC 0.74), which significantly improved when BChE activity was integrated (AUCROC 0.84, p < 0.001).
Conclusions:
- Elevated HbA1c and decreased BChE activity are key risk factors for POD after cardiac surgery.
- Integrating BChE activity into the CARDEL index significantly enhances its predictive capability for POD.
- This optimized model could improve early risk stratification and targeted interventions for high-risk patients.
Introduction:
Postoperative delirium (POD) after cardiac surgery significantly affects the perioperative morbidity and mortality. Butyrylcholinesterase (BChE) is an enzyme primarily produced in the liver, which plays a crucial role in the hydrolysis of acetylcholine outside of neuronal synapses, referred to as extraneuronal hydrolysis. The integration of BChE activity into the cardiac delirium (CARDEL) index might increase its predictive power for identifying POD after cardiac surgery. Therefore, the primary aim of this study was to assess the applicability of the CARDEL index and determine whether integrating the BChE activity enables optimization of the predictive model.
Methods:
This secondary analysis of a prospective observational study included patients undergoing elective coronary artery bypass graft surgery. BChE activity is expressed in units per liter (U/L), while the BChE drop refers to the percentage decrease in BChE activity from pre- to postoperative levels. POD risk factors were identified using multivariate regression analysis. The predictive power of the CARDEL index and an optimized model including BChE was calculated with receiver operating characteristic (ROC) analysis.
Results:
Of 93 included patients, 20 (21.5%) developed POD. Elevated preoperative HbA1c [OR 2.5 (1.2-4.8), p = 0.01], a decrease in BChE activity [%, OR 1.1 (1.0-1.2), p = 0.04], age [1 (0.94-1.1), p = 0.55], and a postoperative hemoglobin change [OR 0.86 (0.78-0.96), p < 0.001] were identified as independent risk factors for POD. While the CARDEL index showed a moderate prediction of POD [AUCROC of 0.74 (0.60-0.87)], the optimization including BChE resulted in a significant prognostic improvement: AUCROC of 0.84 (0.72-0.94, p < 0.001).
Conclusion:
Despite the small size of this derivation cohort, this study identified elevated HbA1c as the strongest risk factor for the development of POD, followed by a decrease in BChE activity, postoperative anemia, and age, respectively. By including these parameters to the CARDEL index, its predictive power for the identification of POD significantly improved in this derivation cohort. Moving forward, integrating these findings into clinical practice could enhance early risk stratification and targeted intervention for patients at high risk of POD. Therefore, further research should evaluate these results in a larger, external cohort.

