Related Experiment Video
Updated: Jun 3, 2025

Novel Triple-Loop Technique for Suturing TFCC Injuries without Transosseous Tunnel
Published on: May 23, 2025
Pediatric Scaphoid Nonunions: Does Insurance Status Play a Role?
James S Lin1, James MacDonald2, Julie Balch Samora3
1Sterling Ridge Orthopaedics and Sports Medicine, The Woodlands, TX.

Insights
Insurance status did not impact treatment access or outcomes for pediatric scaphoid nonunions. This study found no significant differences in care timelines or surgical results between privately insured and underinsured children.
Area of Science:
- Pediatric Orthopedic Surgery and Hand Trauma.
- Health Services Research focusing on pediatric scaphoid nonunions and socioeconomic disparities.
- Clinical Outcomes Assessment in musculoskeletal healthcare delivery.
Background:
Scaphoid fractures represent a significant portion of carpal injuries in the adolescent population, often requiring specialized surgical intervention when healing fails. Prior research has shown that socioeconomic factors frequently influence the timeliness of medical consultation and the quality of surgical results in various orthopedic conditions. Disparities in healthcare access often stem from differences in coverage, potentially delaying the diagnosis of carpal fractures until they progress to a nonunion state. While adult populations show clear correlations between financial resources and recovery timelines, the pediatric demographic remains less characterized in this specific context. The complexity of managing a failed bone union in a growing skeleton necessitates an understanding of all external variables that might hinder recovery. Clinicians must identify whether systemic barriers prevent children from receiving timely specialized hand surgery. This absence of evidence motivated a focused investigation into how financial coverage affects the clinical pathway for children with carpal complications.
Purpose Of The Study:
This investigation sought to determine if financial coverage correlates with the duration of diagnostic delays and subsequent surgical success in young patients. Researchers examined the interval between the initial traumatic event and the first consultation with a specialized hand surgeon to identify potential barriers to entry. The analysis extended to the time elapsed from the first specialist visit to the actual operative procedure to assess institutional efficiency across different payer groups. Investigators also scrutinized postoperative metrics, including bone healing rates and functional recovery, to ensure clinical equity. By comparing privately insured individuals with those underinsured or on Medicaid, the study aimed to highlight any systemic biases in a tertiary care setting. The study specifically looked at whether underinsured status led to longer wait times or inferior physical outcomes like reduced grip strength. This comprehensive evaluation provides a baseline for understanding how socioeconomic status interacts with specialized pediatric trauma care.
Main Methods:
A retrospective cohort study, classified as Level III evidence, was conducted through a detailed chart review of patients treated at a large tertiary care pediatric hospital. The study period spanned from January 2015 to April 2021, capturing all individuals who underwent surgical repair for a scaphoid fracture nonunion. Participants were categorized into two distinct cohorts: those with private medical insurance and those classified as underinsured, which included Medicaid or state-funded programs. The research team extracted specific data points regarding the chronology of care, starting from the date of injury through the final postoperative follow-up. Clinical outcomes were measured by assessing radiographic union, residual pain levels, and objective metrics such as range of motion and grip strength. Researchers compared 21 privately insured patients against 17 underinsured patients to detect differences in age, race, or fracture characteristics. Statistical significance was determined using P-values to compare the two insurance groups across all temporal and functional variables.
Main Results:
Statistical analysis revealed no significant difference in the time from injury to specialist evaluation between the privately insured group and the underinsured cohort. The mean duration for private insurance holders was 192 days with a standard deviation of 195, while the underinsured group averaged 155 days with a standard deviation of 205, yielding a non-significant P-value of 0.57. Similarly, the interval from specialist consultation to surgical intervention showed no disparity, with means of 35 days and 31 days respectively (P = 0.82). Primary surgery resulted in successful bone union for 80% of privately insured patients and 88% of those with state-funded coverage (P = 0.67). Functional outcomes remained consistent across groups, as residual pain affected 15% of private payers compared to 19% of underinsured individuals (P = 1.00). Range of motion deficits were observed in 38% of the private group and 40% of the underinsured group, while strength deficits were limited to 6% and 7% respectively. Return to activity rates exceeded 93% for all participants, confirming that insurance status did not dictate functional recovery.
Conclusions:
The findings suggest that insurance status does not adversely affect the timeline of care or the clinical success of scaphoid nonunion surgery at a major pediatric institution. These results indicate that the internal protocols for managing complex carpal injuries may effectively mitigate potential socioeconomic barriers to specialized treatment. However, the authors caution that these observations are specific to a single tertiary center and may not represent the broader healthcare landscape. Future research should investigate whether similar equity exists for primary scaphoid fractures before they progress to the nonunion stage. Understanding the factors that lead to the initial development of a nonunion remains a priority for improving pediatric hand trauma outcomes. The study underscores the importance of institutional commitment to providing high-quality orthopedic care regardless of a patient's financial background. Clinicians should continue to monitor access patterns to ensure that all pediatric patients receive timely interventions for carpal fractures.
Objective:
There are no studies that evaluate the effects that insurance or socioeconomic status may have on treatment and outcomes of scaphoid nonunions in children. We evaluated whether there is an association between insurance status and (1) time from injury to hand surgeon evaluation, (2) time from specialist evaluation to surgery, and (3) postoperative outcomes of scaphoid fracture nonunions in children.
Methods:
A chart review was performed for patients who underwent surgical treatment of scaphoid fracture nonunion from January 2015 and April 2021 at a large tertiary care pediatric hospital. Underinsured patients were defined as those with no medical insurance or Medicaid/state-funded insurance.
Results:
There were 21 privately insured patients and 17 patients who were underinsured. There was no difference in age, race, or fracture characteristics between the two groups. The mean time between injury and hand surgeon evaluation was 192 SD 195 days for the privately insured group compared with 155 SD 205 days for the underinsured group (P = 0.57). The mean time between specialist evaluation and surgical treatment was 35 SD 54 days for the privately insured group and 31 SD 31 days for the underinsured group (P = 0.82). Union was achieved in 80% of patients with private insurance compared with 88% of underinsured patients after primary surgery (P = 0.67). There was no difference detected in the proportion of patients who had residual pain (15% vs 19%), range of motion deficits (38% vs 40%), strength deficit (6% vs 7%), and return to activity (94% vs 93%) between privately insured and underinsured patients, respectively (P = 1.00).
Conclusions:
There was no difference in time from injury to specialist evaluation, time from evaluation to surgery, or postoperative outcomes based on insurance status for pediatric patients with scaphoid fracture nonunions. Although insurance status was not associated with access to care for pediatric scaphoid fracture nonunions at our institution, this information may not be generalizable to other populations, including patients who sustain primary scaphoid fractures and who have not yet developed nonunions.
Level Of Evidence:
Level III-retrospective cohort study.
Frequently Asked Questions
Based on this study's findings, insurance status does not significantly delay specialist evaluation, with underinsured patients reaching a hand surgeon in 155 days compared to 192 days for privately insured patients (P = 0.57).
The researchers found that 80% of patients with private insurance achieved successful bone union, while 88% of underinsured patients reached the same outcome, showing no statistically significant difference (P = 0.67).
This methodology allowed the authors to evaluate 38 specific cases at a large tertiary care pediatric hospital to compare postoperative outcomes like range of motion deficits, which occurred in 38% of private and 40% of underinsured patients.
The study's authors note that these results may not apply to patients who sustain primary scaphoid fractures and have not yet developed nonunions, nor to populations outside this specific tertiary care institution.
The study's authors propose that while insurance status was not associated with access to care at their institution, further investigation is needed to determine if financial factors influence the initial development of a nonunion from a primary fracture.
Related Concept Videos
 01:27
Fractures: Bone Repair
Minor fractures with no bone displacement are treated by immobilizing the fractured bone using a cast or splint. However, in the case of fractures with displaced bones, the broken bones are repositioned before immobilization to ensure successful healing without deformation and loss of function. The realignment of fractured bone ends is performed through a process called reduction. If the...
 01:09
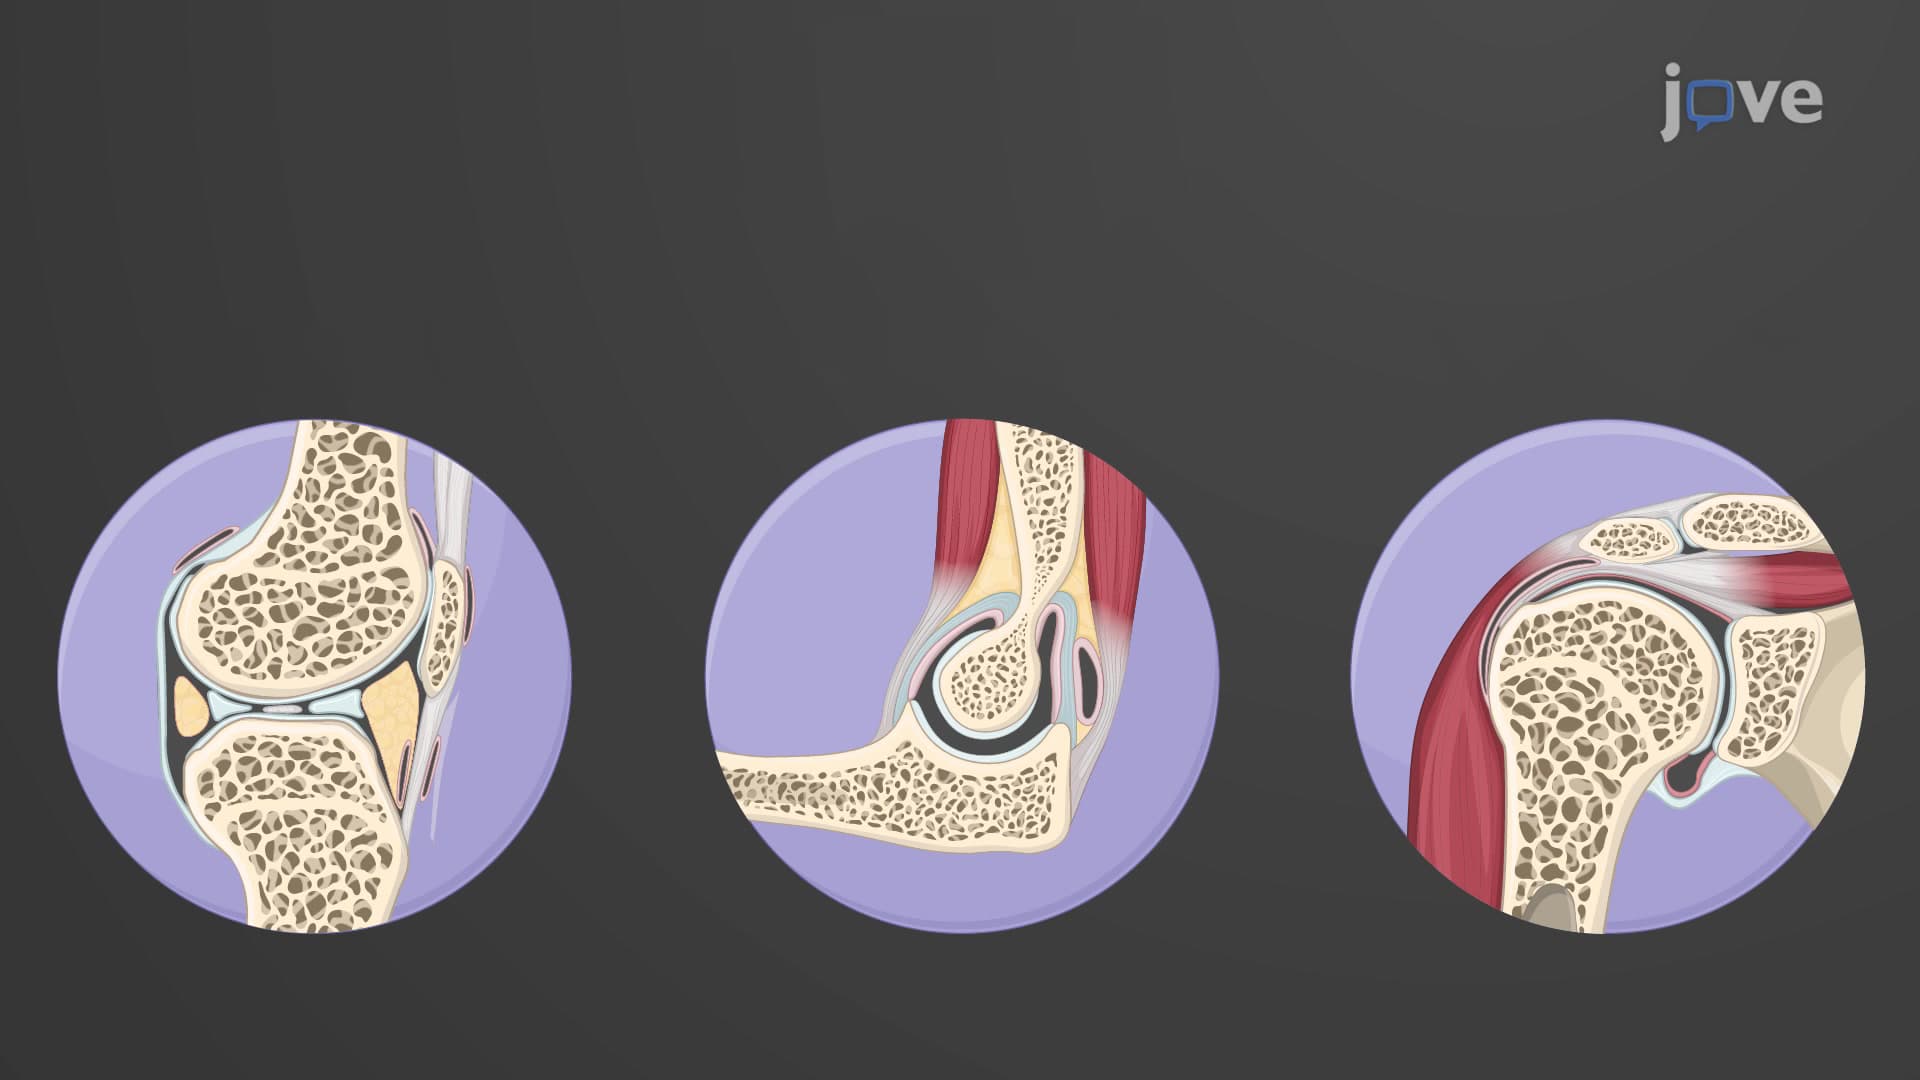
Functional Classification of Joints
The functional classification of joints is determined by the amount of mobility between the adjacent bones. Joints are functionally classified as a synarthrosis or immobile joint, an amphiarthrosis or slightly moveable joint, or as a diarthrosis, a freely moveable joint. Fibrous and cartilaginous joints can be functionally classified as either synarthroses or amphiarthroses, whereas all synovial joints are classified as diarthroses.
Synarthrosis
An...