

Left Bundle Branch Area Pacing Versus Right Ventricular Pacing in Patients With Atrioventricular Block: A Systematic
Irfan Ahsan1, Hussam Al Hennawi2, Angad Bedi2
1Division of Cardiology, Thomas Jefferson University Hospital, Philadelphia, Pennsylvania, USA.

Background:
Left bundle branch area pacing (LBBAP) is a new technique for patients with atrioventricular block (AVB) and preserved left ventricular ejection fraction (LVEF), potentially offering better cardiac function than right ventricular pacing (RVP).
Methods:
We searched databases and registries for studies that compared LBBAP with RVP in patients with AVB and preserved LVEF. We extracted data on various outcomes and pooled the effect estimates using random-effects models.
Results:
Our meta-analysis included 14 studies (10 observational and 4 RCTs) involving 3062 patients with AVB. The analysis revealed that the QRS duration was significantly shorter in the LBBAP group compared to the RVP group [MD = -35.56 ms; 95% CI: (-39.27, -31.85), p < 0.00001]. Patients in the LBBAP group also exhibited a significant increase in left ventricular ejection fraction (LVEF) [MD = 5.48%; 95% CI: (4.07%, 6.89%), p < 0.00001], and a significant reduction in left ventricular end-diastolic diameter (LVEDD) compared to RVP [MD = -3.98 mm; 95% CI: (-5.88, -2.09 mm), p < 0.0001]. In terms of clinical outcomes, LBBAP was associated with a significantly lower risk of heart failure hospitalizations (HFHs) compared to RVP [OR = 0.26; 95% CI: (0.16, 0.44), p < 0.0001]. However, no significant differences were observed between the two groups in the implant success rate, pacing impedance, or pacing threshold. The RVP group demonstrated a significantly higher R-wave amplitude increase than the LBBAP group [MD = 0.85 mV; 95% CI: (0.23, 1.46), p = .007]. Lastly, there was no significant difference in the incidence of complications between the two groups [OR = 2.12; 95% CI: (0.29, 15.52), p = 0.46].
Conclusion:
LBBAP outperforms RVP in several cardiac function indicators, suggesting it may be a superior pacing method for AVB patients with preserved LVEF. However, the small sample size in studies and the result in heterogeneity call for more research to validate these findings and assess LBBAP's long-term effects.


Related Concept Videos
 01:28
Disturbances in Heart Rhythm
Arrhythmias are categorized by their speed, rhythm, and origin. A slow...
 01:19
Conduction System of the Heart
The pacemaker cells are located in two primary nodes: the sinoatrial (SA) node and the atrioventricular (AV) node. The SA node pacemaker cells can autonomously depolarize, triggering an action potential that leads to the...
 01:20
Antiarrhythmic Drugs: Class IV Agents as Calcium Channel Blockers
Verapamil, a calcium channel blocker, inhibits calcium movement across myocardial cell membranes and vascular smooth muscle. This results in the dilation of coronary and...
 01:24
Antiarrhythmic Drugs: Class II Agents as β-Adrenergic Blockers
 01:19
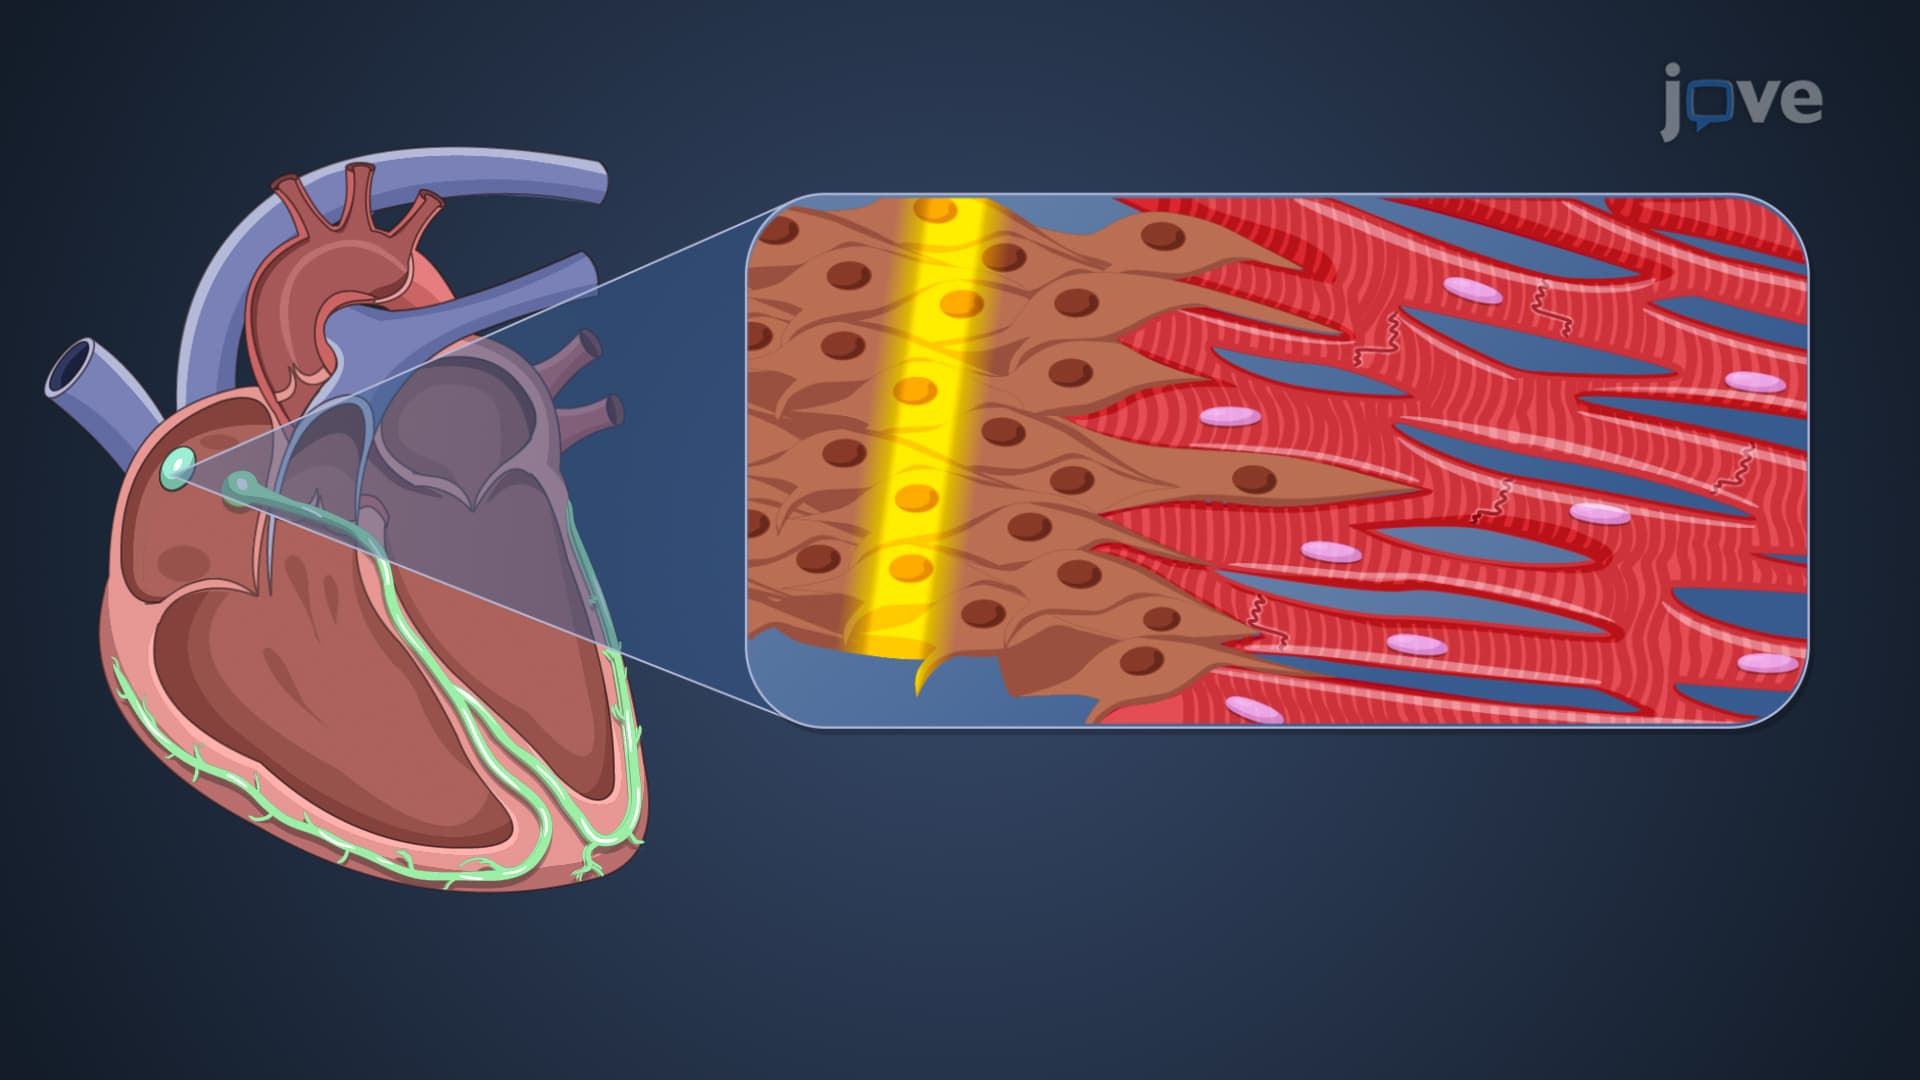
Electrophysiology of Normal Cardiac Rhythm
 01:13
The Cardiac Cycle
The Process
Electrical signals—sent from the sinoatrial (SA) node in the right atrial wall to the atrioventricular (AV) node between the right atrium and right ventricle—cause both atria to simultaneously contract. When the signal reaches the AV node, it pauses for approximately a tenth of a second, allowing the atria to contract and...