Related Experiment Video
Updated: Jul 28, 2026
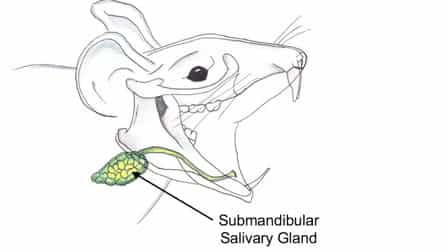

Cannulation of the Mouse Submandibular Salivary Gland via the Wharton's Duct
Published on: May 14, 2011
Large recurrent sialoliths in a residual Wharton duct after sialoadenectomy: Two case reports and literature review
Li-Wen Su1, Huan Sun2, Hong-Yu Zhang1
1Department of Oral and Maxillofacial Surgery.

Rationale:
When gland-preserving treatments are unsuccessful, sialoadenectomy is typically conducted for patients afflicted with submandibular gland diseases. The definitive treatment modality for these individuals is the removal of both the gland and the associated ducts. During surgery, the gland and the majority of the ducts can be excised utilizing the lateral transcervical approach, with residual ducts unlikely to develop pathology. After sialoadenectomy, the recurrence of salivary gland stones is extremely rare. Although there are some relevant speculations, to the best of our knowledge, there are no comprehensive reports of larger recurrent stone-related cases available.
Patient Concerns:
We present 2 instances of recurrent sialoliths in the residual Wharton duct following sialoadenectomy. In our cases, it was not until several years later that both patients presented with symptoms. The patients, a 51-year-old male and a 28-year-old female, presented with swelling and purulent discharge in the right floor of the mouth.
Diagnoses:
Computed tomography scans revealed irregular high-density masses in the floor of the mouth, indicative of sialolithiasis.
Interventions:
The intraoral incision exposed the recurrent sialoliths, which were successfully removed along with the residual duct.
Outcomes:
There were no complications in both cases.
Lessons:
This report aims to clarify potential mechanisms behind recurrent sialoliths in residual Wharton ducts after submandibular gland excision, warranting further investigation to improve patient management. New stones may form again in the residual duct even if the glands were removed. With the risk of recurrent sialoliths after resection of the gland, multiway preventive management can optimize outcomes.
Related Concept Videos
 01:15
Aortic Regurgitation I: Introduction
 01:22
Aortic Regurgitation II: Clinical Features and Diagnostic Tests
 01:26
Aneurysm III: Interprofessional Care
 01:26
Varicose Veins II: Diagnostic Studies and Interprofessional Care
 01:20
Venous Thrombosis II: Clinical Manifestations and Diagnostic Studies