Related Experiment Video
Updated: May 31, 2025
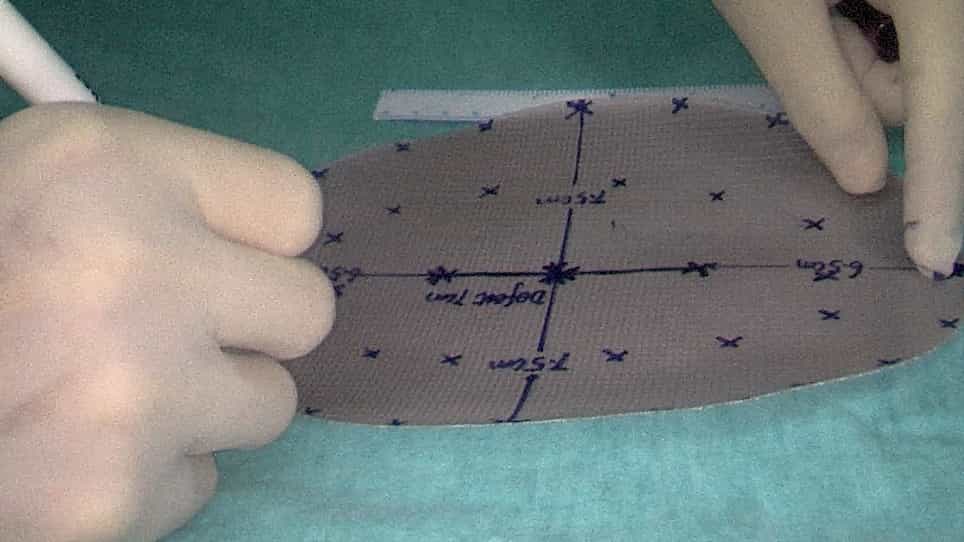
Application of a New Mesh Fixation Method in Laparoscopic Incisional Hernia Repair
Published on: December 23, 2022
Management and outcome of mesh infection after abdominal wall reconstruction in a tertiary care center
Victor Franchi1, Claire Triffault-Fillit2, Sophie Jarraud3,4
1Department of Infectious Diseases, Hospices Civils de Lyon, Service des Maladies Infectieuses et Tropicales, 103 Grande Rue de la Croix-Rousse, Lyon, 69004, France.

Purpose:
Abdominal wall reconstruction is a common surgical procedure, with a post-operative risk of mesh-associated infection of which management is poorly known. This study aims to comprehensively analyze clinical and microbiological aspects of mesh infection, treatment modalities, and associated outcomes.
Methods:
Patients with abdominal mesh infection were included in a retrospective observational cohort (2010-2023). Patients characteristics and management were described, and determinants for failure were assessed by logistic regression and treatment failure-free survival curve analysis (Kaplan-Meier).
Results:
Two hundred and nine patients (median age, 62 [IQR, 55-71] years) presented a mesh infection occurring within 15 (IQR, 7-31) days after surgery, mainly as an abdominal wall or deep abscess (n=189, 90.4%). Infection was polymicrobial in 89/166 (79.4%) cases, S. aureus (n=60, 36.1%), Enterobacteriaceae (n=60, 36.1%) and anaerobes (n=40, 24.1%) being the most prevalent pathogens. Surgery was performed in 130 (62.2%) patients, associated with a 13.5 (IQR, 8-21) day course of antimicrobial therapy in 172/207 (83.1%) cases. Sixty-three (30.1%) treatment failures occurred, associated with previous multiple abdominal surgeries (OR, 3.305; 95%CI, 1.297-8.425), complete mesh removal (OR, 0.145; 95%CI, 0.063-0.335) and antimicrobial therapy (OR, 0.328; 95%CI, 0.136-0.787). The higher failure rate of conservative strategies was associated with symptom duration >1 month (OR, 3.378; 95%CI, 1.089-4.005) and retromuscular mesh position (OR, 0.444; 95%CI, 0.199-0.992).
Conclusion:
Mesh infection is associated with high treatment failure rates. Complete mesh removal coupled with targeted antibiotic therapy is associated with better outcomes. Conservative treatment strategies must rely on careful patient selection based on symptom duration and mesh placement.
Insights
Mesh infection after abdominal wall reconstruction has high failure rates. Complete mesh removal and targeted antibiotics improve outcomes, while conservative approaches require careful patient selection based on symptom duration and mesh placement.
Area of Science:
- Surgical infections
- Mesh-related complications
- Microbiology of surgical site infections
Background:
- Abdominal wall reconstruction is a common procedure with a risk of mesh-associated infection.
- Management strategies for mesh infections are not well-established.
- Understanding clinical and microbiological aspects is crucial for effective treatment.
Purpose of the Study:
- To comprehensively analyze clinical and microbiological features of mesh infections.
- To evaluate treatment modalities and their associated outcomes.
- To identify determinants of treatment failure in mesh infections.
Main Methods:
- Retrospective observational cohort study of patients with abdominal mesh infection (2010-2023).
- Analysis of patient characteristics, management strategies, and treatment outcomes.
- Logistic regression and Kaplan-Meier survival analysis were used to assess failure determinants.
Main Results:
- 209 patients experienced mesh infection, often as deep abscesses within 15 days post-surgery.
- Infections were frequently polymicrobial, with Staphylococcus aureus and Enterobacteriaceae being common.
- Treatment failure occurred in 30.1% of cases, associated with prior surgeries and conservative management; complete mesh removal and antibiotics were linked to better outcomes.
Conclusions:
- Mesh infection presents a significant challenge with high treatment failure rates.
- Complete mesh removal combined with targeted antibiotic therapy is associated with superior outcomes.
- Conservative management requires careful patient selection, considering symptom duration and mesh position.
More Related Videos


Related Concept Videos
 01:29
Appendicitis-II: Diagnostic Studies and Management
Diagnosing Appendicitis
It requires a multifaceted approach, starting with a detailed physical examination to pinpoint the location and nature of the pain and identify any associated symptoms. Laboratory tests play a crucial role. A complete Blood Count (CBC) typically reveals leukocytosis (an increased number of...
 01:28
Esophageal Perforation-II: Clinical Manifestations and Management
Clinical Manifestations: