

Prevalence and prognostic impact of ST-segment elevation in lead aVR among patients with cardiac arrest
Soumya Banna1, Christopher Schenck2, Noah Kim3
1Department of Internal Medicine, Yale School of Medicine, New Haven, CT, USA.

Insights
ST-segment elevation in lead aVR (STE-aVR) was found in nearly one in five cardiac arrest survivors. This ECG finding independently predicts higher in-hospital mortality, highlighting its prognostic value.
Area of Science:
- Cardiology
- Emergency Medicine
- Electrocardiography
Background:
- ST-segment elevation in lead aVR (STE-aVR) in acute coronary syndrome signifies global myocardial ischemia and is linked to worse outcomes.
- The prevalence and prognostic implications of STE-aVR in cardiac arrest (CA) patients remain largely uncharacterized.
Purpose of the Study:
- To determine the prevalence of STE-aVR in patients who achieve return of spontaneous circulation (ROSC) after cardiac arrest.
- To investigate the association between STE-aVR and in-hospital mortality and neurologic outcomes in cardiac arrest survivors.
Main Methods:
- Retrospective analysis of 443 cardiac arrest patients (≥18 years) between 2011-2022 who achieved ROSC.
- Electrocardiograms (ECGs) post-ROSC were assessed for STE-aVR (≥1 mm ST-segment elevation at J point).
- Multivariable logistic regression analyzed the association of STE-aVR with in-hospital mortality and poor neurologic outcome.
Main Results:
- STE-aVR was identified in 18.3% of cardiac arrest survivors.
- Patients with STE-aVR were more likely to have out-of-hospital CA and less likely to have shockable rhythms.
- STE-aVR was significantly associated with increased in-hospital mortality (OR 2.23; 95% CI: 1.02-4.84) after multivariable adjustment.
Conclusions:
- ST-segment elevation in lead aVR is a notable finding in approximately one in five cardiac arrest survivors.
- STE-aVR is independently associated with a higher risk of in-hospital mortality following cardiac arrest.
Aims:
In acute coronary syndrome, ST-segment elevation in lead aVR (STE-aVR) indicates global myocardial ischaemia, often related to multivessel or severe left main disease, and correlates with increased mortality. The prevalence and prognostic significance of STE-aVR in cardiac arrest (CA) patients is unknown.
Methods And Results:
We identified patients (≥18 years) with CA between 2011 and 2022 who achieved return of spontaneous circulation (ROSC). The first electrocardiogram post-ROSC was assessed for STE-aVR, defined as ≥1 mm ST-segment elevation at the J point, measured by two trained assessors. Multivariable logistic regression was used to analyse the association between STE-aVR and outcomes (in-hospital mortality and poor neurologic outcome), adjusted for patient and arrest characteristics. Including 443 CA patients, the median (interquartile range) age was 61 years (50-72 years), with 60.5% (n = 268) male, 65.7% (n = 291) presenting with out-of-hospital CA (OHCA), and 29.8% (n = 132) with shockable rhythms. ST-segment elevation in lead aVR was observed in 18.3% (n = 81) of patients. Those with STE-aVR were more likely to present with OHCA and less likely to have a shockable rhythm (both, P < 0.05). ST-segment elevation in lead aVR was associated with higher in-hospital mortality (86.4% vs. 65.8%, P < 0.001) and poor neurologic outcomes (90.1% vs. 72.9%, P = 0.001). After multivariable adjustment, STE-aVR remained associated with higher in-hospital mortality [odds ratio (OR) 2.23; 95% confidence interval (CI): 1.02-4.84, P = 0.04], but not a poor neurologic outcome (OR 2.12; 95% CI: 0.90-4.98, P = 0.09).
Conclusion:
ST-segment elevation in lead aVR was present in one in five CA survivors and was independently associated with higher in-hospital mortality.
More Related Videos
 08:28
Methods for ECG Evaluation of Indicators of Cardiac Risk, and Susceptibility to Aconitine-induced Arrhythmias in Rats Following Status Epilepticus
Published on: April 5, 2011
 05:26
Postconditioning with Lactate-enriched Blood for Cardioprotection in ST-segment Elevation Myocardial Infarction
Published on: May 28, 2019
Related Concept Videos
 01:29
Electrocardiogram
Three major waveforms are present in a typical ECG recording: the P wave, the QRS complex, and...
 01:28
Electrocardiogram Fundamentals
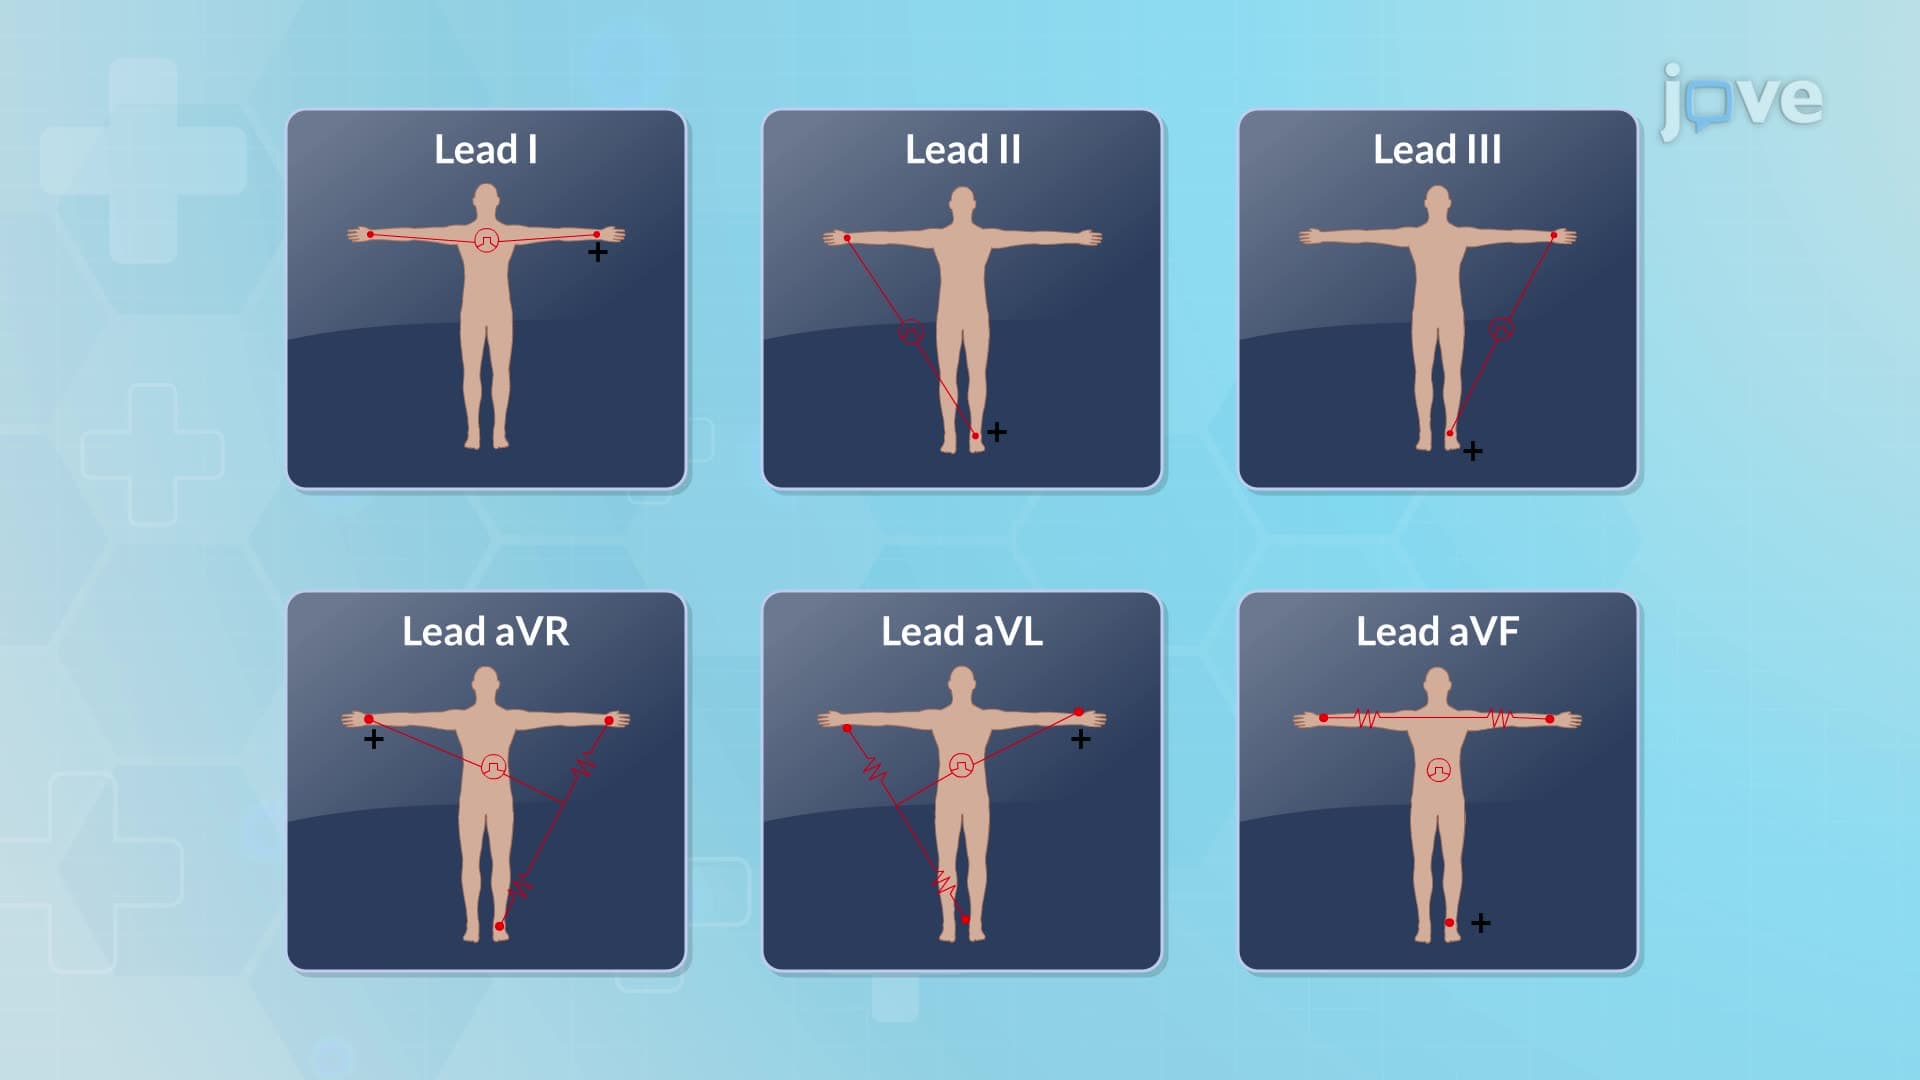
An electrocardiogram (ECG) is a diagnostic tool for identifying cardiac conditions such as arrhythmias, conduction abnormalities, and myocardial ischemia.
Definition
An electrocardiogram (ECG) visualizes the heart's electrical activity by tracing the electrical movement associated with each heartbeat on a graph or monitor. As the heart beats, an electrical wave passes through it, correlating with the cardiac cycle events.
Parts of an ECG
An ECG utilizes electrodes on the skin...