Related Experiment Video
Updated: May 8, 2026


Implantation of a Carotid Cuff for Triggering Shear-stress Induced Atherosclerosis in Mice
Published on: January 13, 2012
Prolonged sitting is not associated with altered shear-mediated dilation of the internal carotid artery, despite
Shotaro Saito1, Kento Dora1, Marino Karaki2
1Department of Biomedical Engineering, Toyo University, Saitama, Japan.

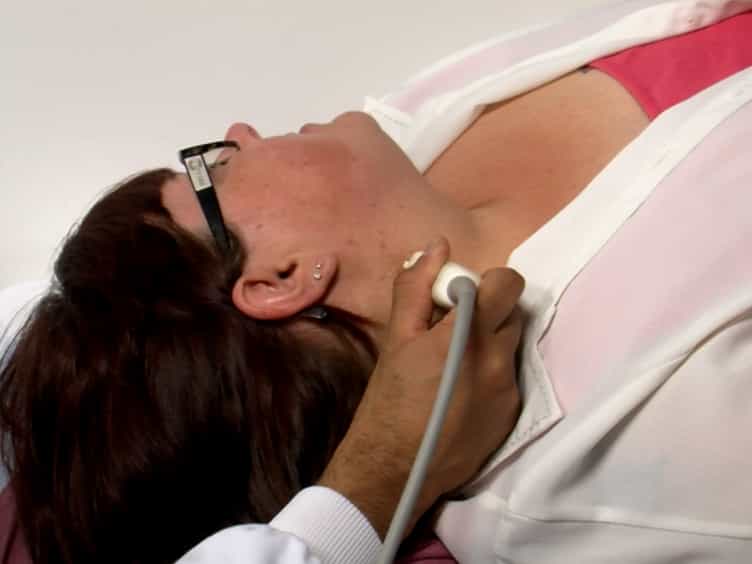
The present study aims to examine the effect of 4 h of continuous sitting on cerebral endothelial function, which is a crucial component of cerebral blood flow regulation. We hypothesized that 4 h of sitting may impair cerebral endothelial function similarly to how it affects lower limb vasculature. Thirteen young, healthy participants were instructed to remain seated for 4 h without moving their lower limbs. The blood flow and shear rate (SR) in the popliteal and internal carotid artery (ICA) were measured using duplex Doppler ultrasound. During the 4-h sitting, peripheral (popliteal artery) and cerebral (ICA) endothelial function were assessed every hour. We induced peripheral and cerebral flow-mediated dilation (pFMD and ICA FMD) using hyperemia (5 min of cuff inflation on lower limb, then deflation) or hypercapnia (30s of hypercapnia, end-tidal partial pressure of CO2 + 9 mmHg), respectively. We then calculated each relative peak dilation from the baseline diameter to identify both pFMD and ICA FMD. We observed a significant decrease in pFMD starting at 2 h from the onset of sitting, and this reduction persisted throughout the 4-h sitting [Base (6.8 ± 4.2%) vs. 2-h (3.9 ± 2.0%), p = 0.044; vs. 3-h (3.2 ± 1.8%), p = 0.016; vs. 4-h (3.2 ± 1.9%), p = 0.005]. In contrast, during the 4-h sitting, ICA blood flow, SR, and ICA FMD remained unchanged (p = 0.062, p = 0.068, and p = 0.203, respectively). Unlike peripheral endothelial function, cerebral endothelial function remained stable during 4-h sitting. This suggests that the acute effect of prolonged sitting on cerebral vasculature differs from that of lower limb vasculature.
The present study aims to examine the effect of 4 h of continuous sitting on cerebral endothelial function, which is a crucial component of cerebral blood flow regulation. We hypothesized that 4 h of sitting may impair cerebral endothelial function similarly to how it affects lower limb vasculature. Thirteen young, healthy participants were instructed to remain seated for 4 h without moving their lower limbs. The blood flow and shear rate (SR) in the popliteal and internal carotid artery (ICA) were measured using duplex Doppler ultrasound. During the 4-h sitting, peripheral (popliteal artery) and cerebral (ICA) endothelial function were assessed every hour. We induced peripheral and cerebral flow-mediated dilation (pFMD and ICA FMD) using hyperemia (5 min of cuff inflation on lower limb, then deflation) or hypercapnia (30s of hypercapnia, end-tidal partial pressure of CO2 + 9 mmHg), respectively. We then calculated each relative peak dilation from the baseline diameter to identify both pFMD and ICA FMD. We observed a significant decrease in pFMD starting at 2 h from the onset of sitting, and this reduction persisted throughout the 4-h sitting [Base (6.8 ± 4.2%) vs. 2-h (3.9 ± 2.0%), p = 0.044; vs. 3-h (3.2 ± 1.8%), p = 0.016; vs. 4-h (3.2 ± 1.9%), p = 0.005]. In contrast, during the 4-h sitting, ICA blood flow, SR, and ICA FMD remained unchanged (p = 0.062, p = 0.068, and p = 0.203, respectively). Unlike peripheral endothelial function, cerebral endothelial function remained stable during 4-h sitting. This suggests that the acute effect of prolonged sitting on cerebral vasculature differs from that of lower limb vasculature.

Related Concept Videos
 01:30
Peripheral Artery Disease I: Introduction
 01:21
Peripheral Arterial Disease II: Clinical Manifestations and Diagnostic Evaluation
 01:27
Peripheral Artery Disease III: Interprofessional Care