Related Experiment Video
Updated: May 29, 2025
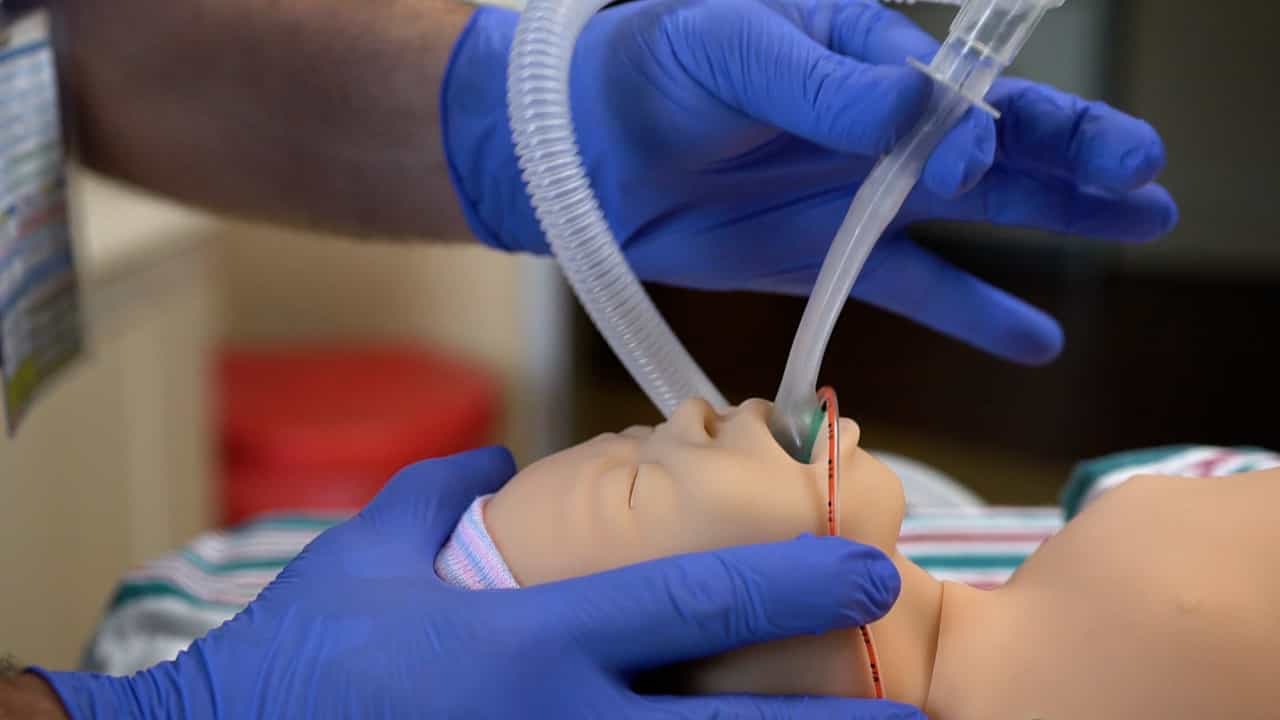

Laryngeal Mask Airway LMA Placement in a Neonatal Patient Simulator Using a Non-Inflatable Supraglottic Airway SGA
Published on: July 14, 2023
Confirmation of successful supraglottic airway device placement in neonates using a respiratory function monitor
Robyn Dvorsky1, Tobias Werther1, Katharina Bibl1
1Division of Neonatology, Pediatric Intensive Care and Neuropediatrics, Department of Pediatrics, Comprehensive Center for Pediatrics, Medical University of Vienna, Vienna, Austria.

Background:
This study investigated the use of a respiratory function monitor (RFM) to guide the placement of a supraglottic airway device (SAD) in neonates during intensive care interventions. We hypothesized that using a RFM would decrease the number of attempts needed for a successful placement.
Methods:
This single-center pilot study was carried out at a tertiary NICU at the Medical University of Vienna. Patients were ventilated using a SAD during neurosurgical or endoscopic interventions. A RFM was either hidden (but recording) or visible to providers during SAD placement. Feedback from the RFM was used to assess correct/incorrect placement and optimize ventilation quality. The parameter leakage was used for assessment: if leak was <30%, correct placement was assumed. The primary outcome was the number of attempts until correct placement. Secondary outcomes included ventilation parameters recorded by the RFM and the duration of SAD placement.
Results:
Six patients were included in this pilot trial. Using a RFM to guide SAD placement led to fewer attempts (median attempts: 3 [hidden] vs. 1 [visible]). Furthermore, using the RFM, necessary adaptations were made to the SAD position to decrease leakage (mean leakage: 74.8% [hidden] vs. 17.8% [visible]), subsequently endoscopy after insertion of SAD using the RFM then confirmed anatomically correct position.
Conclusion:
This pilot study indicated that a RFM might be useful to provide guidance during SAD placement.
Impact Statement:
Feedback from a RFM reliably indicated correct anatomical placement of a SAD by correlating low leakage values with proper SAD positioning. RFM guidance could improve neonatal airway management, reducing procedural time and number of attempts. We present promising preliminary results. Further research is needed to confirm these findings.
More Related Videos

Related Concept Videos
 01:30
Assessment of Airway, Skin Color, and Use of Accessory Muscles
Introduction
The initial evaluation of a patient's respiratory system...
 01:15
Endotracheal Intubation I: Procedure
The ET tube comprises various components, including a standard adaptor to attach a bag-valve-mask (BVM) or ventilator, a cuff, a pilot balloon, and radiopaque markings along its length to measure the insertion distance. The tube sizes...
 01:24
Endotracheal Tube Extubation
Procedure
Extubation removes the endotracheal tube (ETT) from the patient on mechanical ventilation. It requires a well-coordinated, multidisciplinary approach involving physicians, nurses, respiratory therapists, and other healthcare professionals....
 01:16
Oxygen Delivering System II: Venturi Mask and Transtracheal Oxygen
Venturi Mask
The Venturi mask, named after the Venturi effect, is designed to deliver precise oxygen concentrations. It consists of a large tube with an oxygen inlet that narrows down, causing a pressure drop that pulls air in through adjustable side ports. The mask is a lightweight,...